
Longevity
October 16, 2026
Ivermectin and fenbendazole for cancer: what the research and recovery stories actually tell us
On this page
If you have been looking into ivermectin or fenbendazole for cancer, you have probably encountered two very different conversations. One describes inexpensive medicines with exciting laboratory results and remarkable recovery stories. The other warns that the evidence in people is too limited to guide treatment.
There is real research behind the interest. There are also gaps that matter enormously when someone has cancer and needs to make a decision now. A drug can damage cancer cells in an experiment without helping a person live longer. A person can improve after starting a drug without that drug being responsible. Neither observation means the research should be dismissed. It means we need to understand exactly what was measured.
As of October 16, 2026, the available evidence does not establish ivermectin or fenbendazole as effective cancer treatments in people. Ivermectin is being tested in a small breast cancer trial whose early results were modest, and a second trial is due to open. Fenbendazole has laboratory findings, human case reports and a growing list of published liver injuries, but no registered cancer trial. ASCO, the largest professional society of cancer specialists, advises against using either drug for cancer outside well-designed clinical trials, including as an addition to standard treatment. ASCO clinical notice, ASCO's June 2026 communication
This guide covers the strongest reasons to investigate these drugs, the human evidence, the stories that made them famous, the people and podcasts behind the conversation, the risks, and the argument for trying them alongside standard care. It ends with a directory of studies, organizations, videos and communities so you can continue your own research.
If this question affects your own care, bring the article and the sources that interest you to your oncology team. Do not stop or postpone a recommended cancer treatment to try either drug.
The short answer
- The science is real but early. Both drugs affect cancer cells in laboratory and animal experiments. Some of the most cited experiments have since been corrected, questioned or retracted, and several careful experiments found no effect.
- The human evidence is thin. For ivermectin, there are small reports and one early trial result: 1 partial response among 8 evaluable women with heavily pretreated breast cancer. Fenbendazole has never been studied in a cancer trial. The related human drug mebendazole has mixed trial results.
- The famous recoveries involved other treatment. Joe Tippens, whose story launched the fenbendazole movement, was also in an immunotherapy trial. Most widely shared recoveries involve chemotherapy, immunotherapy, radiation or surgery at the same time.
- "Harmless" is not established for this use. Ivermectin is very safe as a short antiparasitic course. Cancer protocols use it daily for months, often at higher doses. Published reports describe liver injury, seizures and treatment interruptions in people with cancer.
- The biggest measured danger is skipping effective care. People who used alternative medicine instead of standard treatment had about two and a half times the risk of death in a large US study.
First, these are three different medicines
Ivermectin, fenbendazole and mebendazole often appear together in online discussions. Keeping their names separate prevents a surprising amount of confusion.
Ivermectin is a medicine used in humans for certain parasitic infections. It belongs to a class called macrocyclic lactones and is on the World Health Organization's list of essential medicines. Its established antiparasitic uses tell us that it can be a valuable medicine; they do not establish a cancer indication. The US oral Stromectol label describes treatment of intestinal strongyloidiasis and onchocerciasis, usually as a single dose of 150 to 200 micrograms per kilogram of body weight. Stromectol prescribing information
Fenbendazole is a veterinary antiparasitic in the benzimidazole family. It is not approved by the FDA for human use. Calling it an animal medicine is a statement about its development and authorization, not an argument that it cannot have interesting biology. The problem is that veterinary experience cannot supply the missing human safety and effectiveness data. American Cancer Society's fenbendazole overview
Mebendazole is a related benzimidazole with human antiparasitic uses and its own cancer research. A positive mebendazole study does not become a positive fenbendazole study because the names sound similar. Related drugs can differ in absorption, metabolism, tissue exposure and adverse effects. Emverm prescribing information
The same applies to albendazole, another human benzimidazole, and to oxfendazole, which the body produces from fenbendazole and which has been tested in healthy volunteers for parasitic disease.
The evidence ladder used in this article
Each study below is described by where it sits on this ladder. The higher the rung, the more directly it answers the question a patient is actually asking: will this help me live longer or better?
- Laboratory (cell) studies: cancer cells grown in a dish, exposed to a known concentration.
- Animal studies: usually mice carrying implanted tumors.
- Case reports and testimonials: what happened to one or a few selected people, usually alongside other treatment.
- Uncontrolled studies: a group of patients treated and followed, with no comparison group.
- Controlled trials: patients assigned to receive the drug or not, so its added effect can be measured.
- Replicated controlled trials: the same result found again by independent teams.
Most of the ivermectin and fenbendazole evidence sits on the first three rungs. That does not make it worthless. It means it can justify a trial, not replace one.
Evidence at a glance
Drug
Ivermectin
- Lab and animal studies
- Many positive; several key papers corrected, questioned or retracted
- Human reports
- Small case series, testimonials
- Clinical trials
- One small phase 1/2 trial (early results modest); one randomized trial not yet open
- Main safety signal in cancer use
- Neurological toxicity and drug interactions at high or prolonged doses
Drug
Fenbendazole
- Lab and animal studies
- Mixed; some positive, several null in animals
- Human reports
- Case series, testimonials, at least six published liver injuries
- Clinical trials
- None registered
- Main safety signal in cancer use
- Liver injury
Drug
Mebendazole
- Lab and animal studies
- Positive in several models
- Human reports
- Case reports
- Clinical trials
- Several trials: one small positive randomized trial, others negative or uncontrolled
- Main safety signal in cancer use
- Liver enzyme rises at high doses
How these drugs became cancer talking points
Most people arrive at this topic through a story rather than a study. The stories matter because they explain why the interest exists, and because their full details are often missing in the retelling.
A laboratory accident at Johns Hopkins (2008)
Researchers studying human lymphoma in mice noticed that tumors stopped growing as expected after the animal facility switched to chow medicated with fenbendazole, which also happened to contain extra vitamins. They investigated. Fenbendazole alone did not change tumor growth. Vitamins alone did not either. Only the combination did. The authors presented it as a warning that routine animal-facility medicines can confound cancer experiments, not as a treatment discovery. Gao, Dang and Watson, Journal of the American Association for Laboratory Animal Science, 2008
Joe Tippens (2016 to 2017)
The modern fenbendazole movement traces to Joe Tippens, who was diagnosed with small-cell lung cancer in 2016. By his own account he received chemoradiation and brain radiation, learned in January 2017 that the cancer had spread widely, and then joined a clinical trial at MD Anderson. Around the same time, on a veterinarian's suggestion, he began fenbendazole with CBD and a curcumin product. He reports a clear scan in May 2017 and no detectable disease for years afterward. Tippens's protocol page
The detail that usually goes missing is the trial. Tippens told the Daily Dot it was Merck's trial of pembrolizumab (Keytruda), an immunotherapy that can produce delayed and long-lasting responses in a minority of patients. The claim that he was the trial's only responder has not been verified. Fact-checkers at PolitiFact and Science Feedback both concluded that his recovery cannot be credited to fenbendazole. Daily Dot, PolitiFact, Science Feedback
Tippens says plainly that he is not a doctor or scientist. His protocol page now also recommends a line of supplement products, while stating that he receives no payment from the company.
South Korea's fenbendazole rush (2019 to 2021)
In 2019, the Tippens story spread through Korean YouTube. Comedian Kim Chul-min, who had advanced lung cancer, announced that he was taking fenbendazole alongside his chemotherapy and radiotherapy. Pharmacies sold out of fenbendazole and then of the human dewormer albendazole. Korea's drug regulator, its medical association and its oncology society all issued warnings. Korea Times, October 2019, Heo, Journal of Korean Medical Science, 2020
A year later, Kim said his liver readings had risen and his cancer had spread, and he urged other patients to stop taking it. He died in December 2021, aged 54. His public reversal received far less attention than his original announcement. Korea Times, October 2020, Korea Times, December 2021
From COVID to Joe Rogan (2020 to 2026)
Ivermectin became famous during the COVID-19 pandemic, when laboratory results prompted widespread use before large trials found no meaningful benefit for COVID. Many of the same clinicians and audiences later turned to cancer. In January 2025, actor Mel Gibson told Joe Rogan that three friends with stage IV cancer no longer had cancer after using ivermectin, fenbendazole and other substances. In the following months, prescriptions combining ivermectin with a benzimidazole roughly doubled overall and rose 2.63-fold among people with cancer, according to an analysis of 68 million patient records. Rockwell et al., JAMA Network Open, 2026
Year
1996
- Event
- Lab study reports ivermectin can block a drug pump that cancer cells use to resist chemotherapy
Year
2008
- Event
- Johns Hopkins mouse study: fenbendazole plus vitamins, not fenbendazole alone, slowed lymphoma
Year
2014
- Event
- ReDO project publishes its review of mebendazole as a cancer candidate
Year
2016 to 2017
- Event
- Joe Tippens's recovery during an immunotherapy trial
Year
2018
- Event
- Influential fenbendazole cell and mouse study (Dogra)
Year
2019
- Event
- South Korean fenbendazole rush and government warnings
Year
2021
- Event
- "Cold to hot" ivermectin breast cancer mouse study (Draganov)
Year
2023
- Event
- Ivermectin and immunotherapy breast cancer trial (NCT05318469) begins
Year
January 2025
- Event
- Mel Gibson on The Joe Rogan Experience; prescriptions rise
Year
May 2025
- Event
- First interim trial results presented at ASCO
Year
January 2026
- Event
- Three-patient Makis paper retracted; National Cancer Institute announces a laboratory study of ivermectin
Year
February to June 2026
- Event
- Draganov paper corrected, then given an expression of concern
Year
April to October 2026
- Event
- Industry-run ivermectin and mebendazole survey published, questioned, then retracted
Year
May to June 2026
- Event
- ASCO clinical notice advises against use outside trials
Year
2026
- Event
- Randomized ivermectin and immunotherapy trial (ICONIC) registered
Why researchers are interested in repurposing drugs
Drug repurposing means investigating a medicine for a different use from the one it was originally developed for. The idea is sensible. An existing compound may affect a biological process that also matters in cancer, and researchers already know something about its manufacture and behavior in the body. Credible organizations such as the Anticancer Fund champion repurposing for exactly this reason. Anticancer Fund on repurposed drugs
That can make a promising candidate easier to investigate. It does not remove the need to investigate it. A short course for a parasite and months of use alongside chemotherapy are different clinical situations. Someone with impaired liver function, substantial weight loss or several other medicines may handle a drug differently from a healthy volunteer.
The strongest scientific case for these particular candidates is not that cancer is secretly a worm infection. It is that drugs can have more than one biological effect. A compound developed against a parasite may also alter cell division, stress responses or signaling in a cancer model.
There is an important nuance here. Some infections, including certain parasites, do increase the risk of particular cancers. Some liver flukes are associated with bile duct cancer, and Schistosoma haematobium is associated with bladder cancer. That does not make an established tumor equivalent to a parasite, or mean that any deworming medicine will treat it. National Cancer Institute on infectious agents and cancer
The practical research question is narrower and more useful: can this particular drug, at a tolerable exposure, improve a meaningful outcome in this particular cancer?
What fenbendazole might do inside a cancer cell
One of the best-known fenbendazole papers is a 2018 study by Dogra and colleagues. It investigated human lung cancer cell lines and a mouse tumor model. The researchers reported effects involving microtubules, the p53 pathway and glucose handling, alongside reduced tumor growth in their animal experiment. Dogra et al., Scientific Reports, 2018
Microtubules are tiny structures that help organize a cell and move material around it. During cell division, they help separate duplicated chromosomes into the two new cells. Interfering with that process can make it difficult for a dividing cell to survive. This is a credible area of cancer biology: several established chemotherapy medicines act on microtubules. But a shared cellular target does not make two drugs clinically interchangeable. The amount that reaches a tumor, the duration of exposure and the effect on healthy tissues can be very different.
The other part of the hypothesis involves how cells respond to stress. The p53 protein helps regulate responses to cellular damage. Cancer can disrupt that system in several ways, and tumors with different p53 biology may not respond alike.
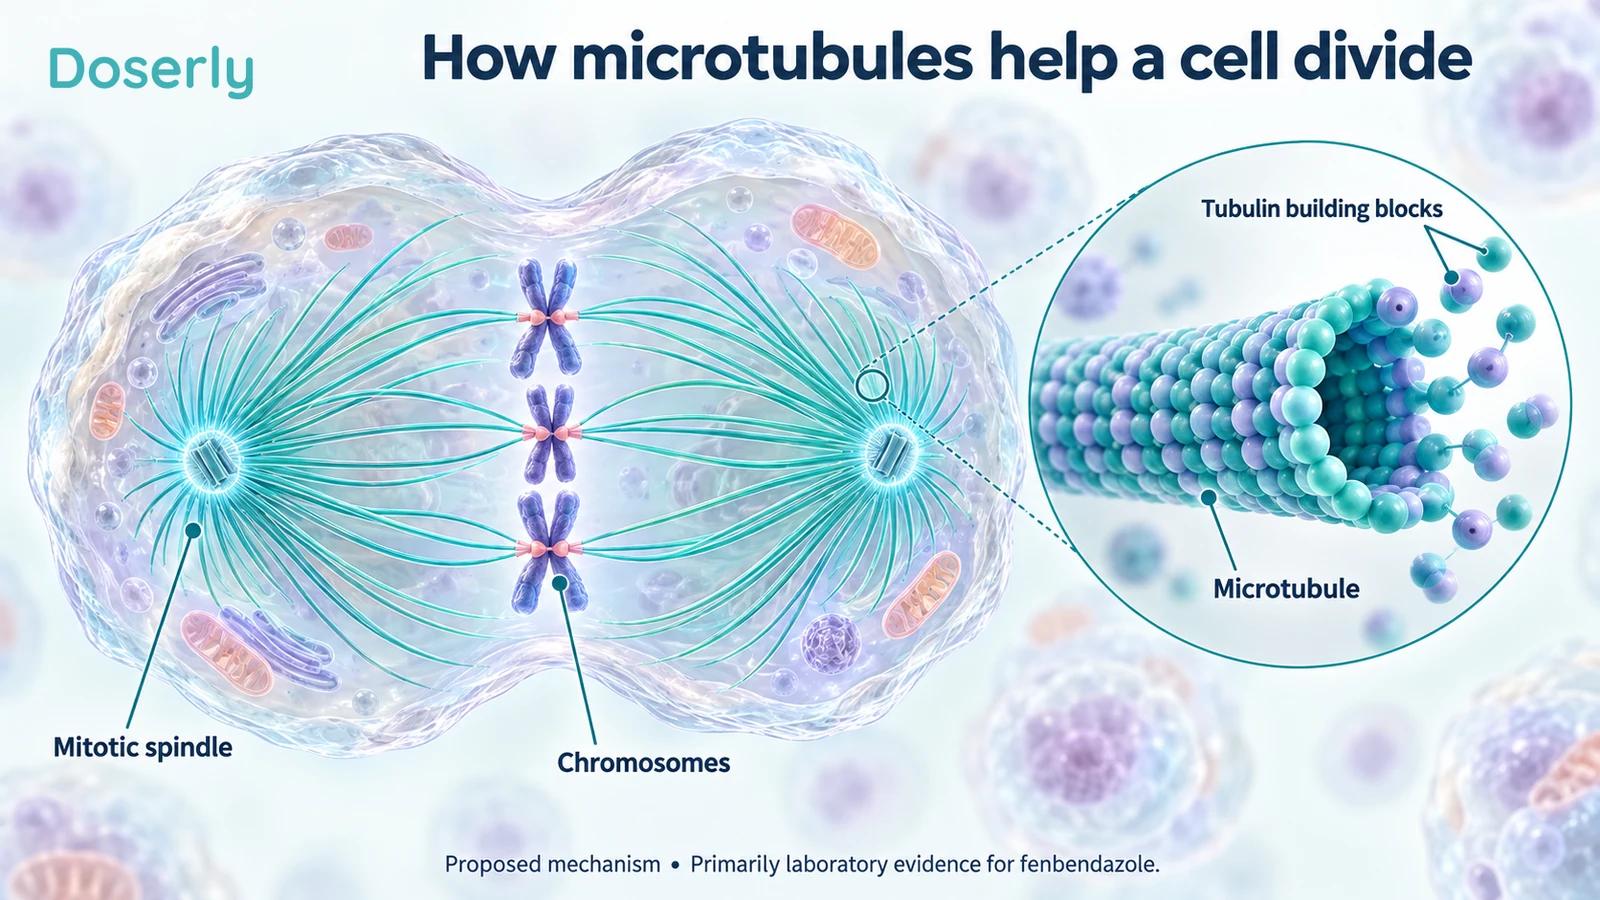
Two terms appear constantly in this research. A cell line is a population of cancer cells, originally from a patient, grown in a laboratory. A headline that says "kills human cancer cells" can sound much closer to clinical evidence than it really is, because the cells sit outside a body's circulation, immune system and organs. A xenograft is a tumor implanted into an animal. It shows more than a dish can, but it still cannot reproduce a person's cancer or predict every human side effect.
The experiments that found little or nothing
Selecting only favorable experiments gives an incomplete picture. Several careful studies found that fenbendazole's effect in a dish did not carry over to a living animal:
- Duan, Liu and Rockwell, 2012 and 2013. Fenbendazole was toxic to a mouse breast cancer cell line in the laboratory, but a fenbendazole-medicated diet did not change tumor growth, spread or response to radiation in mice. 2012 study, 2013 study
- Jung and colleagues, 2023. Fenbendazole killed lymphoma cells in a dish but had no effect on lymphoma in mice, and the treated tumors showed a more immunosuppressive environment. Jung et al., Current Issues in Molecular Biology, 2023
- Gao and colleagues, 2008. As described above, fenbendazole alone did not slow lymphoma growth.
These do not invalidate every positive experiment. Different tumor models, formulations and exposures can produce different results. They do show that "it kills cancer cells" is too broad to guide treatment. The useful questions are which cells, under what conditions, and what happened in the whole organism.
What ivermectin might do: signaling, cellular stress and immunity
Ivermectin has been investigated through many proposed anticancer mechanisms. Review articles map them in detail. Juarez et al., American Journal of Cancer Research, 2018, Tang et al., Pharmacological Research, 2021
- Cell stress and death. A 2010 leukemia study reported effects on chloride movement, membrane electrical charge and reactive oxygen species, with activity in leukemia cells and mice. Sharmeen et al., Blood, 2010
- Growth signaling. A 2014 paper reported that ivermectin inhibited WNT signaling, a pathway important in colorectal and other cancers. Melotti et al., EMBO Molecular Medicine, 2014 Other frequently cited papers describe effects on PAK1 and autophagy in breast cancer, SIN3 in triple-negative breast cancer and YAP1 in gastric cancer. Dou et al., 2016, Kwon et al., 2015, Nambara et al., 2017
- Drug resistance. Ivermectin can block P-glycoprotein, a pump some cancer cells use to expel chemotherapy, which is why it has been studied for reversing resistance. Didier and Loor, 1996, Jiang et al., 2019
These pathway names can make an argument sound more complete than it is. Identifying a change in WNT, AKT or another signaling system is not the same as showing that a tolerable human dose changes that pathway enough, in the right tissue, to improve survival.
The "cold tumor to hot tumor" idea
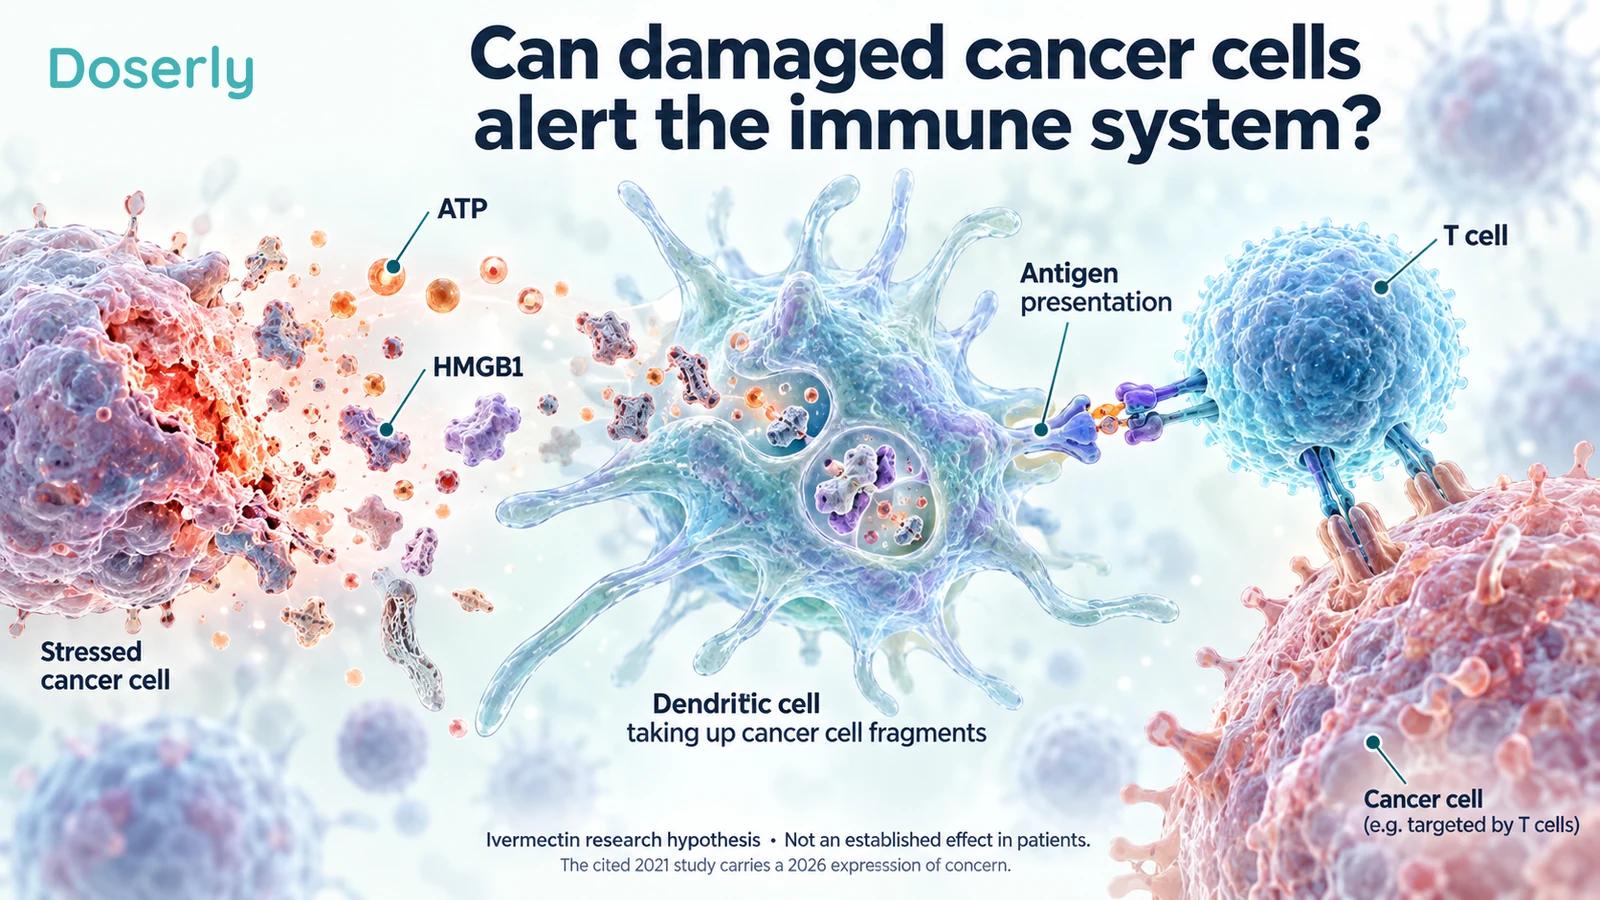
A particularly influential 2021 breast cancer paper proposed that ivermectin could make tumors more responsive to immune checkpoint treatment. A "cold" tumor has relatively little immune activity against it; a "hotter" tumor is more engaged with immune cells. The researchers reported immunogenic cell death, a form of cell damage that releases signals the immune system may recognize, and tested ivermectin with checkpoint blockade in mice. This work directly motivated the human trial described below. Draganov et al., npj Breast Cancer, 2021
The publication record has since changed. A February 2026 correction addressed problems with figure panels. In June 2026, the journal issued an expression of concern after further image concerns, noting that original data were unavailable and advising caution. An expression of concern is not a retraction, but this paper should no longer be presented without that qualification. Author correction, expression of concern
For a firsthand explanation of the research rationale, Peter Lee's interview with the Cancer Prevention Initiative describes screening existing medicines for effects that might help immunotherapy work. Read Lee's research interview
Publication integrity is a live issue
The Draganov paper is not alone. In 2026, two other ivermectin cancer laboratory papers were retracted: one testing ivermectin with sorafenib in liver cancer and one in glioma. McGill University's Office for Science and Society has documented image problems across this literature. Retractions do not prove the underlying idea is wrong, but they mean a long reference list should be checked paper by paper. Lu et al., 2022, retracted, Liu et al., 2019, retracted, McGill OSS
The missing step: getting enough drug to the right place
One of the most important differences between a dish and a person is drug exposure. In a dish, researchers place a known concentration directly around the cells. After someone swallows a medicine, it must be absorbed, circulate, reach the relevant tissue and remain available long enough to have an effect. Much of it binds to proteins in the blood, and some is broken down by the liver.

Ivermectin: the numbers
The ivermectin label reports an average peak blood concentration of about 46.6 nanograms per milliliter after a standard 12 mg dose. That is roughly 0.05 micromolar. Many anticancer experiments use around 5 micromolar, including a 2020 study whose title describes its concentrations as "clinically feasible." That laboratory concentration is about 90 times the average peak blood level after a label dose. Stromectol clinical pharmacology, Juarez et al., Cancer Chemotherapy and Pharmacology, 2020
The same gap decided ivermectin's fate in COVID-19. The famous 2020 laboratory study also used 5 micromolar, and pharmacologists calculated that blood levels would not reach it even at ten times the approved dose. Large trials later found no meaningful COVID benefit. Schmith et al., Clinical Pharmacology and Therapeutics, 2020
Higher exposure is not a simple fix. Toxicity may increase before the desired effect is reached, which is what dose-finding trials are designed to measure safely. Tumor tissue concentrations can also differ from blood levels in either direction, so a simple comparison can flag a problem without settling it.
A 2022 cervical cancer cell study raises a further concern. Some cell-killing effects tracked with solid ivermectin clumps in the laboratory preparation; filtering these out removed that effect. Remaining growth inhibition required concentrations the authors considered above achievable human levels. Qabbus et al., Toxicology and Applied Pharmacology, 2022
Brain tumors face an extra barrier. The label states that ivermectin does not readily cross the blood-brain barrier, because P-glycoprotein pumps it back out. That protects the brain from ivermectin's neurological effects, and it also limits exposure in glioblastoma and brain metastases. Schinkel et al., Cell, 1994
Fenbendazole: almost no human data
There is no published study measuring fenbendazole in people who took it directly. It dissolves poorly in water, which limits absorption. The closest human data come from oxfendazole, a related compound the body forms from fenbendazole: studies in healthy volunteers found it well tolerated but absorbed less than proportionally as doses increased. The only human fenbendazole measurement comes from one of these studies, where it appeared as a breakdown product of oxfendazole. An et al., 2019, Bach et al., 2020, Bach et al., 2021
Half-life is relevant to both drugs. Ivermectin's plasma half-life is about 18 hours, and food substantially increases how much is absorbed. Half-life does not mean the medicine is gone after one or two half-lives, and repeated daily doses produce overlapping exposure. Our half-life explainer walks through these principles with peptide examples; its individual drug estimates should not be transferred to ivermectin or fenbendazole.
Cancer type and treatment context change the question
"Cancer" includes many diseases. A result in one breast cancer model does not establish a result in pancreatic cancer, prostate cancer or leukemia. Even within a single organ, tumors can differ in mutations, receptors, immune activity and sensitivity to treatment.
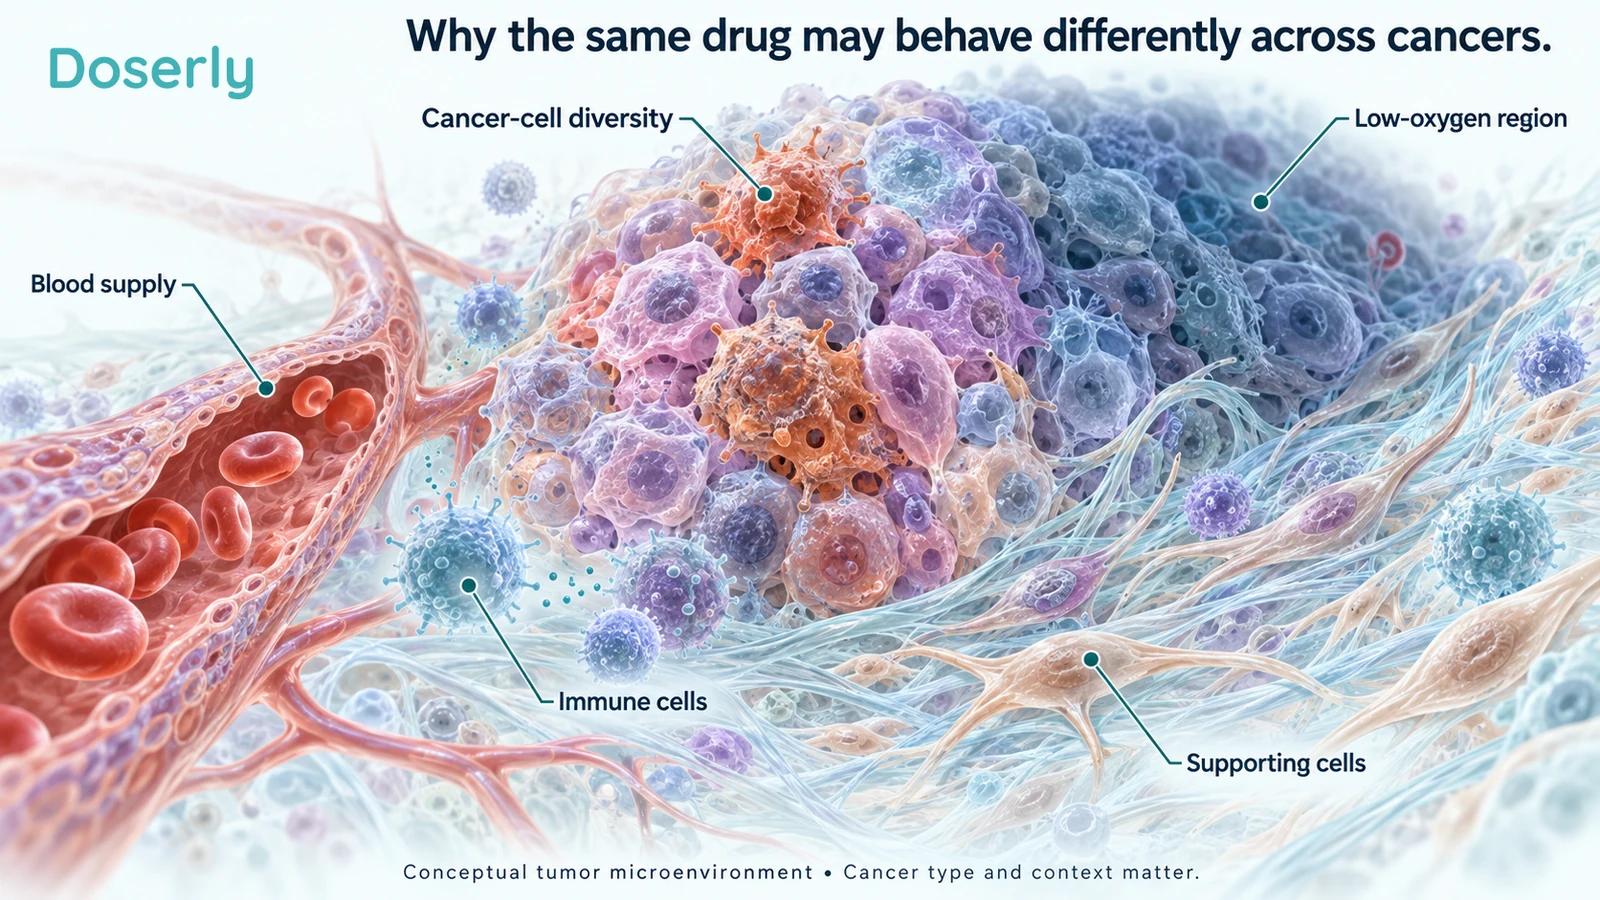
A tumor also contains more than cancer cells. Blood vessels, immune cells, connective tissue and regions with different oxygen and nutrient supplies can affect what happens. Cancer cells within the same tumor may differ from one another, and a treatment can affect one population while another survives. NCI's explanation of cancer biology
There is also a difference between investigating a medicine alone and investigating it as an addition. If a study combines ivermectin with an immunotherapy that already has activity, any improvement has to be interpreted in that context. A single-group study may show that the combination deserves a larger trial; it usually cannot tell us how much of the outcome came from the added medicine.
Treatment stage matters just as much. A study in heavily pretreated metastatic disease asks a different question from a study after surgery intended to reduce recurrence.
The clinical trials: what is registered and what has reported
Trial
NCT05318469
- What it tests
- Ivermectin with balstilimab or pembrolizumab in metastatic triple-negative breast cancer, Cedars-Sinai; phase 1/2, single group, about 34 people
- Status as of October 2026
- Recruiting; interim results presented May 2025
Trial
NCT07487805 (ICONIC)
- What it tests
- Two ivermectin doses added to standard immunotherapy in solid tumors, University of Florida; phase 2, randomized, 80 people
- Status as of October 2026
- Not yet recruiting; planned start December 2026
Trial
NCT02366884
- What it tests
- A Mexican study combining many anti-infective drugs
- Status as of October 2026
- Status unknown since 2022; no results
Trial
Fenbendazole
- What it tests
- No registered cancer trial
- Status as of October 2026
- None
Trial
Mebendazole
- What it tests
- Several registered cancer studies
- Status as of October 2026
- None with posted results; see the mebendazole section
The breast cancer trial's early results
NCT05318469 began in October 2023. Ivermectin is taken by mouth on three consecutive days each week of a three-week cycle, alongside an immunotherapy infusion. The main goals are to find a safe dose and measure how often tumors shrink. ClinicalTrials.gov record, NCI trial description
Interim results presented at ASCO in 2025 covered nine heavily pretreated patients who received ivermectin at 30, 45 or 60 mg with balstilimab. Of eight who could be assessed, one had a partial response, one had stable disease and six had progression. Median progression-free survival was 2.5 months. The investigators described the combination as well tolerated and the benefit rate as encouraging, and the study continues. Yuan et al., Journal of Clinical Oncology, 2025
That is a fair, early human signal: modest activity in very hard-to-treat cancer, in a design that cannot separate ivermectin's contribution from the immunotherapy's. Its estimated completion date is October 2026, so fuller results may appear soon.
ICONIC: testing benefit and possible harm
The University of Florida's ICONIC trial will randomly assign 80 people already receiving checkpoint immunotherapy to two ivermectin doses, 200 or 400 micrograms per kilogram, on three days a week for four weeks. Its main measurement is a T-cell marker in the blood. Notably, its rationale considers that ivermectin might weaken, rather than strengthen, the immune response. That is an honest acknowledgment that adding a drug is not automatically neutral. ClinicalTrials.gov record

A common misunderstanding is that trial registration means an institution has already endorsed the treatment. It means investigators are asking a question under a specified plan. Some trials produce encouraging results; others find insufficient activity, unacceptable toxicity or difficulty reaching the intended exposure.
Other human ivermectin evidence
A 2022 report by Ishiguro and colleagues described three patients treated with combinations including ivermectin, dichloroacetate, omeprazole and, in some cases, tamoxifen. The authors reported symptom improvements. Because several treatments were involved and there was no comparison group, the report cannot isolate ivermectin's contribution or establish a survival benefit. Ishiguro et al., Cureus, 2022
Symptom improvement deserves attention: walking more comfortably or having less pain matters deeply to a patient. But symptom relief, measured tumor shrinkage and longer survival are different outcomes.
A 2020 letter describes continuous high-dose ivermectin in patients with acute myeloid leukemia. Its focus is safety experience, not effectiveness, and the full letter is not openly available. de Castro et al., Leukemia and Lymphoma, 2020
The largest human datasets on higher-dose ivermectin come from outside cancer. Guzzo and colleagues gave escalating doses up to ten times the standard amount to 68 healthy volunteers. COVID-19 trials such as ACTIV-6 gave up to 600 micrograms per kilogram daily for six days to hundreds of people. These studies found short courses generally tolerable. They do not establish the safety of months of daily use, combinations with cancer drugs, or use by people with organ impairment. Guzzo et al., Journal of Clinical Pharmacology, 2002, Navarro et al., Journal of Antimicrobial Chemotherapy, 2020
What the human fenbendazole reports show
Human fenbendazole evidence comes entirely from individual stories and small uncontrolled reports. Some describe meaningful improvements; others describe harm. Both need to be read with the treatment timeline intact.
A 2021 case series by Chiang and colleagues describes three patients with genitourinary cancers. It appeared in a journal from SciTechnol, a publisher that has appeared on lists of questionable open-access publishers, which makes careful reading of the details more important. Read the original case series
- Kidney cancer: A man with metastatic disease had previously received surgery and several cancer medicines. Fenbendazole began around the time of a short course of nivolumab immunotherapy. Subsequent imaging improved. The authors acknowledge that nivolumab could have contributed.
- Urethral cancer: A man received brain-directed radiation, chemotherapy and immunotherapy, followed by further chemotherapy that produced a near-complete response. After a lymph node enlarged, he used fenbendazole with several supplements; the node subsequently became smaller.
- Bladder cancer: A woman received tumor resection through the urethra and combination chemotherapy while also taking fenbendazole. Follow-up imaging was favorable, and she chose surveillance rather than bladder removal.
These are encouraging reported outcomes, but none isolates fenbendazole. An author's university affiliation does not make it a university-sponsored clinical trial.
A 2026 case report shows how an apparent response can unfold. A 74-year-old man with metastatic melanoma declined standard treatment and took ivermectin and fenbendazole. His circulating tumor DNA fell sharply and his scans initially improved. Then the cancer progressed. The authors argue that spontaneous regression, which is rare but documented in melanoma, is at least as plausible an explanation as the drugs. Cheng and Araujo, Frontiers in Oncology, 2026
The 2025 three-patient paper has been retracted
A paper by William Makis, Ilyes Baghli and Pierrick Martinez reported outcomes in three patients with breast cancer, prostate cancer and melanoma. It attracted attention because it described substantial responses. In January 2026, the publisher retracted it over an undeclared conflict of interest involving related services offered by the first author, and the publisher's assessment of its effect on interpretation and recommendations. That is not a finding that the patients' experiences were fabricated. It does mean the paper should not be cited as reliable efficacy evidence. Original article and current status, Publisher's retraction statement
A video recorded before a correction or retraction may accurately describe what the paper said at the time and still give viewers an outdated impression today.
Mebendazole and albendazole: the related drugs with more human data
Mebendazole has more direct human cancer research than fenbendazole, and its record is genuinely mixed. Keeping it separate lets us acknowledge promising findings without assigning them to fenbendazole. The reference review is the 2014 ReDO project paper by the Anticancer Fund and colleagues. Pantziarka et al., ecancermedicalscience, 2014
Encouraging single cases. A 48-year-old man with metastatic adrenocortical cancer, after progression on previous treatments, received mebendazole alone. The authors reported initial regression followed by stable disease for 19 months, with satisfactory quality of life, before progression at 24 months. Dobrosotskaya et al., Endocrine Practice, 2011 In Sweden, a man with treatment-resistant metastatic colon cancer had a marked remission of his metastases on mebendazole. Nygren and Larsson, Acta Oncologica, 2014
A small positive randomized trial. In 2022, 40 people with metastatic colorectal cancer received standard chemotherapy with bevacizumab plus either mebendazole or placebo. The abstract reported tumor response in 13 of 20 with mebendazole versus 2 of 20 with placebo, and median progression-free survival of 9.25 versus 3 months. It is a favorable controlled signal, but small, registered after the fact, and not yet independently replicated. Hegazy et al., Life Sciences, 2022
Negative and uncontrolled trials. The same Swedish group that reported the colon cancer remission later ran a trial of individually dosed mebendazole in advanced gastrointestinal cancers. It struggled to reach intended drug levels, every treated patient's cancer progressed, and it stopped early for lack of benefit. Mansoori et al., Scientific Reports, 2021 That arc, a striking case followed by a negative trial from the same researchers, is a model of how this research should work.
In brain tumors, an 88-person randomized trial in recurrent glioblastoma gave mebendazole to both groups; neither reached its nine-month survival benchmark. Patil et al., EClinicalMedicine, 2022 A Johns Hopkins phase 1 trial in newly diagnosed high-grade glioma found high-dose mebendazole could cause significant liver enzyme rises, with median survival of 21 months in an uncontrolled group. Gallia et al., Neuro-Oncology Advances, 2021 Pediatric phase 1 studies have focused on safety and dosing, and one reported limited evidence of single-drug effectiveness. Krystal et al., 2024, Phan et al., 2025 A 2026 systematic review concluded that current clinical evidence does not demonstrate meaningful efficacy in brain tumors. Blum et al., British Journal of Clinical Pharmacology, 2026
Albendazole has been tested in small early trials. In a 2001 pilot, three of seven patients developed severe drops in white blood cells, which probably contributed to one death; a later phase 1 study found bone marrow suppression to be the dose-limiting problem. Morris et al., 2001, Pourgholami et al., 2010
A cautionary retraction. A widely cited 2019 study of the Care Oncology Clinic protocol, which includes mebendazole with metformin, atorvastatin and doxycycline, was retracted in October 2026. The notice reports that the UK medicines regulator found it was a clinical trial conducted without appropriate ethics approval or informed consent. Agrawal et al., Frontiers in Pharmacology, 2019, retracted
The retracted 2026 ivermectin and mebendazole survey
A widely shared 2026 report claimed an 84 percent "clinical benefit" from ivermectin plus mebendazole. It enrolled 197 people and obtained six-month follow-up surveys from 122. Its benefit category counted stable disease alongside regression and no evidence of disease, and outcomes were patient-reported, in a mixed group receiving other treatments. Hulscher et al., Anticancer Research, 2026
All of its authors, including Peter McCullough, Drew Pinsky and Harvey Risch, were affiliated with The Wellness Company, which sells the compounded capsule that was studied, and the project did not have ethics board review. The journal issued an expression of concern in June 2026 and retracted the paper on October 1, 2026, citing methodological and analytical problems. A John Campbell video promoting it had been viewed about 600,000 times. Retraction notice, Lead Stories fact check
There is a general lesson here. A percentage based on follow-up respondents is not the percentage among everyone who started treatment, because people missing from follow-up may have different outcomes. "Clinical benefit" is also not the same as tumor response, cure or benefit caused by the drug.
How to read recovery stories without dismissing people
It is reasonable to be moved by someone describing an unexpected recovery. The experience may be entirely real. The harder question is what caused it.
Imagine a person who starts an experimental medicine shortly after beginning immunotherapy. Their next scan looks better. The timeline supports the statement that improvement occurred after both treatments began. It does not tell us how much came from either treatment. The opposite conclusion would also be too confident: we cannot say the added drug contributed nothing. The honest answer is that its contribution is unknown.
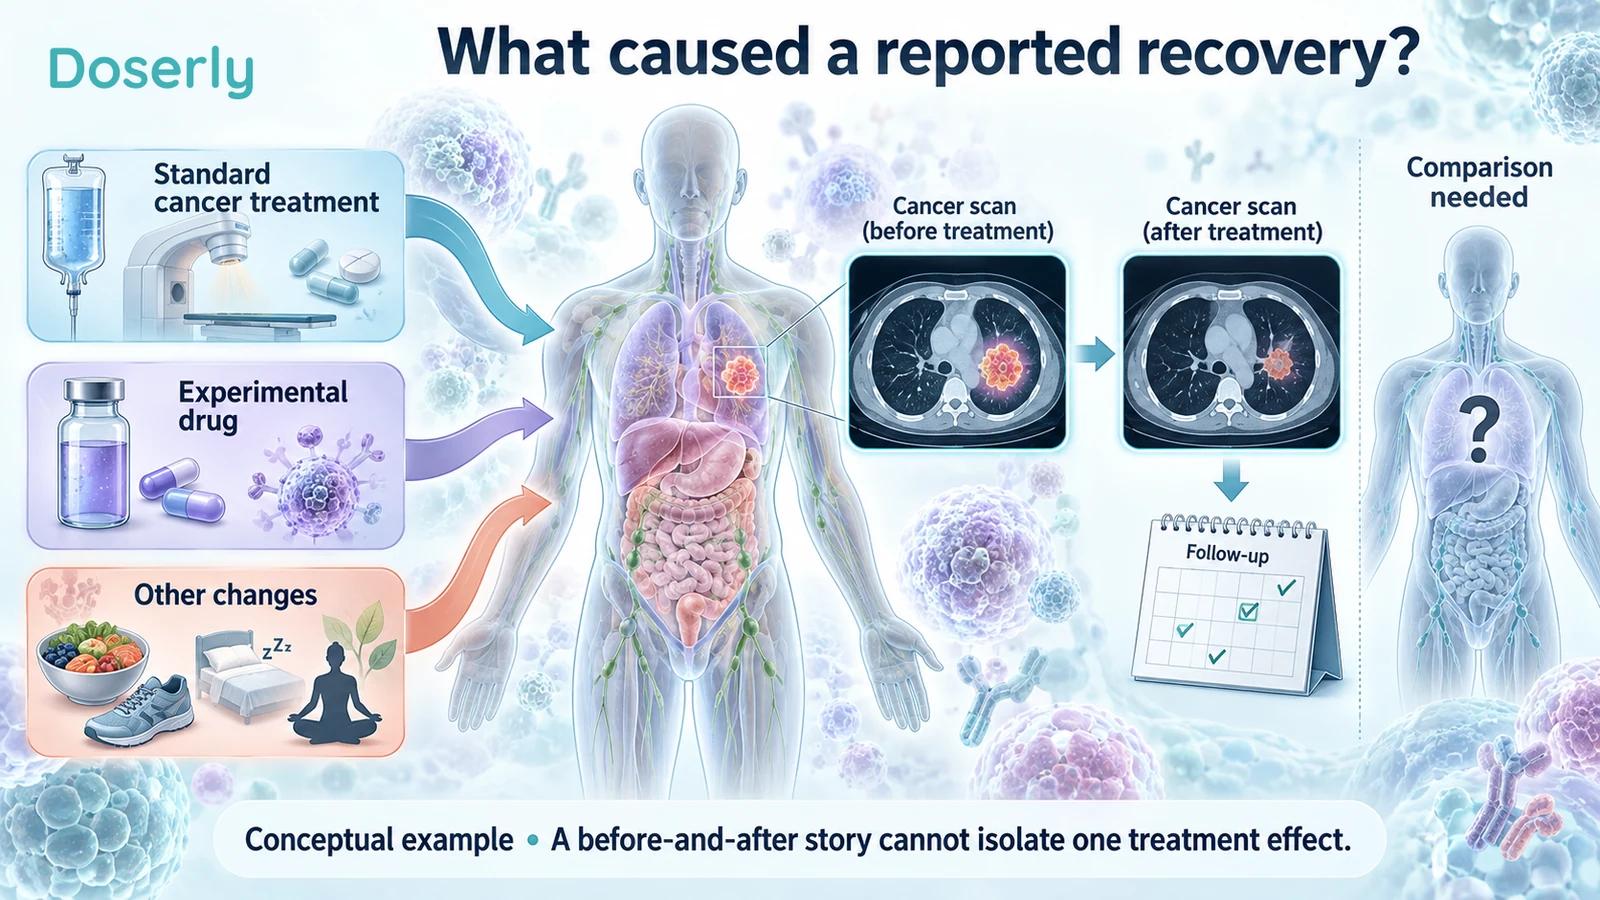
Four things make recovery stories hard to interpret:
- Delayed effects of real treatment. Immunotherapy responses can appear months after starting and can be long-lasting. Radiation and chemotherapy effects can also continue after treatment ends. A drug added later can collect the credit.
- Natural variation. Some cancers, including certain lymphomas, melanomas and kidney cancers, can occasionally shrink on their own. Slow-growing cancers can stay stable for long periods.
- The missing denominator. If ten compelling stories are shared, how many people tried the same thing without improving? How many stopped because of side effects, or died before they could post an update?
- Repetition. The same patient's story can circulate through a podcast, an X post, a newsletter and a case-series discussion. Four links may describe one person.
A stronger case report provides a confirmed diagnosis, dates, pathology, scan reports, all concurrent treatments, the reason each treatment changed, side effects and adequate follow-up. Independent review makes the account easier to assess. It still lacks the comparison that a controlled study provides.
This is not a reason to be cold toward patients or families. It is a reason to protect them from having their experience turned into a promise for someone else.
Reported recoveries, and the accounts that went the other way
There are accounts worth reading beyond the best-known podcast clips. Some appear in medical journals, some are told by clinicians, and others come directly from patients or families. The examples below describe what each source reports. They are not independently verified, and they should not be added together into a success rate.
Kathleen Ruddy's accounts: three different kinds of improvement
In a May 2024 interview, breast surgeon Kathleen Ruddy describes three patients whose experiences led her to investigate ivermectin. Ruddy's original interview
- Metastatic prostate cancer: Ruddy reports a large PSA reduction and improved functioning after ivermectin in a man previously treated with radiation, chemotherapy and hormone suppression. Bone lesions remained at the early assessment; later, some reportedly disappeared while others stayed stable. A falling PSA is encouraging, but it is not the same as all cancer disappearing.
- Esophageal cancer: She describes an older man who declined chemotherapy and radiation, then reportedly regained weight and swallowing ability and had a later scan without visible tumors after ivermectin. This is a striking account, but the interview does not provide pathology and imaging records that others can assess.
- A pelvic tumor with reported liver spread: Surgery removed the large pelvic mass before ivermectin. A later liver ultrasound was reportedly clear. This cannot be described as ivermectin making the original tumor operable.
A family account on City of Hope's fundraising platform
A fundraising page supporting Peter Lee's research tells Jacquie's story of metastatic triple-negative breast cancer. Her family reports survival exceeding three years after an initially very short prognosis, with an antibody-drug conjugate (a cancer medicine that delivers chemotherapy through an antibody) plus ivermectin. They believe ivermectin helped. The page reports longer-than-expected survival, not a documented cure, and the antibody-drug conjugate is an essential part of the history. Read the family's account
A Reddit account of no evidence of disease
In a public pancreatic cancer thread, a caregiver reports that her husband's PET scan showed no evidence of disease after about a year of treatment that included chemotherapy, a NanoKnife procedure (a technique that destroys tumor tissue with electrical pulses), ivermectin, fenbendazole and other additions. She describes the result as a miracle and credits looking beyond standard care. Because several treatments were combined, the thread cannot show which one was responsible, and it does not establish a lasting cure. Read the original post and discussion
A Substack story whose full text changes the headline
The "Fenbendazole Can Cure Cancer" newsletter, written by William Supple, a neuroscience PhD who describes himself as not an oncologist or medical doctor, maintains an archive of patient accounts. One describes a 66-year-old man with inoperable metastatic esophageal cancer who reported no evidence of disease after taking fenbendazole and other substances. Although the subtitle says there was no chemotherapy or radiation, the patient's own account names fluorouracil and Herzuma, a brand of the targeted cancer drug trastuzumab. Treatment described as palliative can still shrink cancer and extend life. Read the original account, NCI on trastuzumab, NCI on advanced esophageal cancer treatment
The newsletter's case-report archive can provide leads. Its cure language is the publisher's interpretation, not a conclusion from an independently reviewed registry. Supple has also published a 2026 book, Cancer Is a Parasite.
What about an inoperable cancer becoming operable?
If treatment allows a surgeon to remove a tumor that previously could not be removed, it may change the patient's options substantially. But becoming eligible for surgery, completing surgery and being cured are three different claims.
A May 2026 Makis newsletter headline reports that a woman with pancreatic cancer became operable after three months involving ivermectin and fenbendazole. The public headline does not supply the treatment history, serial scans, surgical assessment or confirmation that an operation occurred. Makis's reported operability account
For pancreatic cancer, surgical eligibility depends on involvement of nearby blood vessels, distant spread and whether the person can tolerate an operation. Established chemotherapy before surgery can itself make some tumors operable. The most useful documentation would show what initially prevented surgery, every treatment given, what changed on imaging, the surgeon's reassessment and, if surgery occurred, the pathology report. NCI on pancreatic cancer stages and resectability, NCI pancreatic cancer treatment summary
Accounts with mixed or negative outcomes
Stories of disappointment and harm are shared less often and travel less far. They belong in the picture too.
- Kim Chul-min, described above, publicly reported rising liver readings and cancer spread, urged patients to stop, and died in 2021.
- A gastric cancer patient on Reddit took a commercial ivermectin and mebendazole product before treatment, developed drug-induced liver injury and had chemotherapy delayed. Read the thread
- A man with prostate cancer on Reddit saw his PSA fall slightly, from 19 to 16, but developed severely abnormal liver tests and blurred vision, stopped, and chose surgery. Read the thread
- A pancreatic cancer caregiver reported tumor shrinkage on chemotherapy plus both drugs and said it may well have been the chemotherapy. Read the thread
- A parent whose daughter died before she could start fenbendazole describes regret at not trying it, a reminder of how strong the pull of these stories is when options run out. Read the thread
Recovery accounts at a glance
Account
Joe Tippens, lung
- Source type
- Personal blog
- Other treatment at the time
- Immunotherapy trial after chemoradiation
- Reported outcome
- No detectable disease for years
- What is missing
- Trial records, comparison
Account
Kim Chul-min, lung
- Source type
- Public statements, news
- Other treatment at the time
- Chemotherapy, radiotherapy
- Reported outcome
- Liver readings rose, cancer spread; died 2021
- What is missing
- Medical records
Account
Chiang series, three cases
- Source type
- Case series
- Other treatment at the time
- Nivolumab; chemotherapy; resection plus chemotherapy
- Reported outcome
- Improved imaging
- What is missing
- Comparison; independent review
Account
Ruddy, prostate
- Source type
- Clinician interview
- Other treatment at the time
- Prior radiation, chemotherapy, hormone suppression
- Reported outcome
- PSA fall, some lesions resolved
- What is missing
- Assessable records
Account
Ruddy, esophageal
- Source type
- Clinician interview
- Other treatment at the time
- Declined chemotherapy and radiation
- Reported outcome
- Regained weight; later clear scan
- What is missing
- Pathology and imaging
Account
Jacquie, breast
- Source type
- Family fundraising page
- Other treatment at the time
- Antibody-drug conjugate
- Reported outcome
- Survival beyond three years
- What is missing
- Medical records
Account
Reddit, pancreatic
- Source type
- Caregiver post
- Other treatment at the time
- Chemotherapy, NanoKnife, supplements
- Reported outcome
- No evidence of disease on PET
- What is missing
- Records, follow-up
Account
Ben Fen archive, esophageal
- Source type
- Newsletter
- Other treatment at the time
- Fluorouracil, trastuzumab
- Reported outcome
- No evidence of disease
- What is missing
- Complete timeline
Account
Cheng and Araujo, melanoma
- Source type
- Peer-reviewed case report
- Other treatment at the time
- None
- Reported outcome
- Early response, then progression
- What is missing
- Not applicable; well documented
Account
Reddit, gastric
- Source type
- Patient post
- Other treatment at the time
- None yet
- Reported outcome
- Liver injury, chemotherapy delayed
- What is missing
- Records
Account
Reddit, prostate
- Source type
- Patient post
- Other treatment at the time
- None
- Reported outcome
- Small PSA fall, liver injury, stopped
- What is missing
- Records
Podcasts, videos and the people behind them
Popular interviews can explain why an idea interests people and make complicated biology easier to follow. It helps to separate the speaker's proposed mechanism, their reading of the published evidence, and any patient outcomes they describe. It also helps to know who the speaker is and whether they sell anything related.
Joe Rogan Experience #2254 with Mel Gibson
In the January 9, 2025 episode, around 1:37:30, Gibson describes three friends with stage IV cancer who he says no longer had cancer, connecting their stories with ivermectin, fenbendazole and other substances. The episode does not supply medical records, treatment histories or follow-up. Its reach explains why patients now bring these medicines into oncology appointments. Science Feedback and Canadian fact-checkers reviewed the claim, and the Canadian Cancer Society publicly called it dangerous. Watch the original episode near the discussion, Science Feedback, Canadian Press fact check
William Makis: DTV episode 162, John Campbell and Makis Medicine
William Makis is the most prominent online advocate for these drugs in cancer. The College of Physicians and Surgeons of Alberta states that he has not held an active licence to practise medicine there since 2019, and in March 2026 it obtained a permanent court injunction that bars him from offering advice or consultations regarding cancer treatment and from calling himself a doctor or oncologist. CPSA statement
In DTV episode 162 (October 6, 2026), Makis describes patient experiences and argues for repurposed drugs, including in combination with conventional treatment. He also acknowledges people who did not respond, says much of the data is not yet there, and says patients should remain with their oncology teams. His estimates are not accompanied by an independently assessed dataset. Cohost Todd Pitner describes taking ivermectin for prostate cancer and later undergoing prostate surgery; the surgery is an essential part of that story. DTV episode 162
"Repurposed drugs for cancers," hosted by John Campbell, is a longer discussion with Makis. Campbell, a retired nurse educator with a very large audience, later promoted the now-retracted ivermectin and mebendazole survey in "Ivermectin and mebendazole, 84% benefit in cancer." Watch Campbell and Makis, Campbell's 2026 video
Makis also shares individual treatment stories on X and Substack. These can identify claims worth investigating, but a social post is not an independently reviewed record, and the same patient may appear in several places. Makis Medicine on X, Makis on Substack
Clinicians explaining the evidence on video
- Talking Cancer with Dr. Roman covers each drug separately, which helps keep the evidence apart: ivermectin, fenbendazole, a follow-up answering viewer comments on fenbendazole and mebendazole.
- Jay Chaplin's July 2026 live Q&A, with a September 2026 written summary, focuses on whether laboratory concentrations are achievable in people and whether improvements could reflect earlier treatment. Watch the discussion, read the summary
- Pacific Northwest Urology Specialists reviews new preclinical fenbendazole data and the claims made about it. Watch the video
- Lisa Jackson Broyles presents the ivermectin research as preliminary. Watch the video
Integrative and advocate perspectives on video
- Paul Anderson, a naturopathic doctor, covers repurposing, proposed roles, combinations and risks. Watch Anderson's explainer
- Micah Yu, a rheumatologist, covers both compounds and links to a mechanism review. Watch Yu's video
- The Cracking Cancer Podcast explains how ivermectin is thought to work. Watch the episode
- Dr. Dino Prato, a naturopathic doctor, discusses fenbendazole, mebendazole and ivermectin together. Watch the episode
For any promising result mentioned in a video, follow the reference far enough to find out whether it came from cells, animals or people.
Paul Marik, Pierre Kory and the Independent Medical Alliance
Paul Marik's Cancer Care monograph, published through the Independent Medical Alliance (formerly the FLCCC, which promoted ivermectin for COVID-19), assembles research on repurposed drugs, nutrition and metabolic approaches. The October 2024 edition gives ivermectin and benzimidazoles strong recommendations while acknowledging limited clinical evidence. The useful contribution is that it makes the rationale explicit. The important question is whether the strength of a recommendation matches the strength of the human evidence. Marik's Cancer Care resource page and free monograph, IMA Cancer Resource Hub
The July 24, 2026 guide deserves close reading. It states that some rankings were generated using AI, that head-to-head studies have not been conducted and that the analyses are not fully transparent. Its ranked lists are therefore not clinical comparisons showing one medicine is safer or more effective than another. Marik's updated guide
Pierre Kory, a critical care physician, co-wrote The War on Ivermectin with Jenna McCarthy, a book about COVID-era medicine and institutions rather than cancer. On his Substack he has described his move into cancer care and published a five-patient lung cancer series from his own practice, which is not peer-reviewed. His clinic offers repurposed-drug cancer care. Publisher's book page, Kory on cancer, Kory's lung cancer series
Questions about incentives and the funding of generic-drug research are legitimate. A financial incentive can influence what gets studied, but neither a drug's low price nor a dispute with an institution supplies the missing clinical outcome data. The same disclosure standard applies to everyone: academic researchers, drug companies, supplement sellers and clinicians offering consultations.
Where the experts actually disagree
The disagreement is not between people who have a large positive trial and people who are hiding it. Nobody has that trial. The disagreement is about what to do while the evidence is incomplete. Three broad positions exist, and each would change its mind in response to different evidence.
Position 1: Use them now, alongside standard care
- Who holds it: Paul Marik and the Independent Medical Alliance, Pierre Kory, William Makis and Joe Tippens.
- Core reasoning: The drugs are cheap and widely used, the proposed mechanisms are plausible and the anecdotes are encouraging. Waiting years for trials, in this view, costs lives.
- What would change their mind: Well-run trials showing no benefit, or clear evidence of harm.
The reasoning and disclosures for each of these advocates are covered in the podcasts and books section above.
Position 2: Worth testing, but only in trials or with monitored, informed consent
- Who holds it: The Anticancer Fund, radiation oncologist Brian Lawenda, and the investigators running the City of Hope, Cedars-Sinai and ICONIC research.
- Core reasoning: The scientific rationale is real, but drug exposure, interactions and benefit in people are unknown, so the priority is to collect data properly.
- What would change their mind: Positive controlled trials would move them toward use; clear harm signals would move them away.
Brian Lawenda's April 2026 essay is a good example. He acknowledges the preclinical rationale, separates the drugs, and is open to selected, monitored use while firmly rejecting replacement of established treatment. Read Lawenda's evidence discussion
The Anticancer Fund, a charity that actively champions repurposed drugs, still states that the human trials are missing. Its free My Cancer Navigator service will summarize the evidence and interaction risks for a specific drug and situation. Anticancer Fund
Position 3: Do not use them outside clinical trials
- Who holds it: ASCO, the American Cancer Society, the Canadian Cancer Society, Macmillan Cancer Support and Science-Based Medicine.
- Core reasoning: There is no proven benefit, there are documented harms and interaction risks, and unproven treatment can displace effective care.
- What would change their mind: Replicated controlled trials showing benefit.
ASCO's notice is the clearest statement of this position. It says the drugs "should not be used for the treatment of cancer, nor as an adjunct to established cancer therapies, outside the regulatory safeguards of a well-designed clinical trial." It also urges oncologists to take a "proactive, non-judgmental approach," asking patients about use and maintaining trust, and it names the opportunity cost of displacing effective treatment as "the greatest unmeasured risk." ASCO clinical notice
The strongest critical analyses come from McGill's Office for Science and Society and from Science-Based Medicine, where surgical oncologist David Gorski and retired surgeon David Weinberg have written about both drugs and the retracted survey. Their tone is openly combative, but their reference checking is thorough. McGill OSS, Gorski on fenbendazole, Weinberg on ivermectin and mebendazole
Does the metabolic explanation make these combinations more convincing?
Cancer metabolism is a real and active research field. Cancer cells need energy and raw materials to build new cells, and changes in glucose use, mitochondrial activity and other metabolic processes can create treatment targets.
The oversimplification is to treat all cancers as though they depend on one fuel and can be reliably starved by one diet or medicine. Cancer cells differ in what they use, and their behavior changes with their environment. Normal tissues depend on many of the same nutrients and pathways.
Thomas Seyfried's interview with The Moss Report explores glucose, glutamine and antiparasitic drugs from a metabolic perspective. One paper linked with the episode tested a calorie-restricted ketogenic diet with the glutamine-targeting compound DON in mouse glioblastoma models and reported favorable results. That supports studying a specific metabolic strategy. It does not establish that ivermectin or fenbendazole reproduces the same effects. Watch Seyfried's interview, read the primary 2019 experiment Jane McLelland's book How to Starve Cancer, which includes mebendazole among its "metabolic blockers," has built a large following on similar reasoning. How to Starve Cancer
A June 2026 study shows both the interest and the limits. Researchers combined ivermectin with recombinant methioninase, an enzyme that breaks down the amino acid methionine, in one colon cancer cell line for 72 hours. They reported a larger effect on cell viability than with four of five chemotherapy and methioninase combinations. The authors identified the single-cell-line design as a limitation. It supports further laboratory work, not a claim that ivermectin outperforms chemotherapy in people. Kim et al., Frontiers in Oncology, 2026
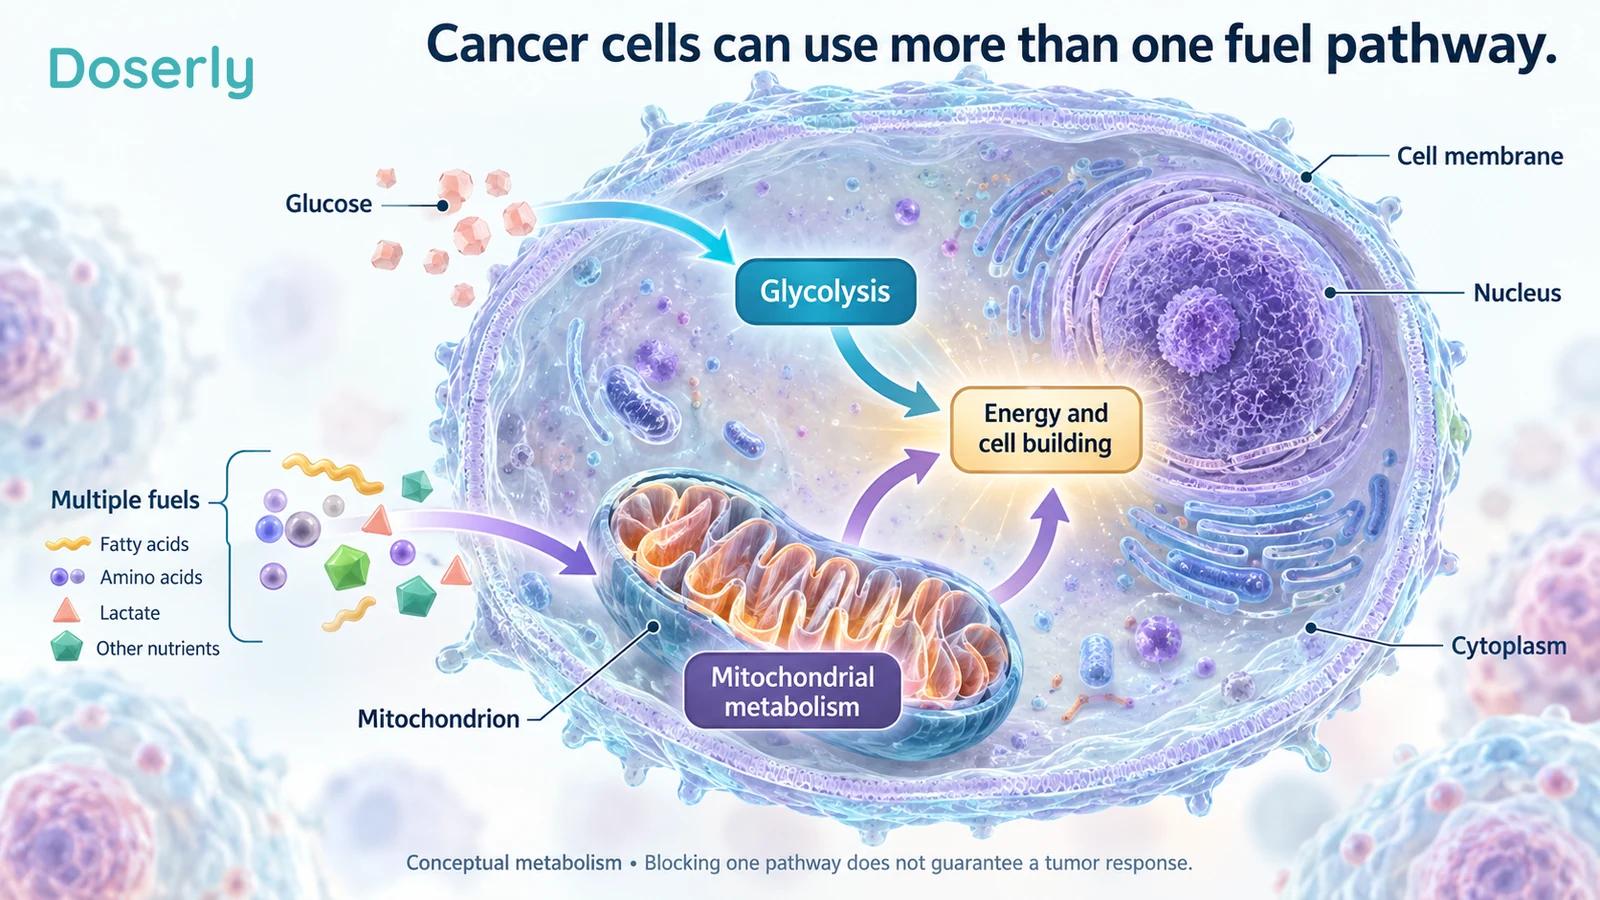
This matters particularly when a person is losing weight or muscle during treatment. Aggressive dietary restriction is not automatically helpful because it is described as metabolic therapy. Maintaining strength and adequate intake can be an important part of care. NCI on nutrition in cancer care
Safety: what "well tolerated" leaves out
Ivermectin
Ivermectin has an outstanding safety record at the doses used for parasites. The Mectizan Donation Program has supplied more than 5.9 billion treatments since 1988, typically as single annual doses. The American Cancer Society puts it well: ivermectin "is safe if taken at the recommended dose to treat a worm infection. That doesn't mean it's completely safe in all situations." Mectizan Donation Program 2024 highlights, American Cancer Society on ivermectin
Cancer use is different: daily doses for months, often above label amounts, frequently combined with other drugs. Published reports describe the consequences:
- A woman with metastatic breast cancer developed seizures and respiratory failure requiring a ventilator after taking ivermectin. Saperstein et al., Postgraduate Medicine, 2026
- A child being treated for cancer developed ivermectin toxicity, described by the treating team as a consequence of medical misinformation. Pediatric Blood and Cancer, 2025
- Poison centers recorded confusion, unsteadiness and other neurological effects in people who took ivermectin daily for weeks to prevent or treat COVID-19, sometimes at ordinary doses. Temple et al., New England Journal of Medicine, 2021
- A systematic review of higher-than-standard doses found only six eligible studies and concluded there was not enough data to support using doses above those approved. Navarro et al., 2020
The label also lists neurological adverse reactions and rare reports of increased INR with warfarin. Ivermectin is processed mainly by the liver enzyme CYP3A4 and is both moved and blocked by P-glycoprotein, the same systems that handle many oral chemotherapy and targeted cancer drugs. Stromectol safety information, Rendic, Archives of Toxicology, 2021
Fenbendazole and the liver
Fenbendazole has no established human dosing or safety framework. The NIH's LiverTox database now has a fenbendazole entry stating that it commonly causes mild liver enzyme rises and can cause clinically apparent acute liver injury. LiverTox: fenbendazole
At least six human cases have been published:
- 2021: liver injury in a woman with lung cancer receiving pembrolizumab, improving after fenbendazole was stopped. Yamaguchi et al., Case Reports in Oncology, 2021
- 2024: severe liver injury with biopsy findings, with recovery after stopping. Severe fenbendazole-associated liver injury report
- 2025: cholestatic liver injury in Norway that initially looked like an immunotherapy reaction. Skaara et al., 2025
- 2026: a 47-year-old woman with metastatic colon cancer on nivolumab and relatlimab developed liver injury after increasing her own fenbendazole dose; once fenbendazole was identified as the probable cause, her immunotherapy was safely restarted. Krishnan et al., World Journal of Clinical Cases, 2026
- 2026: severe liver injury, rated highly probable, in a man taking veterinary fenbendazole and ivermectin for prostate cancer. Powderly et al., Cureus, 2026
- 2026: liver injury at the widely promoted dose of 222 mg a day, despite also taking a supplement marketed for liver protection. Satinsky et al., 2026
Case reports cannot tell us how common an adverse event is, but they establish a clear warning signal. They also show a specific danger for people on immunotherapy: fenbendazole liver injury can look like an immune reaction to the cancer drug, which can lead to unnecessary steroids or interrupted treatment.

An abnormal liver test should not be explained away as a sign that a tumor is being destroyed. Possible causes include drug injury, infection, bile duct blockage, cancer involvement and immune-related complications.
Yellowing of the eyes or skin, dark urine, severe abdominal symptoms, new confusion, trouble walking, vision changes or marked drowsiness warrant prompt medical advice; severe or rapidly worsening symptoms warrant urgent care. Bring the actual product names, packaging and a record of what was taken.
Product quality and combinations
Products sold online vary widely. Patients describe using livestock paste and receiving mislabelled fenbendazole. The FDA has issued a warning letter to a clinic selling fenbendazole kits with late-stage cancer claims, and Health Canada has seized ivermectin from a British Columbia seller claiming it heals cancer. FDA warning letter, Health Canada seizure
A list of individually familiar products is not a tested combination. Drugs and supplements can share effects on the liver, bleeding or the nervous system, and can change exposure to cancer drugs. NCI specifically advises discussing supplements and complementary products with the treatment team. NCI on cancer-treatment interactions
The largest measured risk: replacing treatment
The best-documented harm in this area is not a side effect. In a US study of people with curable cancers, those who chose alternative medicine instead of standard treatment had about two and a half times the risk of death. A companion study found that the extra risk among people using complementary medicine was explained by their being more likely to refuse standard treatment. Johnson et al., Journal of the National Cancer Institute, 2018, Johnson et al., JAMA Oncology, 2018
"It might not help, but it can't hurt": the case for and against a hybrid approach
One of the most common arguments for these drugs is not that they are proven, but that they are cheap, widely used and unlikely to cause harm, so why not take them alongside standard treatment? The argument is sharpest for people waiting weeks or months for surgery. On DTV episode 162, Makis describes breast cancer patients facing a three-to-five-month wait who began ivermectin and mebendazole in the meantime because they could not "just sit around and wait for the tumor to get bigger." He presents these as anecdotes.
The instinct behind this is reasonable. Delay does matter: across 34 studies, each four-week delay in cancer surgery was associated with roughly a 6 to 8 percent higher risk of death, with larger effects for some treatments. Wanting to act during that time is not irrational, and feeling some control over your care has value of its own. Hanna et al., BMJ, 2020
The question is whether each part of the argument holds up.
"It's low risk"
At the doses used for parasites, ivermectin's record supports this. But those are usually single doses. Cancer protocols often use daily doses for months, and published reports now describe seizures, respiratory failure and liver injury in people with cancer who were self-treating. Fenbendazole has never been studied for safety in people. "Low risk" is established for a short antiparasitic course, not for the way these drugs are being used against cancer.
"It won't interfere with my treatment"
Immunotherapy antibodies are not broken down by liver enzymes, so classic drug interactions with them are less likely. Many oral chemotherapy and targeted drugs do share ivermectin's CYP3A4 and P-glycoprotein pathways. Even without a direct interaction, side effects can disrupt care: in published cases, fenbendazole liver injury was mistaken for an immunotherapy reaction and treatment was interrupted. The ICONIC trial exists partly to rule out that ivermectin weakens the immune response.
Supplements often bundled into these protocols raise their own questions. In a large breast cancer trial, people taking vitamin B12 before and during chemotherapy had worse disease-free and overall survival, and those taking iron had more recurrences. Antioxidant use showed a similar but not statistically significant trend. Ambrosone et al., Journal of Clinical Oncology, 2020
"Something is better than nothing while I wait"
The evidence on delay supports shortening the wait, not filling it with an untested drug. No trial has tested these drugs as a bridge to surgery, and a tumor that measures smaller on a later scan can reflect differences in imaging as well as real change. Better options exist:
- Ask whether the wait can be shortened. Another surgeon or center may operate sooner, and for many cancers, including many breast cancers, chemotherapy or hormonal therapy can start before surgery.
- Prehabilitation. In a randomized trial, four weeks of structured exercise, nutrition and psychological support before colorectal cancer surgery cut severe complications from 29.7 to 17.1 percent. This is a "do something" option with proof behind it. Molenaar et al., JAMA Surgery, 2023
- Window-of-opportunity trials. These give a promising drug in the gap between biopsy and surgery, then compare tumor tissue before and after. Metformin, another repurposed drug, has been studied this way in breast cancer. This design is exactly how the waiting-period question should be answered, and it is worth asking whether one is open nearby. Maugeri-Saccà et al., 2016, Hadad et al., 2011
"If it doesn't work, nothing is lost"
Some costs are hidden. The American Cancer Society notes that taking ivermectin for a non-approved use could disqualify you from a clinical trial, and trial protocols commonly prohibit any unlisted anticancer therapy. A good scan during combined treatment can be credited to the wrong thing, and that belief can later lead someone to decline treatment that was actually working. Consultations and products also cost money. And as described above, skipping effective care is where the measured mortality risk sits. American Cancer Society on ivermectin
Where that leaves a hybrid approach
Some clinicians, including Lawenda, accept carefully monitored use alongside standard care for patients who are determined to try. Most oncology organizations, including ASCO, do not. If you are considering it, the safest version is transparent rather than hidden:
- Tell your oncologist and pharmacist before starting. Between 20 and 77 percent of people using complementary treatments do not tell their doctors, most often because nobody asked. Davis et al., The Oncologist, 2012
- Never delay, reduce or replace recommended treatment.
- Have the complete list, including supplements, checked for interactions.
- Check clinical trial eligibility first.
- Get liver tests before and during use, and agree in advance on what result or symptom means stopping.
- Avoid veterinary products.
- Change one thing at a time and keep a dated record of products, doses, symptoms and test results.
- Read a good result honestly: when several treatments are given together, a scan cannot tell you which one worked.
Access, funding and public interest
Access is changing faster than evidence. Several US states, including Tennessee, Arkansas, Idaho, Louisiana and Texas, have passed laws allowing ivermectin to be sold or dispensed without a traditional prescription, although many pharmacies remain reluctant. Louisiana's legislature has also asked its surgeon general to assess fenbendazole, noting that the human evidence is limited to case reports and observational data. Easier access changes availability, not the evidence, and makes a pharmacist's interaction check more important. NPR via OPB, March 2026, Louisiana House Resolution 174
Public funding is also arriving, and it is often misdescribed. In January 2026, the director of the National Cancer Institute announced a laboratory study of ivermectin, not a clinical trial; no results had been published by October 2026. KFF Health News Florida's Cancer Innovation Fund awarded three ivermectin projects about 3.4 million dollars in total, for lung, ovarian and prostate cancer research, out of a 60 million dollar program. Descriptions of the entire program as ivermectin money overstate it. Florida grantee list, period 1, period 2, period 3
Funding a project shows that someone considers a question worth investigating. It is not evidence that the treatment has already worked.
What counts as a meaningful cancer outcome?
The words used in an interview or headline can change how impressive a result sounds.
Response usually refers to a defined reduction in measurable disease. Complete response means the detectable signs assessed under the criteria have disappeared; that is not automatically a permanent cure. Stable disease means the measurements have not met the thresholds for shrinkage or progression during the assessment interval. NCI definitions of response, complete response, stable disease
Progression-free survival is time without the cancer worsening, with death also counted. Overall survival is how long people remain alive. Quality of life is how they feel and function. A treatment may affect these differently. NCI on progression-free survival, overall survival

A smaller finding on one scan may be encouraging, but several questions remain. Was it measured consistently? Were other lesions assessed? Was the change sustained? Did the person live longer or feel better? Likewise, a falling tumor marker such as PSA or circulating tumor DNA can be useful without being sufficient proof of benefit on its own, as the melanoma case above shows.
What would make the evidence more convincing?
For ivermectin, the next step is complete reporting from the breast cancer trial and results from ICONIC: who enrolled, what exposure was achieved, what side effects occurred and how tumors behaved. If there is a credible signal, a randomized trial comparing standard treatment with and without ivermectin would answer the question patients care about.
For fenbendazole, basic human pharmacology and safety studies would need to come first. For mebendazole, an independent replication of the positive colorectal trial would be the most valuable single study.
Stronger studies share several features:
- A clearly defined cancer type, stage and prior-treatment history.
- A prospectively registered plan with outcomes specified before results are known.
- A complete account of everyone enrolled, including withdrawals and missing follow-up.
- Confirmed diagnoses and independently assessed outcomes where feasible.
- A comparison that can distinguish the experimental drug's contribution.
- Ethics approval, transparent adverse-event reporting, declared conflicts of interest and accessible data.
- Enough follow-up to assess durability, survival and quality of life.
None of these guarantees a positive result. They make a result interpretable, and they protect a genuinely useful treatment from being judged only through enthusiastic anecdotes or poorly designed studies.
A useful conversation with your oncology team
You should be able to ask about these drugs without being dismissed, and ASCO now explicitly asks oncologists to raise the subject without judgment. A good discussion can acknowledge both the wish to explore every reasonable option and the uncertainty in the evidence.
Bring the specific study or episode that interested you, rather than only its headline. Ask what it tells us about your cancer type and current treatment. If a clinician says the evidence is insufficient, it is reasonable to ask which result would change that assessment.
Useful questions include:
- Does this study involve people with my diagnosis and treatment history?
- What benefit is already expected from my current treatment, and over what time frame?
- Is there a clinical trial I might qualify for, including trials unrelated to these drugs?
- Could a proposed medicine or supplement interact with my treatment or affect trial eligibility?
- If I am waiting for surgery or treatment, can it start sooner, and would prehabilitation help?
- How would we distinguish disease progression, treatment toxicity and an unrelated problem?
- What symptoms should prompt a call, and who should I contact after hours?
- What can we do now to improve pain, appetite, sleep, strength and daily function?

If you have already taken an experimental product, tell the team what it was and when you took it. The purpose is to make your care safer, not to judge you. Keeping an accurate medication and symptom record is useful, but a tracking app cannot determine whether a treatment is effective or safe.
Seeking a second oncology opinion can also be reasonable. The most helpful opinion explains the evidence, the likely benefits and the tradeoffs for your situation. For an independent evidence summary on a specific drug, the Anticancer Fund's My Cancer Navigator is a useful free option.
Where PNC-28 and other peptide research fit
PNC-28 is another experimental anticancer approach, not a proven companion treatment. It is a synthetic peptide studied for effects on cancer-cell membranes, and a 2006 paper reported inhibition of pancreatic tumor growth in mice. PNC-28 animal study Our PNC-28 guide and the related PNC-27 guide explain the proposed biology and its limits. Neither supplies evidence that combining these peptides with ivermectin or fenbendazole improves outcomes.

Prostamax is sometimes mentioned in prostate discussions, but prostate symptoms, benign enlargement and cancer are different conditions. Our Prostamax guide describes its limited evidence. There is no strong basis for presenting it as a cancer treatment.
Frequently asked questions
Does ivermectin cure cancer?
No study has shown that it does. It has laboratory activity, small human reports, and early results from one small trial in which 1 of 8 evaluable patients had a partial response. A randomized trial is due to open in late 2026.
Does fenbendazole cure cancer?
There is no clinical trial of fenbendazole in cancer. The evidence consists of laboratory and animal studies, several of them negative, and individual case reports, most involving other treatment. At least six cases of liver injury have been published.
What is the Joe Tippens protocol?
It is the regimen Joe Tippens describes following after his 2017 lung cancer recovery: fenbendazole with supplements such as CBD and curcumin. He was also enrolled in an immunotherapy trial at the time, so his recovery cannot be attributed to fenbendazole. The promoted dose has been linked to at least one published case of liver injury.
Is fenbendazole the same as mebendazole?
No. They are related benzimidazoles, but mebendazole is approved for humans and has been tested in cancer trials, with mixed results. Fenbendazole is a veterinary drug with no human trials. Results from one cannot be transferred to the other.
Is fenbendazole safe for humans?
Its safety in people has never been formally studied. The NIH's LiverTox database reports that it commonly raises liver enzymes and can cause clinically apparent liver injury.
Can I take ivermectin with chemotherapy or immunotherapy?
ASCO advises against it outside a clinical trial. Ivermectin shares liver and transport pathways with many oral cancer drugs, side effects can be mistaken for treatment reactions, and use can affect trial eligibility. If you are considering it, discuss it with your oncologist and pharmacist first.
What did Mel Gibson say on Joe Rogan?
In January 2025, Gibson said three friends with stage IV cancer no longer had cancer after using ivermectin, fenbendazole and other substances. No medical details were provided. Prescriptions for these drugs among people with cancer rose afterward.
Are there clinical trials I can join?
The ivermectin breast cancer trial (NCT05318469) is recruiting at Cedars-Sinai, and the ICONIC trial (NCT07487805) is expected to open in late 2026. NCI's clinical trial search lists these and many other trials. NCI clinical trial search
The conclusion the evidence supports today
There are scientifically interesting reasons to study ivermectin and fenbendazole in cancer. The laboratory findings are not all imaginary, and patients' experiences should not be ridiculed. The available human evidence still does not justify presenting either drug as an established cancer treatment or a proven add-on to standard care, and the "nothing to lose" argument underestimates real risks.
The most constructive position is open to better evidence and careful about what is claimed now. That means supporting good trials, reporting negative findings, updating older sources after corrections or retractions, and keeping patients' actual outcomes ahead of the popularity of a story.
For someone facing cancer today, the aim is to preserve options and make decisions with the best available information. Hope and accuracy belong in the same conversation.
Resources: studies, organizations, podcasts and communities
Evidence summaries and professional positions
- ASCO clinical notice on ivermectin and fenbendazole
- American Cancer Society on ivermectin and fenbendazole
- Macmillan Cancer Support on ivermectin
- NIH LiverTox entry on fenbendazole
- NCI on cancer-treatment interactions
Pro-repurposing but evidence-first
- Anticancer Fund: separating fact from fiction, including its free My Cancer Navigator service
- ReDO project review of mebendazole
- Brian Lawenda's evidence discussion
Critical analysis and fact checks
- McGill Office for Science and Society: Ivermectin for Cancer Is Putting the Cart Before the Horse Paste
- Science-Based Medicine on fenbendazole, ivermectin and the retracted survey
- Science Feedback on ivermectin preclinical studies and Mel Gibson's claim
- Full Fact on fenbendazole
- The Skeptic: Ivermectin is a genuinely great drug, but there's no good evidence it can treat cancer
- MedShadow: why so many people believe ivermectin cures cancer
Advocate resources
Read these alongside the disclosures described earlier in the article.
- Independent Medical Alliance Cancer Resource Hub and Paul Marik's Cancer Care monograph
- Pierre Kory's Substack on cancer
- Joe Tippens's protocol page
- William Makis on Substack and on X
- Jane McLelland, How to Starve Cancer
- Justus R. Hope's Substack, author of Surviving Cancer, COVID-19, and Disease
- Fenbendazole Can Cure Cancer (Ben Fen) newsletter
Clinical trials
- NCT05318469: ivermectin with immunotherapy in triple-negative breast cancer
- NCT07487805: ICONIC randomized ivermectin trial
- NCI's clinical trial search
Podcasts and videos
- The Joe Rogan Experience #2254 with Mel Gibson
- DTV episode 162 with William Makis
- John Campbell with William Makis
- Talking Cancer with Dr. Roman on ivermectin, fenbendazole and mebendazole
- The Cracking Cancer Podcast: How Does Ivermectin Work?
- Thomas Seyfried on The Moss Report
- Jay Chaplin's live Q&A on fenbendazole, ivermectin and Seyfried
- Pacific Northwest Urology Specialists on fenbendazole
- Lisa Jackson Broyles on ivermectin research
- Paul Anderson on antiparasitic drugs and cancer
- Micah Yu on ivermectin and fenbendazole
- Fenbendazole Voices podcast
Books
- Advocate and repurposing: The War on Ivermectin (Pierre Kory and Jenna McCarthy), Cancer Care (Paul Marik), How to Starve Cancer (Jane McLelland), Surviving Cancer, COVID-19, and Disease (Justus R. Hope), Cancer Is a Parasite (William Supple).
- Metabolic background: Cancer as a Metabolic Disease (Thomas Seyfried), The Metabolic Approach to Cancer (Nasha Winters and Jess Higgins Kelley).
- Critical perspective on cancer evidence in general: Malignant (Vinay Prasad) and Ending Medical Reversal (Vinay Prasad and Adam Cifu), which explains why plausible mechanisms often fail in trials.
Patient communities
Forums are valuable for the practical experience of cancer: uncertainty between scans, side effects, finding another opinion and sharing good news. When reading treatment stories there, look for every treatment given, how long ago, and whether the person posted again later.
- r/pancreaticcancer discussion of fenbendazole and ivermectin
- r/cancer: a family member taking ivermectin for cancer
- r/ProstateCancer: active surveillance and fenbendazole
- r/Oncology: how oncologists approach alternative treatment requests
- Breastcancer.org discussion of the McLelland and Care Oncology protocols