
In this guide
What is femhrt?
femhrt is a US oral fixed combination of ethinyl estradiol, or EE, and norethindrone acetate for specified menopausal treatment in a woman with a uterus. EE is a synthetic estrogen; norethindrone acetate is a synthetic progestin. The included progestin opposes estrogen’s effect on the lining under the prescribed complete regimen. This is different from estradiol plus micronized progesterone. [1]
The complete FDA reference retrieved is revised May 2023 and lists the 0.5 mg/2.5 mcg tablet. An older manufacturer PDF and old repackager entries do not certify a newer femhrt revision or all historically used strengths today. This guide treats its row as a selected FDA-label reference; current original manufacturer labeling and local marketing need another check before release. [1]
Although similar component names appear in birth-control pills, femhrt’s indication and calendar here are menopausal hormone therapy. It is not a contraception protocol and does not use contraceptive missed-pill backup rules. A separate need for contraception requires a separate clinical plan. [1], [3]
What schedule does the selected complete label describe?
| Product / country | Population / indication | Route | Amount | Schedule | Context | Source |
|---|---|---|---|---|---|---|
| femhrt · selected US FDA label | Moderate/severe menopausal VMS; restricted osteoporosis prevention; uterus | Oral fixed tablet | Norethindrone acetate 0.5 mg + EE 2.5 mcg | One daily continuously | Progestin included; latest brand revision/access pending | Label [1] |
| Jinteli · US comparison | Named menopausal VMS/bone indications; uterus | Oral fixed tablet | Norethindrone acetate 1 mg + EE 5 mcg | One daily continuously | Different named product and complete amount, not substitution instruction | Label [2] |
The femhrt row gives progestin in milligrams and estrogen in micrograms. One milligram equals 1,000 micrograms; that unit conversion is not a potency ratio between EE, estradiol or CEE. A numerically small EE amount does not itself prove less clot risk than every larger-milligram estrogen formulation. [1], [3]
The named use is one tablet every day, without a scheduled estrogen-free interval. Start, continuation and any change should be decided under the actual product leaflet and the person’s clinical needs. The Jinteli comparison explains why the same molecule names do not authorize replacing tablets or treating a historical femhrt strength as currently supplied. [1], [2]
Doserly
ORIGINAL EXPLANATORY DIAGRAM
Attach each amount to its component and unit
Selected femhrt FDA reference; current original brand check remains pending.
Norethindrone acetate
0.5 mg progestin in the selected tablet.
Ethinyl estradiol
2.5 mcg estrogen in the same tablet. Not 2.5 mg.
Complete calendar
One daily continuously. No contraceptive inert interval or verified potency conversion.
Sources checked October 2, 2026: Source 1.
Evidence note: selected May 2023 femhrt FDA reference, separate full Jinteli label. Current original femhrt revision and marketing remain pending; no cross-product equivalence supplied.
Verification scope
Named full labels and stated jurisdiction, checked October 2, 2026. Revisions are distinct from access dates. Local stock and reimbursement were not verified.
Which treatment goals are actually listed?
The selected femhrt label supports moderate-to-severe vasomotor symptoms and a restricted osteoporosis-prevention indication. It does not separately list vulvar/vaginal atrophy, contraception, depression or general cognitive protection. Relief of sweats may improve sleep; that practical benefit should be distinguished from treating every possible cause of insomnia. [1], [3]
If the only aim is osteoporosis prevention, the label reserves use for significant risk after carefully considering non-estrogen medicines. Local vaginal symptoms have their own treatment choices and evaluation. Name the problem driving the prescription so that lack of response does not lead to escalating a medicine for an unverified indication. [1], [3]
How should daily use and an omitted dose be handled?
This is an oral complete tablet, not a skin patch, injectable ester or standalone progestin. Oral exposure and interacting medicines matter even though the estrogen is measured in micrograms. Record the full pair of amounts and product name on the medication list. [1]
The selected patient leaflet says one tablet at the same time each day, but does not supply a specific missed-dose catch-up rule. Ask the pharmacist using the actual supplied product instead of borrowing Jinteli or birth-control instructions. Record omissions and associated bleeding; the menopause calendar does not create pregnancy protection. [1], [3]
What can the product trials and WHI tell you?
The femhrt label describes controlled symptom, endometrial and bone-density studies of named regimens. Study arms can include formulations beyond the one currently listed strength; a historical trial arm is not evidence of current brand inventory. The complete estrogen/progestin pair is the intervention, so adding more estrogen or replacing the progestin changes the evidence question. [1]
The label’s WHI discussion concerns oral CEE plus MPA, not a femhrt-versus-transdermal trial. Its relevance to systemic treatment risks should be kept without assigning exact WHI event rates to this EE tablet. Bone-density findings also do not prove every long-term outcome or create a cardiovascular/dementia-prevention indication. Clinical choice combines trial findings, patient history and ongoing benefit. [1], [3]
Doserly
ORIGINAL EXPLANATORY DIAGRAM
Separate molecule, label and trial history
The same ingredient name does not answer every product question.
Selected femhrt label
0.5 mg/2.5 mcg in May 2023 FDA text; later revision and supply need checking.
Jinteli comparison
1 mg/5 mcg in its separate full label. Not a substitution prescription.
WHI context
CEE/MPA trial evidence is not a precise femhrt-versus-patch risk estimate.
What contraindications and interactions remain?
The selected label contraindicates unexplained bleeding, breast or estrogen-dependent cancer, current/past venous or arterial thromboembolic disease, liver impairment/disease, relevant thrombophilia and serious allergy. A small numeric EE dose does not override those restrictions. Sudden chest pain, breathlessness, a swollen painful leg, weakness, speech difficulty or significant visual change needs urgent assessment. [1]
Headache, breast pain, abdominal symptoms and swelling can affect tolerability. Review CYP3A4 inducers/inhibitors, including relevant herbal products, and thyroid-replacement needs. Keep symptom timing clear, including effects present before the medicine. FDA’s first-six February 2026 announcement does not establish a new femhrt label or modify unrelated contraceptive labels. [1], [4]
What should the clinical review measure?
Track hot flashes and their effect on sleep/function, exact tablet, omitted doses, bleeding and unwanted effects. NICE recommends review at three months then annually, earlier for difficulties. Review of adherence and interactions can be more useful than assuming any recurrent symptom needs a higher estrogen amount. No universal blood EE target is supplied. [1], [3]
For systemic HRT, persistent unscheduled bleeding beyond six months after starting or three months after changing treatment needs prompt assessment under NICE, earlier if concerning. A progestin-containing tablet does not make bleeding automatically harmless. Imaging, screening and tests should fit the clinical question rather than an invented routine optimization panel. [1], [3]
How should stopping or switching be arranged?
NICE permits gradual reduction or immediate stopping of MHT. Symptoms can recur, and a fixed tablet changes estrogen and progestin together. Do not treat opening, splitting or alternate-day use as a verified equivalent regimen without the actual prescriber/pharmacist advice. Serious suspected reactions require prompt assessment. [1], [3]
A switch to estradiol does not follow a microgram-to-milligram potency formula. Name the new route, estrogen amount and protection plan with a uterus before changing. Reassess whether local vaginal therapy or another bone-prevention option should continue for separate goals. The source-access gap in this guide is another reason to use the current supplied leaflet. [1], [3]
How is the selected US tablet stored?
The FDA reference specifies 20–25°C with permitted excursions to 15–30°C. Keep the supplied packaging and expiry, and ask a pharmacist about heat exposure, damage or uncertain product identity. Allowed excursions are not ideal ongoing storage. A historical online package or another brand’s condition does not supersede the leaflet supplied with the actual medicine. [1]
How do similarly named combinations differ?
Jinteli’s checked label contains norethindrone acetate 1 mg/EE 5 mcg, whereas the selected femhrt label lists 0.5 mg/2.5 mcg. Matching component names is not an instruction to substitute multiple tablets or assume current availability of an old brand strength. Activella uses estradiol rather than EE; those estrogen amounts cannot be equated by unit conversion. [1], [2] [6]
Compare indication, oral/transdermal route, complete progestin exposure, bleeding, risks and convenience. Separate components offer more independent adjustment but require a reliable protection calendar. If contraception is needed, address its distinct eligibility and missed-dose consequences rather than relying on the menopause combination. [1], [3]
What do public femhrt accounts describe?
The freshly retrieved page includes perceived relief of sweats/hot flashes and sleep disruption, partial or variable benefit, acne/tolerability concerns and recurrence after stopping. Some accounts name older strengths or disease concerns. They cannot certify the current listed product, establish cancer causation or quantify adverse-event rates. [5]
No submitted dose, rating, identity, direct quote or response timeline is reproduced. The useful questions are concrete: which symptom improved, what became difficult, what happened on stopping and whether the actual replacement product was checked. Public preference is not proof of a potency difference between brands. [1], [2], [5]
Common questions about femhrt
Is 2.5 mcg the same as 2.5 mg?
No. A milligram is 1,000 micrograms. The selected estrogen amount is 2.5 mcg; units must remain attached to the component. [1] The progestin component has a different amount and unit, so both must stay named on the prescription. This numerical distinction is not a potency conversion between different estrogens. If the package or strength differs from the selected reference, have the pharmacist identify the actual product before interpreting its instructions. See the component table. [1]
Does this combination provide contraception?
No approved contraceptive indication or calendar is verified in this menopause label. Discuss a separate plan if pregnancy is possible. [1], [3] The norethindrone-acetate component has a uterine role in the studied menopausal regimen, not an automatically established pregnancy-prevention role. Bring the current method and pregnancy preferences to the appointment. A changed bleeding pattern cannot prove that ovarian activity ended or that a new contraceptive is unnecessary. See treatment goals. [1], [3]
Can a historical 1 mg/5 mcg femhrt review prove current supply?
No. The selected FDA reference lists 0.5 mg/2.5 mcg; historical trials and reviews do not certify present stock. Jinteli is separately named. [1], [2], [5] A historical account may describe a prior formulation or a separate product without establishing what a pharmacy can supply now. Match brand, ingredients, strength and full instructions before comparing access or effects. The retained source is a dated label reference, not a present-stock guarantee. See the product comparison. [1], [2], [5]
Is the newest manufacturer revision fully confirmed here?
No. Full May 2023 FDA text was verified; original current brand labeling and local marketing remain pending before release. [1] That access limitation is disclosed so an older complete reference is not mistaken for a fresh original-brand label. Before relying on it for a new prescription or switch, ask the pharmacist for current supplied-product instructions and the prescriber to confirm the complete plan. See the verified protocol scope. [1]
What should I do if a tablet is missed?
Check the instructions supplied with the actual medicine and ask the pharmacist if the rule is unclear. A specific catch-up interval was not verified in the selected full femhrt reference, so this guide does not borrow one from Jinteli, Activella or a contraceptive pack. Keep the omission and next planned dose visible for the conversation; do not invent a double-dose rule. See daily use for this limitation. [1], [2]
Glossary
Definitions for interpreting the product, calendar and limitations.
- Estrogen
- A hormone class that includes estradiol, estrone and estriol.
- MHT / HRT
- Menopausal hormone therapy; hormone replacement therapy is a broader term.
- Vasomotor symptoms
- Menopausal hot flashes and night sweats.
- GSM
- Genitourinary syndrome of menopause: symptoms and tissue changes involving genital and urinary areas.
- Systemic treatment
- Medicine delivered through the circulation to act throughout the body.
- Local treatment
- Treatment directed mainly at the tissue where it is applied; some absorption can still occur.
- First-pass metabolism
- Initial liver processing after a swallowed medicine is absorbed from the gut.
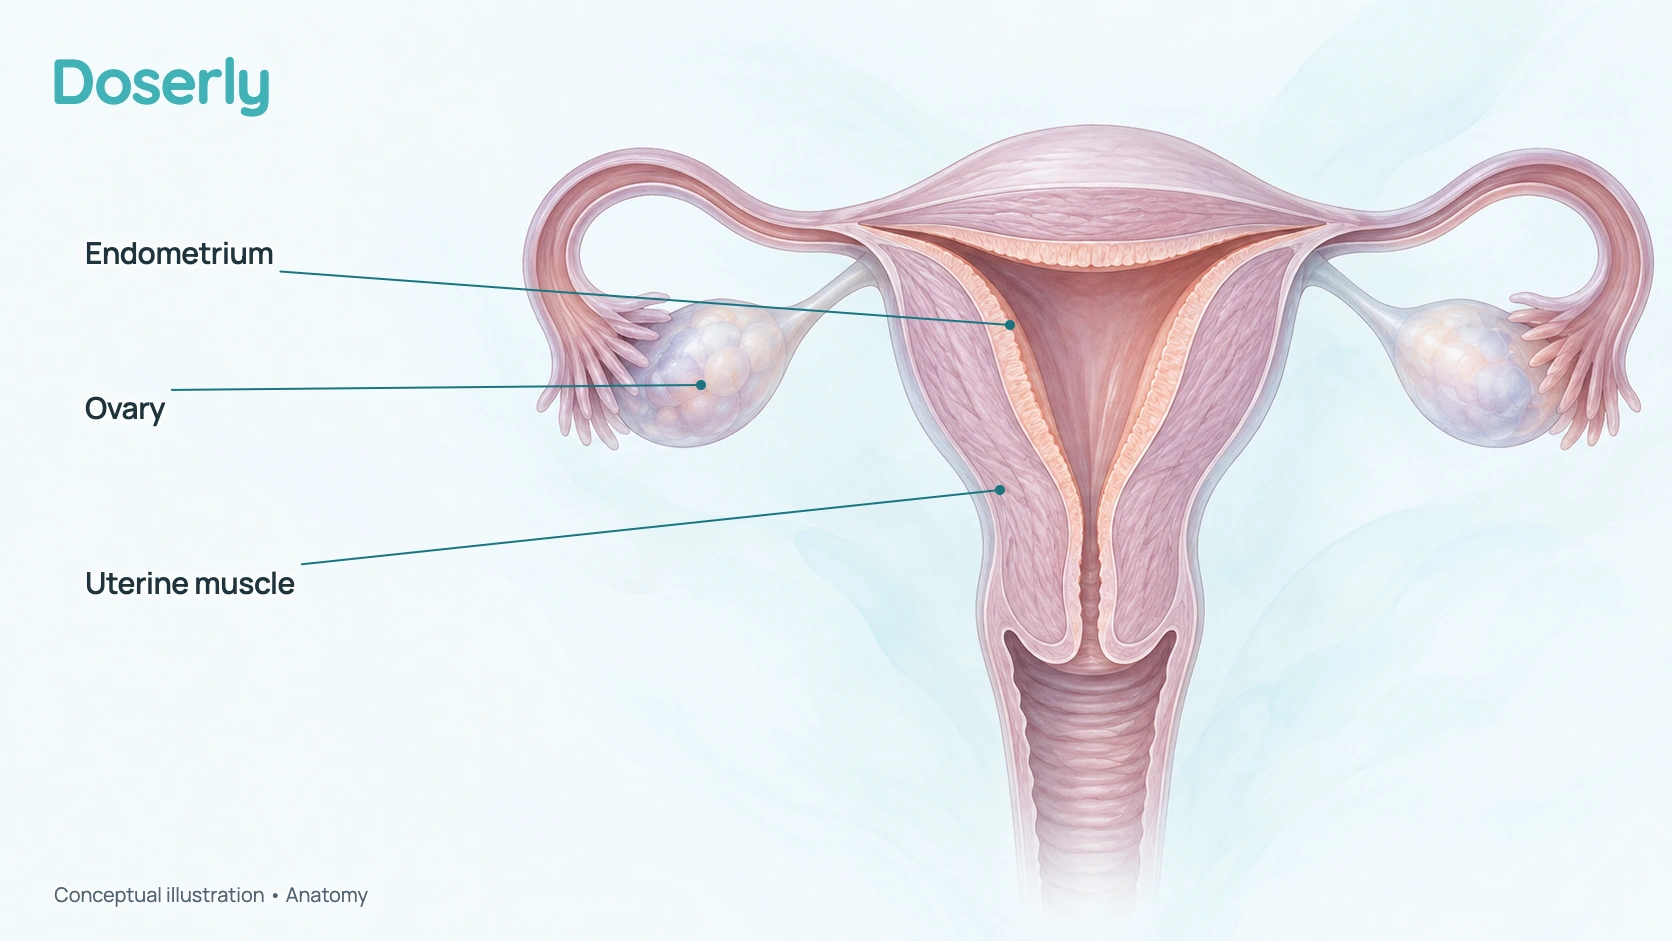
- Endometrium
- The lining inside the uterus.
- Endometrial hyperplasia
- Excess growth of uterine lining; some forms can precede cancer.
- Progestogen
- A medicine class including progesterone and synthetic progestins, used for uterine protection in systemic HRT.
- Micronized progesterone
- Progesterone processed into small particles to support absorption; route and schedule remain important.
- Continuous combined
- Estrogen and progestogen taken without planned monthly breaks.
- Sequential
- Progestogen taken during a defined part of an estrogen-treatment cycle.
- Withdrawal bleed
- A planned bleed associated with stopping the progestogen part of a sequential regimen.
- Hysterectomy
- Surgery to remove the uterus; it does not always remove the ovaries.
- VTE
- Venous thromboembolism: a clot in a vein, including leg clots and pulmonary embolism.
- Pulmonary embolism
- A clot blocking an artery in the lungs; a medical emergency.
- Absolute risk
- How often an event occurs in a specified population over a specified time.
- Relative risk
- An event rate in one group compared with another; it needs baseline risk to show practical size.
- Contraindication
- A circumstance in which a medicine should not be used according to its label.
- Compounded product
- A pharmacy-prepared medicine; approval of an ingredient does not approve the finished preparation.
- EE
- Ethinyl estradiol, a synthetic estrogen.
- Norethindrone acetate
- Synthetic progestin paired with EE in femhrt.
- Microgram / mcg
- A thousandth of a milligram, not a cross-hormone potency comparison.
- Fixed combination
- Two active components in one dosage form, changed together.
How was this guide researched?
Named full labels define calendars, indications and risks. Marketing records do not prove stock; guidelines inform care without changing authorization. Public accounts remain separate from clinical evidence. Sources identify document revision and access.
How this page was made
This Doserly editorial guide was prepared with AI assistance using public sources checked October 2, 2026. No independent clinician reviewer is claimed. Doserly develops a commercial tracking app. Original figures explain concepts and do not represent trial results. The directory identifies source revisions and access limitations. January 2027 is a review target; new evidence can require an earlier check.
Sources and updates
Numbered public sources checked October 2, 2026.
Showing 6 sources
- 01
femhrt — FDA prescribing information ↗
Full label
Complete selected FDA reference; later revision/local supply not certified.
- 02
JINTELI — prescribing information ↗
Full label
Separate 1 mg/5 mcg MHT tablet, not authority for current femhrt strengths.
- 03
Menopause: identification and management — Recommendations ↗
Full guideline
Follow-up, bleeding, routes and stopping.
- 04
FDA Approves Labeling Changes to Menopausal Hormone Therapy Products ↗
Full statement
Named first six do not prove a new femhrt or contraceptive label.
- 05
femhrt User Reviews ↗
Public patient reviews
Full-combination accounts and older differing strengths; no current inventory inference.
- 06
No matching sources
Try a different term or show the full list.