
In this guide
What is vaginal prasterone?
Prasterone is dehydroepiandrosterone, or DHEA, a steroid precursor that the body can convert into estrogens and androgens. Intrarosa is a regulated vaginal preparation used after menopause for specified local vulvar/vaginal symptoms. Its route, amount and evidence differ from an oral DHEA supplement or a custom hormone mixture. It is not a systemic hot-flash or anti-aging replacement protocol. [1], [2], [3]
US Intrarosa is indicated for moderate-to-severe dyspareunia, painful intercourse, due to menopausal vulvar/vaginal atrophy. The UK label uses the broader wording moderate-to-severe symptoms of vulvar/vaginal atrophy. The same daily amount does not erase that indication difference or each country’s safety instructions. [1], [2]
The current FDA application record links the February 2018 label, and the current US manufacturer resource page still directs readers to the corresponding AMAG/DailyMed text. This is a verified current source pathway, not a claim that old NDC entries prove local stock or that a 2025 website footer is a new clinical-label revision. The UK SmPC revision is distinct from its repository posting date. The full UK patient leaflet is revised July 2026 and was separately cross-checked. [1], [2], [3], [7], [8]
What is the exact labeled nightly schedule?
| Product / country | Population / indication | Route | Amount | Schedule | Context | Source |
|---|---|---|---|---|---|---|
| Intrarosa · US | Postmenopausal moderate/severe dyspareunia due to VVA | Vaginal insert | Prasterone 6.5 mg per insert | One daily at bedtime using supplied applicator | Local indication; breast-history warning and bleeding evaluation | FDA label [1] |
| Intrarosa · UK | Moderate/severe postmenopausal vulvar/vaginal atrophy symptoms | Vaginal pessary | Prasterone 6.5 mg per pessary | One daily at bedtime; finger or identified-pack applicator | Product-specific contraindications and combination restrictions | SmPC [2] |
The amount is per vaginal insert, not an oral tablet or absorbed systemic hormone dose. The named labels use daily treatment, without borrowing a vaginal-estrogen initial course and twice-weekly maintenance pattern. Adjustment means discussing benefit, tolerability and whether this product is appropriate, not constructing a different calendar from another medicine. [1], [2]
Use the actual pack’s insertion method. UK instructions allow a finger or applicator in the identified pack and say insert as far as comfortable without force; US labeling names the supplied applicator. This is local administration, not a skin application or a capsule to swallow. [1], [2]
Doserly
ORIGINAL EXPLANATORY DIAGRAM
Keep prasterone route and purpose together
Named US/UK Intrarosa labels; no oral supplement dose is inferred.
Vaginal product
Prasterone 6.5 mg per insert/pessary, one nightly.
Local goal
US: menopausal moderate/severe dyspareunia. UK: moderate/severe VVA symptoms.
Oral DHEA
Different route, exposure and evidence. Not an equivalent replacement protocol.
Evidence note: complete named US and UK labels. No oral DHEA dose, compounded-equivalence rule or symptom-based self-escalation supplied.
Verification scope
Named full labels and stated jurisdiction, checked October 2, 2026. Revisions are distinct from access dates. Local stock and reimbursement were not verified.
Which symptoms and alternatives fit the evidence?
The direct US goal is less pain with intercourse due to menopausal tissue changes. Local comfort and dryness can be discussed in the broader UK VVA population, but urinary complaints, bleeding, infection and pelvic pain may have other causes. A prescription should identify the symptom and whether examination or another treatment is needed. [1], [2], [4]
NICE considers vaginal prasterone when vaginal estrogen or nonhormonal moisturizers/lubricants have been ineffective or are not tolerated. This is a treatment sequence, not proof that it is universally superior. Moisturizers, lubricants, vaginal estrogen and other options have different practical advantages, contraindications and evidence; choose for the actual problem rather than the DHEA name. [4]
Reduced pain can make intimacy more comfortable without establishing an approved treatment for every cause of low libido, infertility or systemic fatigue. Oral supplement benefit cannot be inferred from vaginal trials. [1], [2]
What do local conversion and forgotten-dose rules mean?
Prasterone is converted within tissues into estrogenic and androgenic metabolites. Label pharmacokinetic measurements show some systemic exposure; predominantly local action does not mean no hormone conversion or zero absorption. It also does not make an insert a replacement for systemic estrogen or testosterone treatment. [1], [2]
The UK SmPC says take a forgotten dose when remembered unless the next is due in less than eight hours; then skip it, and do not use two to make up. The selected US leaflet does not provide that precise threshold. Ask the pharmacist using the actual supplied US product rather than importing the UK cutoff as a universal rule. [1], [2]
UK labeling advises avoiding contact with latex condoms, diaphragms or cervical caps because the preparation may damage rubber. This compatibility warning does not imply contraceptive efficacy. [2]
What do the trials establish about local benefit and protection?
The labeled efficacy studies assessed postmenopausal participants with moderate-to-severe dyspareunia and vaginal tissue/pH criteria over 12 weeks. Improvements in symptom severity and tissue measures support the named local treatment. A change in a smear or pH is not the same outcome as comfort, and neither proves a lifetime benefit or superiority over every local estrogen option. [1], [2]
NAMS’s accessed 2020 abstract says progestogen is not indicated solely with vaginal DHEA, while longer-than-one-year endometrial safety evidence is limited. The UK label describes no hyperplasia cases in its 52-week studies but acknowledges that long-term local prasterone safety beyond one year was not studied. No added progestogen for this local indication does not remove protection required for any separate systemic estrogen regimen. [2], [5]
The breast-cancer-history population has important evidence limits; the US label says Intrarosa was not studied there, while UK contraindications are broader. Do not claim zero breast risk or transfer WHI systemic CEE rates to this local preparation. [1], [2], [5]
Doserly
ORIGINAL EXPLANATORY DIAGRAM
Local does not mean every risk question is settled
Conceptual evidence map, not a tissue concentration or outcome plot.
Conversion
Prasterone forms estrogenic and androgenic metabolites; some systemic exposure is measured.
Studied benefit
Local symptom/tissue measures over 12 weeks support the named treatment.
Protection limits
No progestogen solely for vaginal DHEA under NAMS; longer-term data limited and separate systemic protection still matters.
Sources checked October 2, 2026: Source 1, Source 2, Source 5.
Which country-specific restrictions need attention?
US formal contraindication is undiagnosed abnormal genital bleeding. The label also warns about current/past breast cancer because estrogen is a metabolite and the population was not studied. The UK contraindication list includes breast or estrogen-dependent cancer, untreated hyperplasia, specified liver disease, venous clots, thrombophilia and active/recent arterial disease. Preserve that difference instead of calling the US brief list a universal safety exemption. [1], [2]
The UK SmPC does not recommend concomitant systemic HRT, androgen treatment or vaginal estrogen because use was not investigated. That matters when a person already uses a patch or vaginal cream. Guideline discussion of local options does not override the product-specific combination restriction. Review the complete plan with the prescriber. [2], [4]
Discharge, local discomfort and abnormal cervical-screening findings are described in clinical safety reports. An abnormal Pap result is not automatically cancer, and a case reported during use is not proof of causation. New bleeding, a breast change, severe pain or concerning symptoms needs evaluation rather than treating every change as harmless local leakage. [1], [2]
What should follow-up and discharge assessment include?
Track pain with intercourse or other agreed local symptoms, insertion comfort, daily adherence, discharge, bleeding and any added hormonal product. Review whether persistent discomfort reflects atrophy, an infection, skin condition or another pelvic problem. UK labeling says discharge can reflect melting hard fat and increased secretions, and does not by itself require stopping; bothersome or unusual changes still deserve assessment. [1], [2], [4]
NICE recommends review at three months then annually, earlier for problems. The UK product specifically asks benefit/risk reassessment at least every six months. Keep both instructions recognizable and follow the actual clinical plan; no universal blood DHEA target is supplied. UK guidance requires investigation of bleeding or spotting at any time during treatment, not waiting for a systemic-HRT bleeding threshold. [2], [4]
What happens if treatment stops or another product is chosen?
Discuss recurrence of local symptoms, the reason for stopping and a suitable alternative. The labeled daily course does not require an invented systemic hormone taper or a maintenance calendar borrowed from estrogen. Severe or suspicious symptoms need assessment, while ordinary tolerability or access concerns can be addressed with a planned change. [1], [2], [4]
If another local or systemic hormone is considered, review the UK combination restriction rather than overlap by default. Oral DHEA is not a verified milligram-equivalent replacement for the insert. Continuing a separate systemic estrogen may still require its own uterine-protection plan; discontinuing a local insert does not determine that decision. [2], [4], [5]
How do the named storage rules differ?
US label says 5–30°C and permits room-temperature or refrigerator storage. UK says below 30°C and do not freeze. Retain the actual pack, expiry and applicator instructions; a melting fat-based insert needs pharmacist advice if overheated or damaged. Do not turn the US refrigerator permission into a universal requirement or substitute a compounded insert’s beyond-use conditions. [1], [2]
How do vaginal estrogen and oral DHEA differ?
Vaginal estrogen supplies estrogen directly; prasterone provides a precursor converted within tissues. Different mechanisms do not establish a universal superiority or zero-hormone option. NICE’s sequence and the actual contraindications, administration comfort, discharge and access can guide the choice. [1], [2], [4]
An oral supplement changes route, systemic exposure, quality framework and evidence. Its amount cannot be copied from the vaginal insert, and a label calling DHEA natural does not make it the same regulated treatment. This guide provides no oral anti-aging, fatigue or libido protocol. A compounded vaginal mixture likewise requires its own evaluation, rather than borrowing Intrarosa’s approval. [1], [2], [3]
What do the freshly checked public reviews describe?
The verified Intrarosa review page includes perceived pain/local-comfort improvement, partial or absent benefit, discharge and staining, irritation and decisions to continue or stop. Some entries describe urinary or other problems outside the precise US indication. Reports identify practical questions but do not expand approval or establish drug-caused hair, mood or disease outcomes. [6]
No identity, rating, quote, submitted amount or response timeline is reproduced. A striking improvement or difficult experience is not a representative rate, and two people’s timing does not establish how long everyone must persist. Ask what symptom improved, whether discharge was expected or concerning and whether a different local plan fits better. [1], [2], [6]
Common questions about prasterone
Is Intrarosa the same treatment as oral DHEA?
No. The verified amount and trial evidence concern a vaginal insert/pessary, not a systemic oral supplement. [1], [2], [3] The named local product has its own indication, administration instructions and exclusion criteria. An oral supplement cannot inherit those results or be substituted milligram for milligram. If local treatment is unsuitable or symptoms persist, discuss the symptom, examination needs and other options rather than change route yourself. See the treatment comparison. [1], [2], [3]
Does local use mean no estrogen is formed?
No. Estrogens and androgens are metabolites; some systemic exposure is measured. [1], [2] Local administration describes delivery, not complete absence of metabolism or systemic effects. This also explains why product warnings and a relevant cancer history remain part of the assessment. A mechanism does not establish suitability for every person or combination. See metabolism and evidence alongside the actual country label. [1], [2] Keep the actual product identified.
Is additional progesterone required solely for vaginal DHEA?
NAMS’s abstract does not indicate it solely for vaginal DHEA, while longer-term data remain limited and separate systemic estrogen protection remains its own issue. [2], [5] That statement does not remove the need to assess unexpected bleeding or establish safety indefinitely. It concerns the local vaginal treatment, not a new complete regimen that also includes systemic estrogen. Ask which protection and review requirements apply to each medicine you use. See uterine protection and evidence limits. [2], [5]
Can UK Intrarosa automatically be added to a patch?
No. Its SmPC does not recommend concomitant systemic HRT or vaginal estrogen because the combination was not investigated. Review with the prescriber. [2] This product restriction and guidance discussing local options during systemic treatment should remain distinguishable. The precise proposed combination, country instructions and clinical circumstances need review rather than an automatic permission based on the word local. Bring all hormonal products to the appointment. See combination restrictions before adding or replacing treatment. [2], [6]
Should unexpected bleeding wait for a routine review?
No. The labels require assessment, and UK wording calls for investigation at any time. [1], [2] Routine follow-up and investigation of a new symptom serve different purposes. Record timing, amount and associated symptoms and contact the clinician for assessment rather than using a general systemic-HRT bleeding interval as a waiting rule. The vaginal product’s instructions retain their own scope. See monitoring and bleeding. [1], [2]
Glossary
Definitions for interpreting the product, calendar and limitations.
- Estrogen
- A hormone class that includes estradiol, estrone and estriol.
- MHT / HRT
- Menopausal hormone therapy; hormone replacement therapy is a broader term.
- Vasomotor symptoms
- Menopausal hot flashes and night sweats.
- GSM
- Genitourinary syndrome of menopause: symptoms and tissue changes involving genital and urinary areas.
- Systemic treatment
- Medicine delivered through the circulation to act throughout the body.
- Local treatment
- Treatment directed mainly at the tissue where it is applied; some absorption can still occur.
- First-pass metabolism
- Initial liver processing after a swallowed medicine is absorbed from the gut.
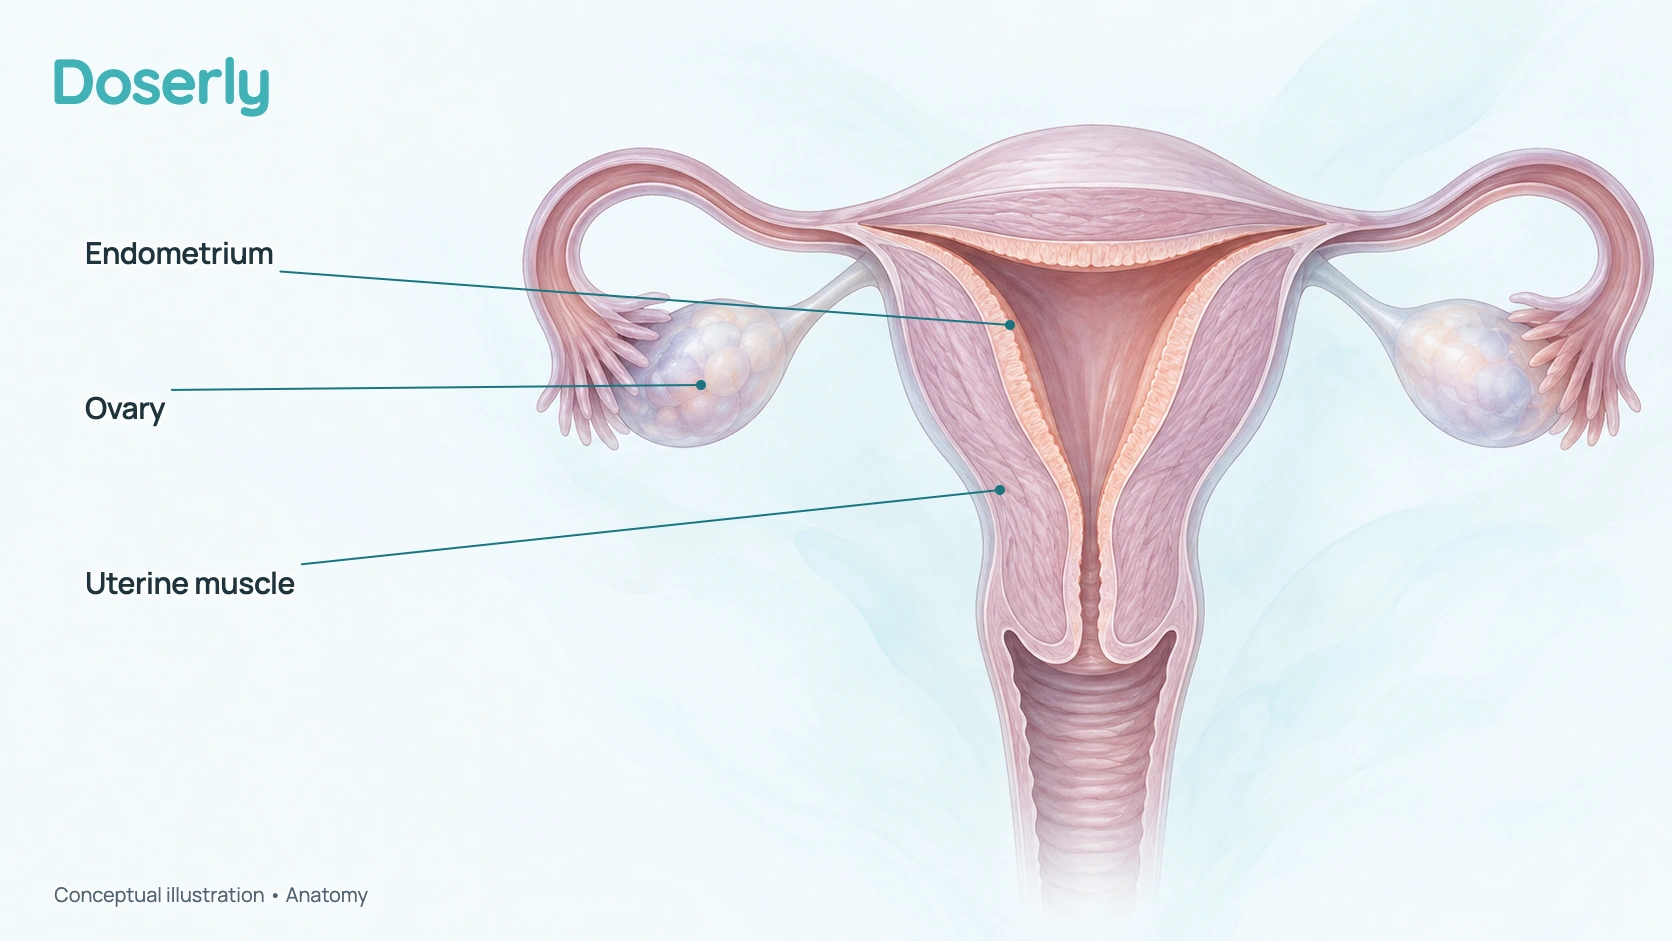
- Endometrium
- The lining inside the uterus.
- Endometrial hyperplasia
- Excess growth of uterine lining; some forms can precede cancer.
- Progestogen
- A medicine class including progesterone and synthetic progestins, used for uterine protection in systemic HRT.
- Micronized progesterone
- Progesterone processed into small particles to support absorption; route and schedule remain important.
- Continuous combined
- Estrogen and progestogen taken without planned monthly breaks.
- Sequential
- Progestogen taken during a defined part of an estrogen-treatment cycle.
- Withdrawal bleed
- A planned bleed associated with stopping the progestogen part of a sequential regimen.
- Hysterectomy
- Surgery to remove the uterus; it does not always remove the ovaries.
- VTE
- Venous thromboembolism: a clot in a vein, including leg clots and pulmonary embolism.
- Pulmonary embolism
- A clot blocking an artery in the lungs; a medical emergency.
- Absolute risk
- How often an event occurs in a specified population over a specified time.
- Relative risk
- An event rate in one group compared with another; it needs baseline risk to show practical size.
- Contraindication
- A circumstance in which a medicine should not be used according to its label.
- Compounded product
- A pharmacy-prepared medicine; approval of an ingredient does not approve the finished preparation.
- Pharmacokinetics / PK
- How exposure changes with absorption, distribution, metabolism and elimination.
- DHEA / prasterone
- Steroid precursor that can be converted into estrogenic and androgenic metabolites.
- Intracrine conversion
- Transformation and action within tissues; it does not mean zero systemic exposure.
- Dyspareunia
- Pain with intercourse; causes and treatment must be assessed.
- Vulvar and vaginal atrophy / VVA
- Menopause-related tissue changes, part of the broader GSM syndrome.
- Pessary / vaginal insert
- Local dosage form; terminology here does not mean a prolapse-support device.
- Pap test / cervical screening
- Screening for cervical cellular changes; an abnormal result is not automatically cancer.
How was this guide researched?
Named full labels define calendars, indications and risks. Marketing records do not prove stock; guidelines inform care without changing authorization. Public accounts remain separate from clinical evidence. Sources identify document revision and access.
How this page was made
This Doserly editorial guide was prepared with AI assistance using public sources checked October 2, 2026. No independent clinician reviewer is claimed. Doserly develops a commercial tracking app. Original figures explain concepts and do not represent trial results. The directory identifies source revisions and access limitations. January 2027 is a review target; new evidence can require an earlier check.
Sources and updates
Numbered public sources checked October 2, 2026.
Showing 8 sources
- 01
INTRAROSA — FDA prescribing information ↗
Full label
Complete US insert indication, nightly schedule, precautions and trial findings.
- 02
Intrarosa 6.5 mg pessary — SmPC ↗
Full SmPC
UK broader VVA indication, eight-hour missed threshold, contraindications and compatibility.
- 03
Intrarosa — Drugs@FDA application overview ↗
Full application record
Approval history and vaginal 6.5 mg prescription product; not local stock.
- 04
Menopause: identification and management — Recommendations ↗
Full guideline
Consider vaginal prasterone when vaginal estrogen/nonhormonal options ineffective or intolerable.
- 05
The 2020 genitourinary syndrome of menopause position statement of The North American Menopause Society ↗
Abstract accessed
Vaginal DHEA, protection principle and longer-term/cancer-history evidence limits.
- 06
Intrarosa User Reviews ↗
Public patient reviews
Mixed local comfort/pain, discharge, irritation and partial benefit accounts.
- 07
INTRAROSA — healthcare professional resources ↗
Full manufacturer page
Current manufacturer links AMAG/DailyMed February 2018 text; no newer clinical revision inferred.
- 08
Intrarosa 6.5 mg pessary — patient leaflet ↗
Full patient leaflet
Fresh July 2026 leaflet cross-check of dose, eight-hour threshold, combinations and storage.
No matching sources
Try a different term or show the full list.