
In this guide
What is magnesium?
Magnesium is an essential mineral. The body uses it to help enzymes release energy from food, build proteins and DNA, move calcium and potassium across cell membranes, contract and relax muscles, and carry nerve signals. About half to 60% of the body's magnesium is stored in bone; most of the rest is inside cells. Less than 1% circulates in serum, the liquid part of blood. [1]
That distribution explains two common sources of confusion. First, a normal serum result does not prove that every tissue store is full. Second, a supplement label must be read in elemental magnesium, the amount of magnesium itself, rather than the total weight of magnesium citrate, glycinate or oxide.
Magnesium is both a nutrient and an ingredient in medicines. Some salts are sold as dietary supplements. Magnesium hydroxide and other salts are also used in antacids or laxatives, where the intended effect and dose are different. A study using one salt for one purpose does not validate every product called magnesium.
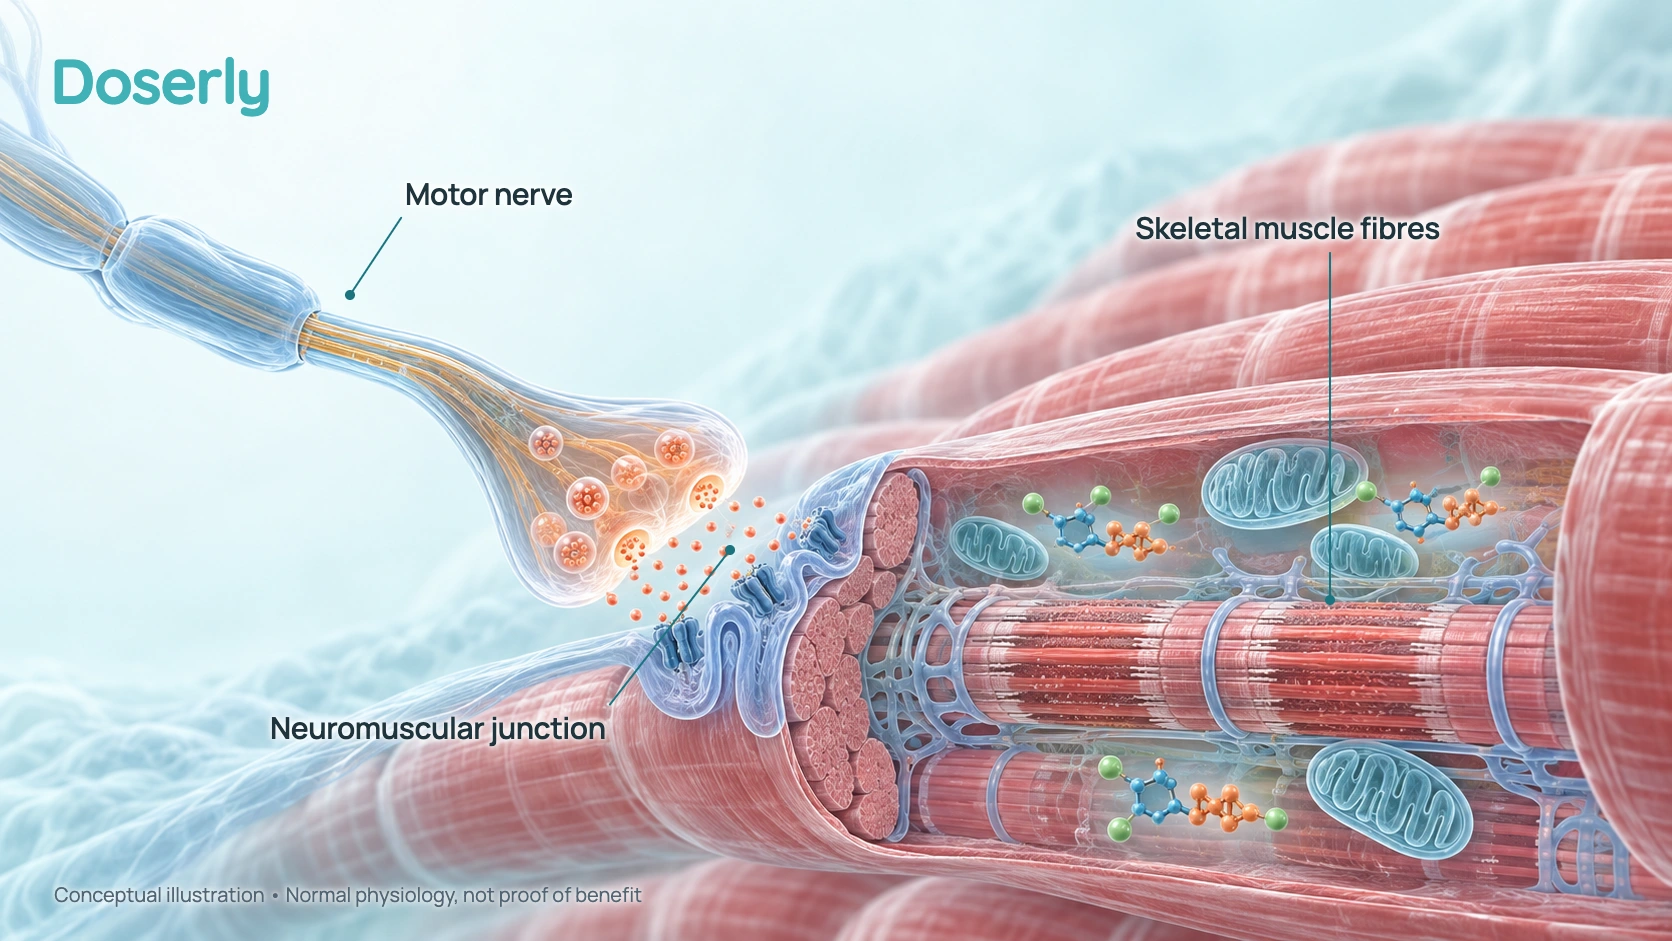
The conceptual illustration below shows a motor nerve meeting skeletal muscle. It presents normal anatomy and does not show magnesium molecules, deficiency, a supplement response or a treatment effect.
Typical Magnesium Protocols
| Purpose or source | Form and amount each time | Frequency | Total per day | Duration |
|---|---|---|---|---|
| U.S. RDA, adult men | Magnesium from all sources | Daily | 400 mg age 19–30; 420 mg age 31+ | Ongoing reference intake |
| U.S. RDA, nonpregnant adult women | Magnesium from all sources | Daily | 310 mg age 19–30; 320 mg age 31+ | Ongoing reference intake |
| Migraine prevention trial | 600 mg magnesium (24 mmol) as trimagnesium dicitrate | Every morning | 600 mg | 12 weeks after a 4-week baseline |
| Poor-sleep trial in adults 18–65 | Two bisglycinate capsules, each providing 125 mg elemental magnesium | Once daily | 250 mg elemental | 28 days |
| Primary-insomnia trial in adults 60–75 | 250 mg elemental magnesium as 414 mg magnesium oxide | Twice daily | 500 mg elemental | 8 weeks |
| Nocturnal-leg-cramp trial | 520 mg elemental magnesium as an 865 mg oxide/oxide-monohydrate complex | At bedtime | 520 mg elemental | 4 weeks |
The first two rows are nutrient reference values, not treatment schedules. The remaining rows preserve the exact form, population and duration from one randomized trial each.
The RDA rows describe total intake that meets the needs of nearly all healthy people. They are not instructions to add that amount as a supplement. Food magnesium already counts. The adult U.S. upper limit is 350 mg/day from supplements and medicines, a limit based mainly on diarrhea; it excludes magnesium naturally present in food and drinks. [1]
The trial rows are alternatives from different questions, not steps in a program. The migraine trial's 600 mg schedule reduced attack frequency more than placebo, but diarrhea affected 18.6% and gastric irritation 4.7%. A 2025 bisglycinate trial found a small improvement in insomnia severity, while the older oxide insomnia trial was small and total sleep time did not differ significantly. The leg-cramp trial was negative. [3], [9], [4], [5]
Where these amounts come from
The RDA and UL rows come from the NIH Office of Dietary Supplements, which reproduces the U.S. National Academies reference values. The migraine row is the complete Peikert 1996 schedule, the sleep row the complete Abbasi 2012 schedule, and the cramp row the complete Roguin Maor 2017 schedule. [1], [3], [4], [5]
We did not merge amounts from different salts, convert a daily total into invented per-dose amounts, or call the highest study dose a safe maximum. The sleep and cramp schedules exceed the U.S. supplemental UL and describe monitored trials, not routine self-care.
Does magnesium need to be cycled?
No nutrient authority describes a general magnesium cycle. Food intake is continuous. A time-limited study schedule ends because the study ended, not because the body needs a break. If a supplement is being used to correct a documented deficiency or address a specific clinical problem, the reason to continue depends on the cause, response, side effects and follow-up rather than an arbitrary on/off calendar.
What happens when magnesium is stopped?
Magnesium does not produce a known withdrawal syndrome. A laxative effect stops when the product is stopped. If low intake, malabsorption, medication use or another cause of deficiency remains, magnesium status can fall again. Trial benefits should not be assumed to persist beyond follow-up; the four trials above did not establish a durable post-treatment effect. [1], [3], [4], [5], [9]
Which foods provide magnesium?
Legumes, nuts, seeds, whole grains and green leafy vegetables are useful sources. Milk, yogurt, fortified cereals and some other fortified foods contribute too. Food brings magnesium with protein, fiber and other nutrients, and its magnesium does not count toward the supplemental UL in healthy people. [1]
Food labels and nutrient databases report milligrams of elemental magnesium. A day with beans or lentils, whole grains, leafy greens and nuts can contribute substantially before a supplement is added. The practical comparison is total intake across food, fortified food, supplements, antacids and laxatives, because several products may contain magnesium under different names.
Does the form or product matter?
Yes, but the most useful distinction is specific rather than a league table.
- Citrate, chloride, lactate and aspartate: these more soluble salts were more completely absorbed than oxide or sulfate in small studies summarized by ODS. Citrate also has an osmotic effect in the bowel at sufficient doses. [1]
- Oxide: contains a large proportion of elemental magnesium by weight, so a small tablet can list a large elemental amount. It is less soluble, and a larger fraction can remain in the gut and loosen stool. The insomnia and leg-cramp trials in this guide used oxide, with mixed results. [4], [5]
- Glycinate or bisglycinate: widely sold and often described as gentle, but the current ODS fact sheet does not establish that it is universally best absorbed or best tolerated. Claims should be tied to the exact product and comparison.
- Threonate: marketed for brain effects. Animal transport findings and small product-specific human studies do not establish that ordinary magnesium outcomes transfer to this salt.
The Supplement Facts panel should state elemental magnesium per serving. Front-label wording such as “2,000 mg magnesium glycinate” can refer to the total compound weight and still provide only a fraction of that amount as magnesium.
Read the elemental amount
The compound name explains the form. The elemental line explains how much magnesium it provides.
How should magnesium be stored, and how long does it last?
Use the product's label for temperature, moisture protection and expiry. Dry tablets and capsules are commonly kept tightly closed at room temperature, but this is packaging guidance rather than a class-wide stability study. Discard a product with damaged seals, water exposure, an unexpected odor or appearance, or an expired label. Prepared liquids and powders follow their own instructions.
What is magnesium commonly used for?
People most often use magnesium to fill an intake gap, treat a diagnosed deficiency, support migraine prevention, loosen stool, or try to improve sleep or cramps. Those purposes are not interchangeable. Nutritional replacement, a laxative medicine and a migraine trial use different forms, amounts and endpoints. The human evidence below keeps each question separate. [1], [3], [4], [5]
What does human research show?
Migraine prevention
In the 1996 multicenter trial, 81 adults with migraine were randomized after a four-week baseline. They took 600 mg magnesium as trimagnesium dicitrate every morning or placebo for 12 weeks. During weeks 9–12, attack frequency fell 41.6% from baseline with magnesium and 15.8% with placebo. Migraine days and use of symptom medicine also fell more with magnesium, while attack duration and intensity did not differ significantly. Diarrhea and gastric irritation were the main reported adverse effects. [3]
The result supports a possible preventive effect for that salt and schedule. It does not show that magnesium stops an acute attack, that every form works equally, or that 600 mg is appropriate without clinical oversight. ODS describes the migraine evidence as several small studies and advises clinical supervision for this use. [1]
Sleep
The newer 2025 trial enrolled 155 healthy adults aged 18–65 who reported poor sleep. The active product provided 250 mg elemental magnesium and 1,523 mg glycine as two bisglycinate capsules daily for 28 days. The Insomnia Severity Index fell 3.9 points with bisglycinate and 2.3 with placebo; the between-group effect was small (Cohen's d 0.2). Other psychological outcomes did not significantly differ, and the study used self-reported rather than objective sleep measures. [9]
The 2012 trial enrolled 46 adults aged 60–75 with primary insomnia, dietary magnesium below 75% of the RDA, and no renal disease. They received 250 mg elemental magnesium as oxide twice daily or placebo for eight weeks. Sleep efficiency, reported sleep time, sleep-onset latency and Insomnia Severity Index scores improved more with magnesium, but total sleep time did not differ significantly. [4]
A later systematic review found only three small trials with 151 older adults, varied forms and schedules, and low to very low certainty. The pooled estimate suggested shorter sleep-onset latency, while the increase in total sleep time was not statistically significant. The fair conclusion is that sleep evidence is limited, not that magnesium is a proven general sleep treatment. [6], [10]
Nocturnal leg cramps
The clearest trial in ordinary community-dwelling adults was negative. Ninety-four people with at least four cramps during a two-week screening period received 520 mg elemental magnesium as an oxide complex at bedtime or placebo for four weeks. Cramp frequency improved in both groups, with no significant difference between them. Severity, duration, sleep and quality of life also did not differ. [5]
This is a useful warning against reading a biological role backward. Magnesium deficiency can cause muscle cramps, but that does not mean extra magnesium treats common nighttime cramps in people who are not deficient.
Blood pressure and cardiometabolic claims
FDA reviewed the evidence linking adequate magnesium intake with lower high-blood-pressure risk and allowed only a qualified claim. Its permitted language says the evidence is “inconsistent and inconclusive.” ODS likewise describes only small average blood-pressure changes and notes that food-pattern studies cannot isolate magnesium from the rest of the diet. [2], [1]
Observational links with type 2 diabetes and bone density are plausible and useful for research, but they do not prove that a supplement prevents either condition. People with diagnosed disease need evidence and treatment specific to that disease.
One mineral, four trial questions
Salt, population, amount and duration stay attached to each result.
These schedules describe trials. They are not a dose ladder or a comparison of equivalent products.
How does magnesium work?
Magnesium binds to and stabilizes molecules that carry cellular energy, including adenosine triphosphate (ATP). Enzymes use it during protein and DNA synthesis. In nerves and muscles, magnesium helps control ion channels and the movement of calcium and potassium, which shapes electrical signaling and contraction. In bone, it contributes to structure and mineral metabolism. [1]
These normal roles explain why severe deficiency can cause weakness, tremor, cramps, seizures or abnormal heart rhythms. They do not show that increasing intake above need enhances each process. A mechanism is a reason to test a claim, not proof that a supplement changes a health outcome.
What are the risks and interactions?
In the United States, magnesium products sold as dietary supplements are not approved by FDA for safety or effectiveness before marketing; the company is initially responsible for compliance, and FDA generally acts through postmarket oversight. In Canada, natural health products require a product licence before sale and carry an eight-digit NPN when authorized. These frameworks regulate products and labels; neither proves that every magnesium claim is effective. [7], [8]
The common dose-limiting effect is diarrhea, sometimes with nausea or abdominal cramping. Unabsorbed magnesium salts pull water into the bowel. This effect is useful when a medicine is intended as a laxative and unwanted when the goal is nutrition. [1]
Very large amounts can cause low blood pressure, lethargy, muscle weakness, difficulty breathing, abnormal rhythm and cardiac arrest. Healthy kidneys usually remove excess magnesium. Impaired kidney function reduces that protection, so high-dose supplements, laxatives and antacids deserve particular caution. [1]
Which medicines interact with magnesium?
- Tetracycline and quinolone antibiotics: magnesium can bind these drugs and reduce absorption. ODS reports label instructions that commonly place the antibiotic at least two hours before or four to six hours after magnesium, but the exact interval belongs to the specific drug label. [1]
- Oral bisphosphonates: magnesium can reduce absorption. ODS describes separating them by at least two hours; follow the medicine's own label. [1]
- Diuretics: loop and thiazide diuretics can increase urinary magnesium loss, while potassium-sparing diuretics reduce excretion. [1]
- Proton-pump inhibitors: long-term use can cause low magnesium. In some FDA cases, supplements did not correct the problem until the PPI was stopped. [1]
- High-dose zinc: very high supplemental zinc can interfere with magnesium balance. [1]
The interaction question is about the whole list: supplement, antacid, laxative, prescription medicines, kidney function and other minerals.
What should be monitored?
For ordinary food intake, routine magnesium testing is not recommended. When deficiency or toxicity is plausible, clinicians interpret serum magnesium with kidney function, symptoms, medications and related electrolytes such as potassium and calcium. Serum is convenient but represents less than 1% of total body magnesium and does not closely track tissue stores. [1]
Practical records can still help: exact product and form, elemental amount per serving, doses taken, bowel effects, the reason for use, and any relevant lab date. A symptom change after starting is an observation. It is not proof that magnesium caused the change.
What do public communities report?
Public posts commonly compare forms, bowel tolerance, sleep, cramps and migraine. Those discussions are useful for finding questions, especially the confusion between compound weight and elemental magnesium. They are poor evidence for effect sizes: products differ, baseline deficiency is usually unknown, and sleep or cramp symptoms often change on their own.
The earlier Doserly dossier reviewed public discussions, but this overhaul did not independently recrawl or quote them. No percentage or “community consensus” is carried forward. The controlled evidence above gets more weight.
How does magnesium compare with nearby options?
| Guide | What it is | Key difference |
|---|---|---|
| Calcium | Essential major mineral | Different intake targets and interactions; calcium and magnesium amounts are not interchangeable |
| Potassium | Essential electrolyte | Supplemental potassium has a distinct hyperkalemia risk, especially with kidney disease and certain medicines |
| Electrolyte powders | Multi-ingredient products | Usually designed around sodium and fluid replacement; the magnesium amount is often modest |
| Vitamin D3 | Fat-soluble vitamin involved in calcium absorption | It has separate intake targets, laboratory interpretation and toxicity risks; one nutrient cannot substitute for the other |
Common questions about magnesium
Is 400 mg of magnesium a high supplement dose?
It is close to the adult male RDA for total intake, but above the U.S. 350 mg/day UL for magnesium from supplements and medicines. The label must also say whether 400 mg is elemental magnesium or total compound weight. [1]
Is magnesium glycinate better than citrate?
There is no universal answer. Citrate is relatively soluble and may loosen stool. Glycinate is widely marketed as gentle, but superiority depends on the product, elemental dose, comparator and outcome. Choose claims supported for the exact form rather than assuming the name predicts the result.
Can magnesium help sleep?
Possibly for some older adults, but the evidence is small and low certainty. In one 46-person trial, some subjective measures improved while total sleep time did not significantly differ. [4], [6]
Does magnesium stop leg cramps?
Not reliably in the general adult population. A 94-person trial of 520 mg elemental magnesium nightly for four weeks found no advantage over placebo. Deficiency is a separate clinical question. [5]
Should magnesium be taken with food?
Food may improve stomach tolerance for some products, but timing depends on the form and purpose. The more important timing issue is separation from interacting antibiotics or bisphosphonates according to their labels. [1]
Can magnesium and calcium be taken together?
They are both nutrients and occur together in food. High-dose products can complicate tolerance or medicine timing, so compare elemental amounts and the reason for each. No fixed ratio is established for every adult.
Is a normal blood magnesium result enough?
It helps identify marked deficiency or excess, but it does not measure total-body stores well. Clinicians interpret it with kidney function, other electrolytes, medicines and symptoms. [1]
Glossary
Plain explanations of the nutrition, laboratory and research terms used in this guide.
- Adequate Intake (AI)
- A nutrient intake level used when evidence is not sufficient to set an RDA.
- Elemental magnesium
- The amount of magnesium itself in a compound. It is smaller than the total weight of magnesium citrate, glycinate or oxide.
- Hypomagnesemia
- A magnesium concentration in blood below the laboratory range. It can reflect medication effects, gastrointestinal losses, kidney losses or other illness.
- Observational study
- Research that observes exposures and outcomes without assigning treatment. It can find an association but cannot by itself prove cause.
- Placebo
- An inactive comparison made to resemble the tested treatment.
- Recommended Dietary Allowance (RDA)
- The average daily intake sufficient for nearly all healthy people in an age and sex group. It is not a treatment dose.
- Serum
- The liquid portion of blood after clotting. Serum magnesium contains less than 1% of the body's magnesium.
- Tolerable Upper Intake Level (UL)
- The highest chronic daily intake unlikely to pose risk for most people in a population. The U.S. magnesium UL counts supplements and medicines only.
How this guide was researched
This draft uses the current NIH ODS magnesium monograph, FDA's magnesium and hypertension evidence decision, three randomized trials with complete schedules, and a systematic review of sleep trials. The current review retrieved and read the relevant source text on October 9, 2026. Older Doserly research files were used to identify claims to recheck, not as proof that those claims were correct.
The protocol table keeps every trial's salt, elemental amount, population, frequency and duration together. It does not turn an RDA into a supplement prescription or treat the UL as a target.
How this guide was made
Research and drafting were AI-assisted. This manuscript is a draft for Doserly editorial review and has not been independently clinically reviewed. Doserly makes a health-tracking app and operates Doserly Academy, both promoted in the guide. Read the editorial policy for the correction and update process.
Explore the sources
These are the sources cited in this draft. Official monographs, regulatory reviews, trials and systematic reviews answer different questions.
Showing 10 sources
- 01
Magnesium - Health Professional Fact Sheet ↗
Official nutrient monograph
Relevant full-page sections reviewed.
Detail: Adult RDAs, supplemental-and-medication-only UL, food sources, salt absorption, deficiency assessment, harms, medicine interactions and evidence summaries.
- 02
FDA Announces Qualified Health Claim for Magnesium and Reduced Risk of High Blood Pressure ↗
Regulatory evidence review
Official summary and linked review letter checked.
Detail: FDA permits only qualified language because the evidence is inconsistent and inconclusive.
- 03
Prophylaxis of Migraine with Oral Magnesium ↗
Randomized controlled trial
Abstract and publisher extract reviewed.
Detail: 81 adults; 600 mg magnesium as trimagnesium dicitrate every morning for 12 weeks; attack frequency fell more than placebo; diarrhea 18.6%, gastric irritation 4.7%.
- 04
The effect of magnesium supplementation on primary insomnia in elderly: A double-blind placebo-controlled clinical trial. ↗
Randomized controlled trial
Full text reviewed.
Detail: 46 adults aged 60–75; 250 mg elemental magnesium as oxide twice daily for 8 weeks; some subjective measures improved, total sleep time did not significantly differ.
- 05
Effect of Magnesium Oxide Supplementation on Nocturnal Leg Cramps: A Randomized Clinical Trial. ↗
Randomized controlled trial
Abstract and methods/results extract reviewed.
Detail: 94 adults; 520 mg elemental magnesium at bedtime for 4 weeks; no significant advantage over placebo.
- 06
Oral magnesium supplementation for insomnia in older adults: a Systematic Review & Meta-Analysis. ↗
Systematic review and meta-analysis
Full-text extracts reviewed.
Detail: Three trials, 151 older adults; low to very low certainty; shorter sleep-onset latency, no statistically significant gain in total sleep time. The 2024 correction addresses search description, PRISMA counts and wording; it is linked separately. [10]
- 07
Questions and Answers on Dietary Supplements ↗
Regulatory overview
Current official page reviewed.
Detail: U.S. supplements generally do not receive FDA premarket approval; firms bear initial responsibility and FDA conducts postmarket oversight.
- 08
Product Licensing ↗
Regulatory overview
Current official page reviewed.
Detail: Natural health products require a product licence before sale in Canada and authorized labels carry an NPN or DIN-HM.
- 09
Magnesium Bisglycinate Supplementation in Healthy Adults Reporting Poor Sleep ↗
Randomized controlled trial
Full text and trial report reviewed.
Detail: 155 adults age 18–65 with self-reported poor sleep; 250 mg elemental magnesium as bisglycinate daily for 28 days; small improvement in insomnia severity, no objective sleep measurement.
- 10
Correction: Oral magnesium supplementation for insomnia in older adults: a Systematic Review & Meta-Analysis. ↗
Published correction
December 19, 2024 notice checked.
Clarifies literature search, screening counts and wording.
No matching sources
Try a different term or show the full list.