
In this guide
What is oral testosterone?
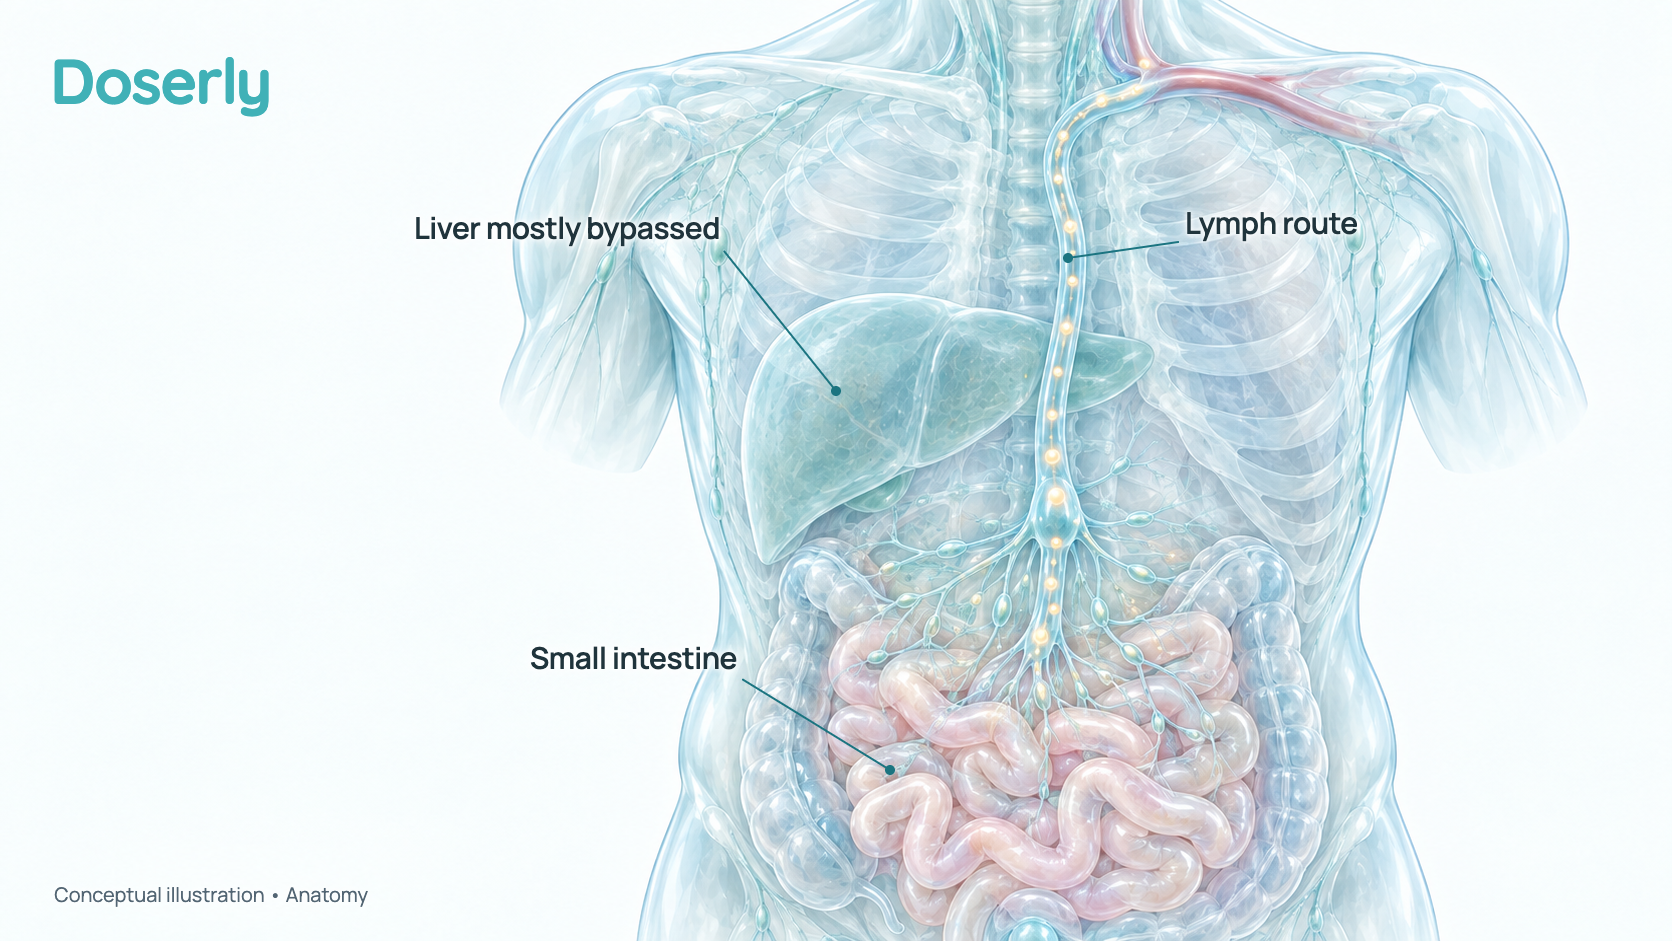
Oral testosterone is a prescription testosterone capsule, usually taken twice a day with meals. Every oral product sold today contains testosterone undecanoate: testosterone with a long fatty tail attached. With a meal, the tail carries the medicine into the gut's lymph vessels, so most of it skips the liver's first pass; plain testosterone swallowed on its own barely changes blood levels. [1], [2], [3]
Undecanoate is an 11-carbon fatty acid, the ester (chemical tail) joined to testosterone; enzymes in the body cut it off to release ordinary testosterone. Because the tail adds weight, 237 mg of testosterone undecanoate contains about 150 mg of testosterone. [4], [5]
It is labeled for men with hypogonadism (low testosterone from a medical cause): either primary hypogonadism, where the testicles fail, or hypogonadotropic hypogonadism, where the brain and pituitary do not send enough signal. US labels still say its safety and benefit in "age-related" low testosterone have not been established. Jatenzo, approved in 2019, was the first US oral testosterone undecanoate. [4], [6], [7]
Three products are sold in the United States: Jatenzo, Kyzatrex and Tlando. Canada markets Jatenzo and a generic 40 mg capsule of the older Andriol type, and has approved Kyzatrex (checked September 2026). [7], [8], [9]
It is not the old "testosterone pill." Methyltestosterone, a chemically altered (17-alpha-alkylated) form used since the 1930s, is still sold in the United States but can damage the liver, and the American Urological Association (AUA) says it should not be prescribed. Testosterone undecanoate is not alkylated, and its labels say it is not known to cause those liver effects. [10], [5], [11], [6]
Testosterone is a steroid hormone, and oral testosterone is a controlled substance: Schedule III in the United States. Compounded or "plain" oral testosterone sold online is not covered by these labels, and no oral form of plain testosterone is licensed. Supplements sold as "testosterone boosters" are something else again (raising testosterone naturally). [12], [13]
Typical Oral Testosterone Protocols
| Source | Amount each time | How often | Daily total | Weekly total | Adjusted by | Source type |
|---|---|---|---|---|---|---|
| US label · Jatenzo (Canada: same dosing) | 237 mg to start; range 158–396 mg | Twice daily, morning and evening, with food | 474 mg to start (316–792 mg) | 3,318 mg to start | Serum testosterone 6 hours after the morning dose, 7 or more days after a change: no change at 425–970 ng/dL; one step up or down outside that | Label 316 mg is two 158 mg capsules and 396 mg is two 198 mg capsules |
| US label · Kyzatrex (Canada: same dosing) | 200 mg to start; range 100–400 mg | Twice daily with food; the lowest step is 100 mg once daily with breakfast | 400 mg to start (100–800 mg) | 2,800 mg to start | Serum testosterone 3–5 hours after the morning dose, 7 days after starting or a change: no change at 460–971 ng/dL | Label |
| US label · Tlando | 225 mg (two 112.5 mg capsules) | Twice daily, morning and evening, with food | 450 mg | 3,150 mg | No dose steps: serum testosterone 8–9 hours after the morning dose at 3–4 weeks; continue at 300–1,080 ng/dL, otherwise stop | Label |
| Canadian label · Taro 40 mg capsule (Andriol type) | Half the daily total at each dose | Twice daily, morning and evening, with a meal | 120–160 mg for 2–3 weeks, then 40–120 mg | 840–1,120 mg, then 280–840 mg | Clinical response; testosterone about 5 hours after a dose, not fasting | Label |
| Endocrine Society 2018 · 40 mg capsules (outside the US) | 40–80 mg | 2 or 3 times daily with meals | 80–240 mg | 560–1,680 mg | Serum testosterone 3–5 hours after a dose with a fat-containing meal; aim mid-normal | Guideline |
| European Association of Urology (EAU) 2026 · self-emulsifying capsules (US type) | 100–237 mg | Twice daily | 200–474 mg | 1,400–3,318 mg | Not stated in the table | Guideline |
| Society for Endocrinology (UK) 2022 · 40 mg capsules | 40–120 mg (1–3 capsules) | 2 or 3 times daily with meals | 80–360 mg | 560–2,520 mg | Not stated; the guideline calls it "not a preferred treatment option" | Guideline |
The three US capsules all use two doses a day with meals, starting at 200–237 mg per dose, each judged by one blood test a set number of hours after the morning dose. The older 40 mg capsule uses 40–360 mg a day across its label and guidelines; its milligrams cannot be compared with the newer capsules, which absorb differently. [4], [6], [1], [9], [14], [16]
- Titration Adjusting the dose in steps
- Each US product has its own draw time and band for an ordinary serum tube: Jatenzo 6 hours after the morning dose (425–970 ng/dL, about 15–34 nmol/L), Kyzatrex 3–5 hours after (460–971 ng/dL, about 16–34 nmol/L) and Tlando 8–9 hours after (300–1,080 ng/dL, about 10–37 nmol/L). Jatenzo and Kyzatrex recheck 7 days after each change; Tlando has no dose steps, so a result outside its band means stopping. In Jatenzo's approval trial, 72% of men ended on a higher dose. Hematocrit and blood pressure can also force a change. [4], [6], [1], [5] See why draw timing matters.
- Breaks and cycles
- Not applicable. Testosterone replacement is continuous treatment; no label or guideline describes planned breaks or cycles, and the UK Society for Endocrinology expects lifelong treatment once the diagnosis is confirmed. Stopping is a separate decision (what happens when you stop). [16]
Read the units. Oral doses are milligrams of testosterone undecanoate per dose, counted in capsules; there is no volume to draw. Jatenzo's highest dose, 396 mg twice daily, is two 198 mg capsules each morning and evening, 792 mg a day. Tlando's 225 mg is two 112.5 mg capsules per dose. Oral milligrams cannot be compared one for one with injection or gel milligrams, because only a small share of a swallowed dose reaches the blood (about 7% for the older 40 mg capsule). Doserly's TRT dose calculator is built for injections; the testosterone unit converter switches blood results between ng/dL and nmol/L. [4], [1], [9]
These are labeled and guideline doses; prescribers adjust them using blood tests and symptoms. The schedules above are for adult men. For women, see testosterone therapy for women, which uses different products and far smaller doses.
Cautions for every schedule above. The labels rule it out with breast cancer, known or suspected prostate cancer and pregnancy, and advise against it with uncontrolled high blood pressure. It lowers sperm production (fertility), and blood pressure, hematocrit, cholesterol and PSA (prostate-specific antigen) need checking (monitoring), plus prolactin on Tlando. [4], [6], [1]
Where these numbers come from
The US label rows come from the current labels for Jatenzo (DailyMed version effective September 30, 2025), Kyzatrex (effective August 26, 2026) and Tlando (effective February 25, 2026). The Canadian Jatenzo and Kyzatrex monographs (December 2025 and June 2026) give the same dosing as the US labels. The Taro row comes from its Canadian monograph (October 25, 2018), which matches the older Restandol Testocaps product information. Daily and weekly totals are simple arithmetic; the labels state amounts per dose or per day. [4], [6], [1], [2], [17], [9], [18]
The guideline rows each come from one document: the Endocrine Society guideline (2018, table of formulations available outside the US), the EAU guideline (2026 preparations table) and the Society for Endocrinology guideline (2022, Table 2). The Canadian Urological Association (CUA) guideline (2021) and the Endocrine Society of Australia (ESA) position statement (2016) repeat the 40 mg capsule's label schedule (120–160 mg a day in two doses to start; 40 mg two or three times a day) and are not listed again. [14], [15], [16], [19], [20]
Not used for any row: the EAU table's other oral line, which reads "120-240mg 2 or 3 times daily" for the 40 mg capsule and would mean up to 720 mg a day if read per dose, far above every label; the British Society for Sexual Medicine (BSSM) table, which gives a frequency but no amount; the range used in Kyzatrex's 12-month safety study (200 mg once daily to 400 mg twice daily), a study range rather than a labeled schedule; once-daily, "pulsed" or oil-dissolved schedules from online discussions, which no source gives as a complete schedule; and a conference abstract of a higher Kyzatrex starting dose that could not be checked against a full report. [15], [21], [6]
What do clinic protocol sources use?
| Source | Amount each time | How often | Daily total | Weekly total | Adjusted by | Source type |
|---|---|---|---|---|---|---|
| US academic urology clinic trial (2024) · men switched from other testosterone | 237 mg; 316 mg if low at 1 month | Twice daily with food | 474 mg (632 mg after the increase) | 3,318 mg (4,424 mg) | Serum testosterone 4–6 hours after a dose at 1, 3 and 6 months; 12 of 30 men (40%) needed the increase at 1 month | Clinic protocol source Men were referred for blood removal if hematocrit went above 52%, a lower line than the 54% most guidelines use |
Only one peer-reviewed practice source gives a complete oral schedule. It follows the Jatenzo label with a wider draw window (4–6 hours), and 76.0% of men (19 of 25) were in its target range at 6 months. [22]
What is oral testosterone commonly used for?
Its approved use is replacing testosterone in adult men whose bodies cannot make enough because of a medical condition. The labels name two groups: testicular failure (from undescended testicles, twisting, infection, removal, Klinefelter syndrome, chemotherapy or toxic damage) and a missing signal from the brain or pituitary (from a hormone deficiency, a tumor, injury or radiation). [4]
People and prescribers often weigh capsules for practical reasons: no needles, and no risk of passing testosterone to a partner or child by skin contact, which is why testosterone gels carry a boxed warning and the capsules do not. The trade-offs are two doses a day with meals, blood-pressure checks and a higher price than generic injections (cost). [23], [4], [24]
What does oral testosterone improve?
Trials of testosterone in general, mostly gels, show the clearest gains in sexual desire and activity (results timeline). In TRAVERSE's sexual-function study of 1,161 men with low libido, testosterone gel gave about 0.5 more sexual acts per day than placebo gel at 6 months (0.49, 95% confidence interval 0.19 to 0.79) and improved desire, but not erections. [25] Studies of the capsules add this:
- Sexual function and mood. In Tlando's 52-week trial, sexual desire and frequency improved by similar amounts on the capsule and a daily gel, with larger gains in some mental-health scores on the capsule, in an analysis that did not adjust for the many comparisons made. Psychosexual scores improved in the 69 men who finished 2 years of Jatenzo. Both were open-label: everyone knew what they were taking. [26], [27]
- Body composition and bone. After a year on Jatenzo, lean mass rose 3.2 kg, fat fell 2.4 kg and bone density rose slightly (open-label, no placebo). [28]
- Older men with borderline levels. In placebo-controlled trials of the older capsule, lean mass rose and fat fell, but strength, function and overall symptom scores did not improve. [29], [30], [31]
Kyzatrex's approval trial did not measure symptoms. [32]
How long does oral testosterone take to work?
Blood levels rise within hours, and the day's lowest level settles by about day 7, which is why Jatenzo and Kyzatrex recheck a week after each change. Symptoms change more slowly. The Canadian Urological Association tells men to expect changes in libido, energy and sexual function after 3 months or longer, and in body composition and bone after 6 months or more. [33], [4], [19]
Where do oral testosterone protocols differ?
The labels agree on two doses a day with food, and differ on whether the dose can change, when blood is drawn and how much food is enough.
Fixed dose or adjustable dose?
Tlando uses one fixed dose; Jatenzo and Kyzatrex adjust. FDA turned Tlando down three times before approving it in 2022, the last time noting too few men with a peak level at or below 1,500 ng/dL (74%, against a target of 85%). The approved fixed dose rests on a trial in which 80% of 95 men reached the normal range in 24 days without dose changes; in a 52-week trial, 43.5% never needed a change. [34], [35], [26]
The adjustable products use their range. In Jatenzo's approval trial, about 72% of men were moved up (32% to 316 mg and 40% to 396 mg twice daily), 26% stayed on 237 mg and 3% went down. On Kyzatrex, 43.8% were on 600 mg a day by day 90 and 8.3% on 200 or 100 mg a day; heavier men and men with diabetes more often needed higher doses. [5], [17], [32]
The practical difference: on Tlando, a low result means stopping or switching, not a higher dose.
When should blood be drawn on oral testosterone?
At the time your product's label names, counted from the morning capsule. A morning test before the first capsule, or a random draw, does not match any label's band.
| Product or guideline | When to draw | Result that means "no change" |
|---|---|---|
| Jatenzo (label) | 6 hours after the morning dose, at least 7 days after a change | 425–970 ng/dL (about 15–34 nmol/L) |
| Kyzatrex (label) | 3–5 hours after the morning dose, 7 days after a change | 460–971 ng/dL (about 16–34 nmol/L) |
| Tlando (label) | 8–9 hours after the morning dose, 3–4 weeks after starting | 300–1,080 ng/dL (about 10–37 nmol/L) to continue |
| Endocrine Society 2018 (40 mg capsule) | 3–5 hours after a dose taken with a fat-containing meal | Mid-normal range |
| Endocrine Society of Australia 2016 | After 2 weeks; trough testing is "not feasible" with oral testosterone | Not given |
Each band was built from its own product's trial data, so the windows cannot be swapped. In Jatenzo's trial, adjusting the dose from one sample 4–6 hours after a dose would have put as many men in range as a full 24-hour profile (93% vs 87%). [5]
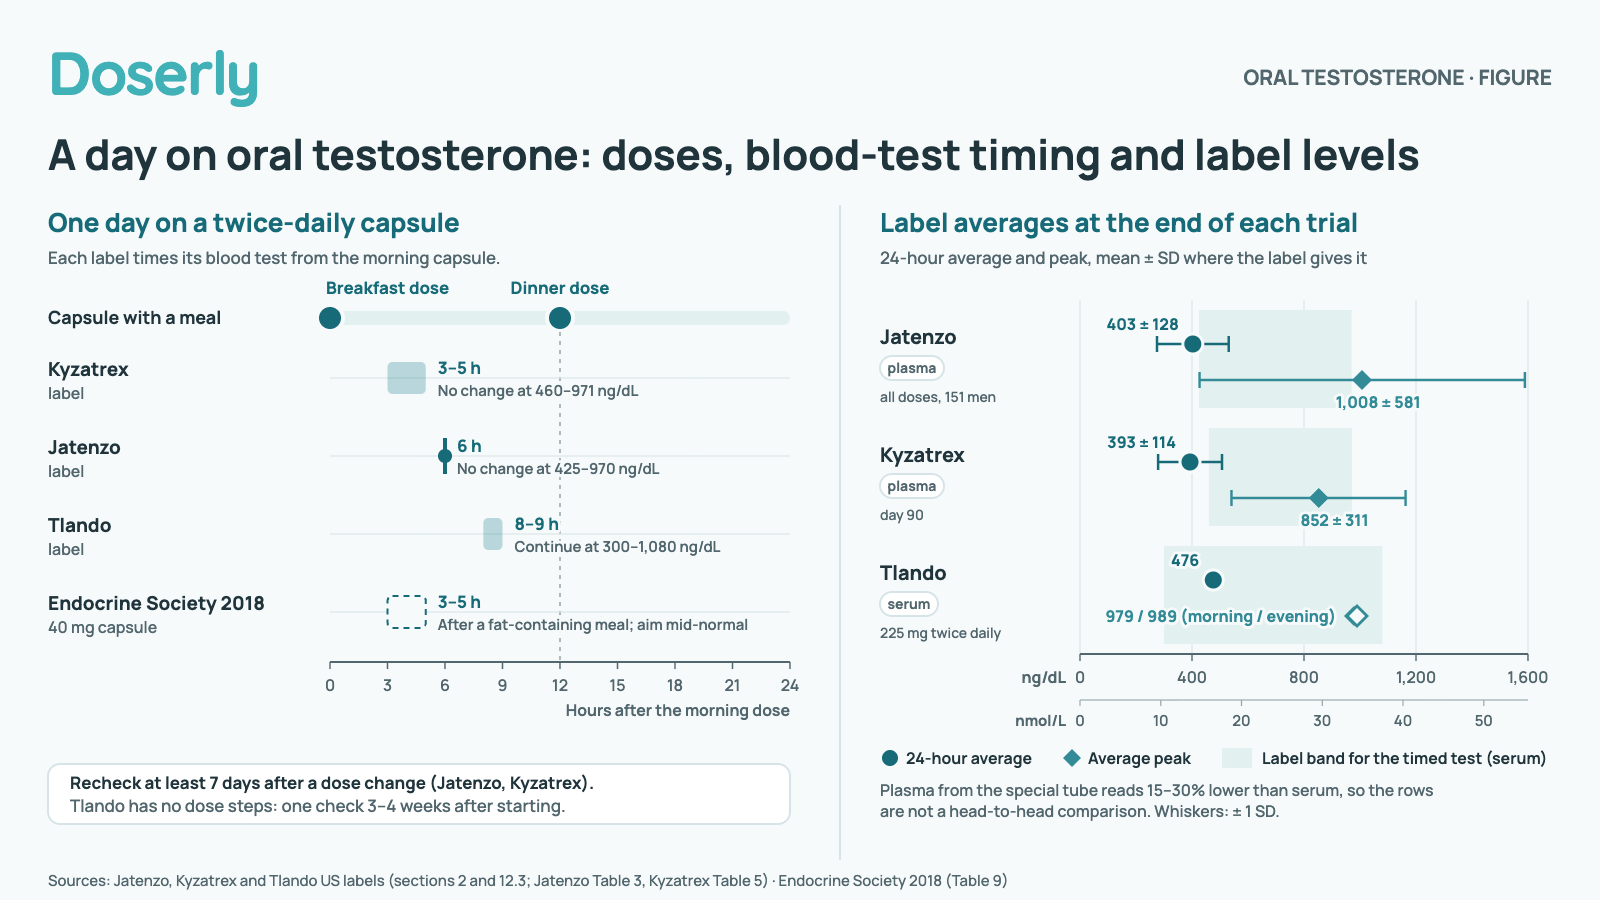
A day on oral testosterone: doses, blood-test timing and label levels
One day on a twice-daily capsule
A capsule with breakfast and another with dinner, about 12 hours apart. Each label times its blood test from the morning capsule (bar: the window; line: an exact time).
- Kyzatrex (label)
- 3–5 h after the morning dose. No change at 460–971 ng/dL.
- Jatenzo (label)
- 6 h after the morning dose. No change at 425–970 ng/dL.
- Tlando (label)
- 8–9 h after the morning dose. Continue at 300–1,080 ng/dL.
- Endocrine Society 2018 (40 mg capsule)
- 3–5 h after the morning dose. After a fat-containing meal; aim mid-normal.
Recheck at least 7 days after a dose change (Jatenzo, Kyzatrex). Tlando has no dose steps: one check 3–4 weeks after starting.
Label averages at the end of each trial
Dot: 24-hour average. Diamond: average peak. Whiskers ± SD where the label gives it. Shaded: the label band for its timed serum test.
- Jatenzo (plasma)
- Average 403 ± 128 ng/dL; peak 1,008 ± 581 ng/dL. All doses, 151 men. Label band 425–970 ng/dL.
- Kyzatrex (plasma)
- Average 393 ± 114 ng/dL; peak 852 ± 311 ng/dL. Day 90. Label band 460–971 ng/dL.
- Tlando (serum)
- Average 476 ng/dL; peak 979 (morning) and 989 (evening) ng/dL. 225 mg twice daily. Label band 300–1,080 ng/dL.
Plasma from the special tube reads 15–30% lower than serum, so the rows are not a head-to-head comparison. A result only makes sense against its own product’s draw time and band.
Do you need a special blood tube? No. The trials used tubes with an enzyme blocker (sodium fluoride) that read 15–30% lower than plain tubes, but the Jatenzo and Kyzatrex labels set their bands for ordinary serum, and researchers judged the difference to matter little in practice. [4], [32], [36]
How much fat does the meal need?
A normal meal. Every label says to take the capsules with food; none sets a gram target. Here is what the food studies found:
| Product or study | What was tested | What happened |
|---|---|---|
| Jatenzo (label) | Breakfasts with 15, 30 and 45 g of fat, and a high-calorie, high-fat breakfast | 30 g, 45 g and high-fat were comparable; 15 g gave 25% less exposure than 30 g |
| Kyzatrex (label) | Breakfasts with 16%, 33% and 45% of calories from fat, against fasting | Exposure 37%, 87% and 94% higher than fasting; in the main trial, men's meals varied in fat, and results were similar in the low- and high-fat groups |
| Tlando (label) | Low-, moderate- and high-fat meals against fasting (13–14 men) | Similar with any meal; fasting cut the peak by about 65% and total exposure by about 38% |
| Early Jatenzo-type capsule (16 men) | Meals with 20%, 30% and 50% fat, and fasting | No difference between 20% and 50% fat; fasting gave half the exposure or less |
| Andriol Testocaps (24 postmenopausal women) | Meals with 0.6–44 g of fat | About five times more exposure with 19 g than 0.6 g; 44 g added little |
[4], [6], [32], [1], [37], [38]
The plain answer: take it with an ordinary meal. An empty stomach or a nearly fat-free snack cuts absorption a lot; extra fat beyond a normal meal adds little. The "30 g of fat" figure repeated online was Jatenzo's reference breakfast, not a minimum every product requires. A similar breakfast on test days makes results easier to compare.
Can you take oral testosterone once a day?
Only Kyzatrex labels a once-daily dose, and only its lowest one: 100 mg with breakfast. No label or trial supports once-daily Jatenzo or Tlando. Each dose lasts only hours (the ester's half-life is about 2 hours), which is why doses are split between morning and evening, and the label's blood-test band was not built for a single daily dose. [6], [1], [9] Some people try it anyway; what they report is in the community section.
Can you switch between Jatenzo, Kyzatrex and Tlando?
Not milligram for milligram. The Kyzatrex and Tlando labels state that they are "not substitutable with other oral testosterone undecanoate products," and the Orange Book lists no generic or interchangeable version. A switch means starting the new product's own schedule and blood-test timing. No label covers switching from injections or gels; in the clinic trial above, men stopped their previous testosterone and waited before starting. [6], [1], [7], [22]
What happens when you stop oral testosterone?
The capsule itself is gone within a day; your own hormone production takes much longer to return.
- The last dose. With the older capsule, levels were back to baseline about 10 hours after a dose. [9]
- Your own testosterone. Capsules switch off the pituitary's signals to the testicles, LH (luteinizing hormone) and FSH (follicle-stimulating hormone); both fell about 70% in Jatenzo's approval trial. No study has tracked their recovery after capsules. After 2 years of undecanoate injections in the T4DM trial, LH and FSH recovered slowly over 12 months, and full recovery may take longer. With a lasting cause of hypogonadism, low testosterone is expected to return. [5], [39], [16]
- Sperm. No study has measured sperm recovery after capsules. In contraceptive trials of healthy men on other hormone regimens, sperm counts returned to 20 million per mL in 67% within 6 months, 90% within 12 months and 100% within 24 months. The labels warn that effects on fertility may be irreversible. [40], [4]
- Tapering. The Canadian Urological Association says no taper is needed when stopping. [19]
See stopping TRT for the full picture.
How does oral testosterone compare with other forms?
It is one of the shortest-acting forms: two peaks a day, no needles and nothing to transfer to other people by touch. In exchange it needs meals, raises blood pressure on its labels and raises DHT (dihydrotestosterone) relative to testosterone more than other forms. [1], [4], [14]
Why does a swallowed dose need a meal?
Swallowed testosterone is normally broken down by the liver before it reaches the rest of the body. Testosterone undecanoate avoids much of that because its fatty tail dissolves in dietary fat. In the gut lining, that fat is packed into tiny particles (chylomicrons) that enter the lymph vessels rather than the blood vessels leading to the liver. The main lymph vessel, the thoracic duct, empties into a large vein near the collarbone, and the ester is then cut to testosterone. [1], [2]
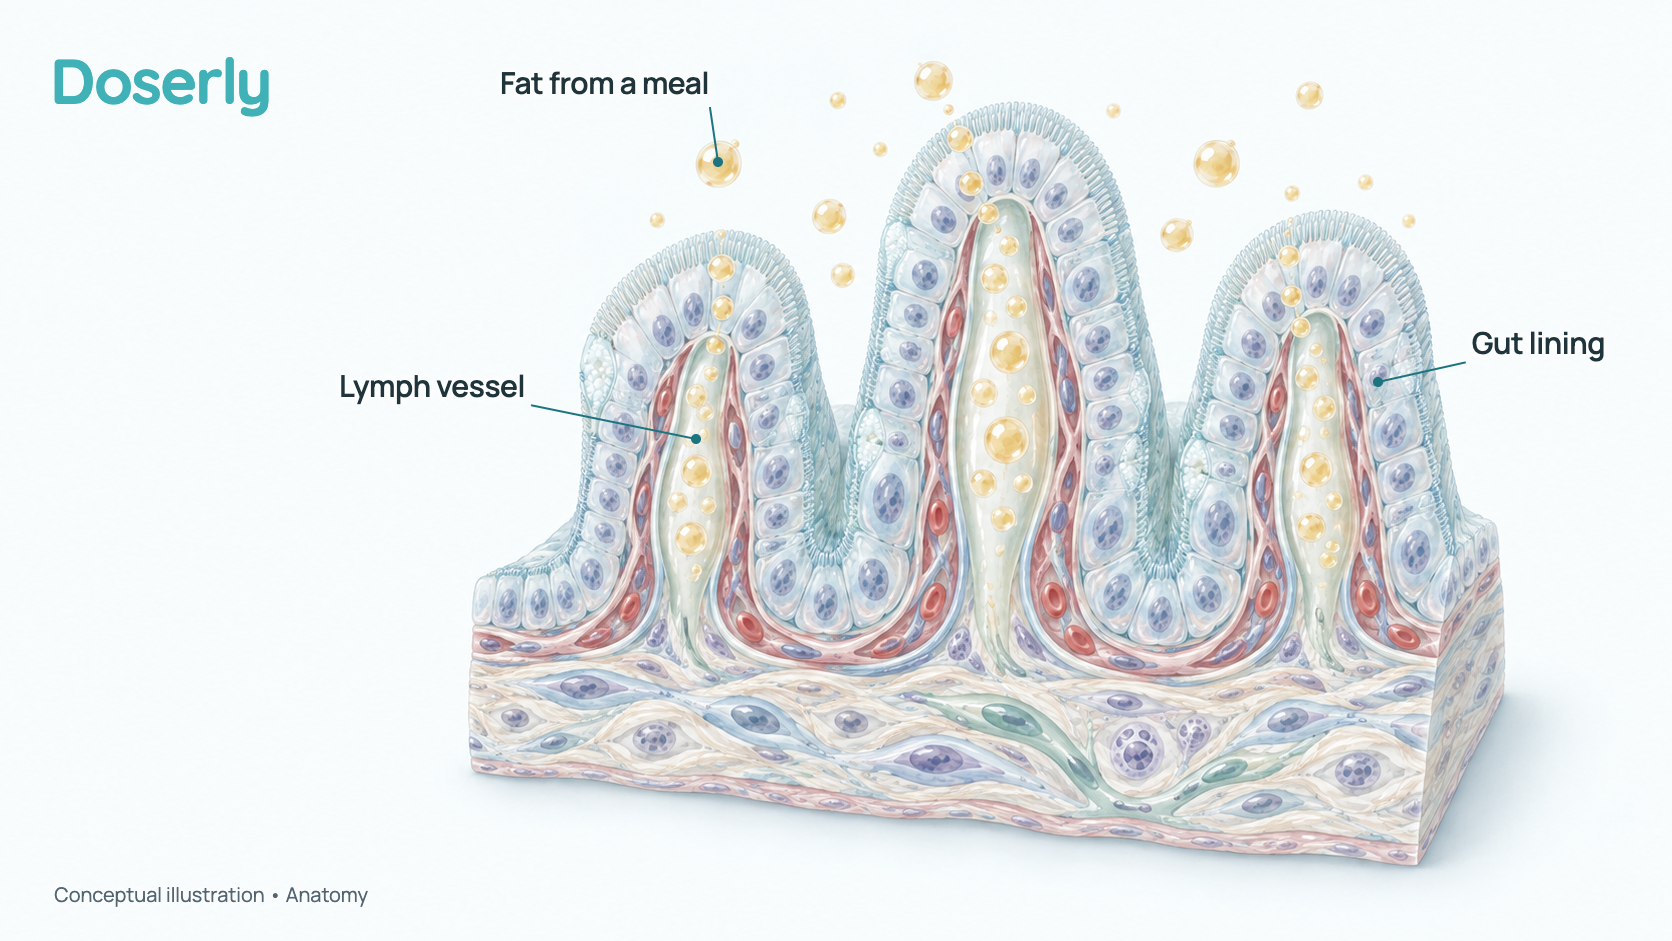
The bypass is partial: Canada's monographs call it "partially circumventing" the liver, and in dogs 84% of the testosterone reaching the blood came through the lymph. Only about 7% of a dose of the older capsule reached the blood as testosterone (its bioavailability). Tlando's 52-week trial report suggests a small first pass through the liver explains why capsules lower HDL cholesterol and SHBG. [2], [41], [9], [42], [26]
How long does one dose last?
Levels peak about 5 hours after a capsule (the median on Tlando; 4–5 hours for the older capsule, which stayed raised for at least 8 hours). The ester's half-life is about 2 hours, and freed testosterone itself has a half-life of only 10 to 100 minutes. Each label reports average and peak levels at the end of its trial. [1], [18], [9]
| Product | Average level over 24 hours | Average peak | How measured |
|---|---|---|---|
| Jatenzo | 403 ± 128 ng/dL | 1,008 ± 581 ng/dL | Special plasma tube, all doses |
| Kyzatrex | 393 ± 114 ng/dL | 852 ± 311 ng/dL | Special plasma tube, day 90 |
| Tlando | 476 ng/dL | 979 and 989 ng/dL (morning and evening) | Ordinary serum, 225 mg twice daily |
Plasma from the special tubes reads lower than serum, so the rows are not directly comparable. Most men's peaks stayed within each study's FDA limit (83% on Jatenzo, 88% on Kyzatrex, 82% on Tlando); a few percent went higher. [4], [6], [1]
Why is DHT higher on oral testosterone?
An enzyme in the gut wall (5-alpha-reductase) turns some of the ester into a DHT form before it reaches the blood, so DHT runs high relative to testosterone. The ratio rose about threefold in an early study of the Jatenzo-type capsule, and the Endocrine Society lists a "high DHT:T ratio" as a drawback. In Jatenzo's trial average DHT (73 ng/dL) was just above the upper limit of 65 ng/dL, no higher than with a skin solution; on Kyzatrex it was about 21% of testosterone. [1], [33], [14], [32], [5]
No study links the higher DHT on capsules to hair loss or prostate problems. Finasteride, which blocks DHT production, did not lower DHT during 7 days of oral testosterone undecanoate in 11 men. [43]
Does oral testosterone change cholesterol?
It lowers HDL ("good") cholesterol more than gels. HDL fell 13.9% on Jatenzo, with 28.9% of men dropping below the normal range against 14.8% on a skin solution. It fell 14.0% on Kyzatrex, and more on Tlando than on gel in the 52-week trial (−0.15 vs −0.05 mmol/L). The Kyzatrex label also reports falls in total cholesterol, LDL and triglycerides. All three labels ask for periodic lipid checks. [5], [32], [26], [6]
How should oral testosterone be stored?
Store the capsules at room temperature, dry and in their original bottle. Each product's label sets its own rules, so the leaflet in your box is the final word. [4], [6], [1], [9]
| Product | Storage |
|---|---|
| Jatenzo | 20–25 °C; short trips to 15–30 °C allowed; keep dry (Canada: avoid refrigerating) |
| Kyzatrex | 20–25 °C; short trips to 15–30 °C allowed; keep dry, in the original bottle |
| Tlando | 20–25 °C; short trips to 15–30 °C allowed |
| Taro 40 mg (Canada) | 15–30 °C; protect from light and moisture; do not refrigerate |
Left in a hot car? No label addresses it; the labels allow only short periods up to 30 °C, so capsules that have softened or stuck together should be checked with a pharmacist. Only the original Andriol capsule needed a fridge; its castor-oil reformulation keeps at room temperature for about 3 years. [4], [44]
For carrying capsules on a trip, see traveling with testosterone.
Jatenzo, Kyzatrex and Tlando: how do they differ?
They contain the same ester and share the same class warnings, but each is its own product with its own dose, blood test and trial record.
| Jatenzo | Kyzatrex | Tlando | |
|---|---|---|---|
| US approval | March 27, 2019 | July 27, 2022 | March 28, 2022 |
| Capsules | 158, 198, 237 mg | 50, 150, 200 mg (100 mg discontinued) | 112.5 mg |
| Starting dose | 237 mg twice daily | 200 mg twice daily | 225 mg twice daily |
| Dose changes | 158–396 mg twice daily | 100 mg once daily to 400 mg twice daily | None: continue or stop |
| Blood test | 6 hours after the morning dose | 3–5 hours after | 8–9 hours after, at 3–4 weeks |
| 24-hour blood pressure rise (separate trials) | +4.9/2.5 mm Hg at 4 months | +1.7/0.6 mm Hg at 4 months | +4.3/1.4 mm Hg at 4 months |
| Warning only on this label | Depression and suicidal thoughts | None beyond the class warnings | Prolactin rise |
| Canada | Marketed since April 24, 2026 | Approved, not yet marketed | Not available |
Checked September 2026. [7], [4], [6], [1], [8]
Jatenzo
Jatenzo is testosterone undecanoate in 158 mg (red), 198 mg (white) and 237 mg (orange) capsules, taken twice daily with food. Its fill is a self-emulsifying oil mix (it forms tiny droplets in gut fluid) that includes peppermint oil, the source of the "minty burps" some men describe. [4], [5]
A long road to approval. First filed in January 2014, it was voted down twice by FDA's outside advisers (17 to 4, then 10 to 9 in January 2018), and FDA's March 2018 rejection cited "a clinically meaningful mean increase in blood pressure." FDA approved it on March 27, 2019; it is now sold by Tolmar. In its approval trial, 87% of 166 men reached the normal range (evidence). [45], [46], [4]
What its label adds:
- Blood pressure: the largest measured rise of the three, 4.9/2.5 mm Hg at about 4 months, not yet leveled off (blood pressure); heart rate rose 2.2 beats per minute. [4]
- Mood: 2 of 166 men (1.2%) reported new or worsening depression, and 1 of 569 across all trials (0.2%) had suicidal thoughts. [4]
- Adrenal glands: in some dog studies the ester shrank the adrenal glands, so FDA required a one-year study of adrenal function in men; the label calls the clinical significance unknown. [45], [4]
- Age: no men over 65 were in the 4-month trial. [4]
Canada. Authorized in December 2025 and marketed since April 24, 2026, with the same dosing. [2], [8]
Kyzatrex
Kyzatrex is testosterone undecanoate in white 50, 150 and 200 mg capsules, taken twice daily with food, with the widest dose range of the three. Its self-emulsifying fill includes vitamin E and plant sterol esters. [6], [32]
Approval. Marius Pharmaceuticals filed it in December 2020, received a rejection letter in October 2021 and gained approval on July 27, 2022, without an advisory committee. A 50 mg capsule was approved on August 25, 2026, and the Orange Book now lists the 100 mg capsule as discontinued, although the label still lists it. The label does not say which capsules now make up a 100 mg dose. Its single-arm approval trial put 88% of men in range and did not measure symptoms or hematocrit (evidence). [47], [48], [7], [6]
What its label adds:
- Blood pressure: the smallest measured rise of the three, 1.7/0.6 mm Hg at 4 months; a history of blood-pressure treatment and diabetes predicted larger rises. [6], [49]
- Alcohol: alcohol with a high-fat meal did not change absorption. [6]
- Age: its trials included no men aged 65 or older. [6]
Access. Kyzatrex does not appear in US pharmacy acquisition-cost or Medicare Part D data, and a 2025 review describes it as offering self-pay access (cost). In Canada it is approved but not yet marketed (checked September 2026). [50], [51], [52], [8]
Tlando
Tlando is testosterone undecanoate in a 112.5 mg capsule (white body, grey cap), taken as two capsules twice daily with food at one fixed dose. It was developed by Lipocine and is sold by Verity Pharmaceuticals. [1], [53]
Approval. FDA rejected it in June 2016, May 2018 and November 2019, citing among other problems blood-pressure increases (2018) and too many high peak levels (2019). It received tentative approval in December 2020 and final approval on March 28, 2022. [34], [53]
The evidence. In its main trial, 80% of 95 men reached the normal range on the fixed dose in about 24 days (95% confidence interval 72% to 88%), and a 52-week trial against AndroGel 1.62% followed 315 men (evidence). [1], [35], [26]
What its label adds:
- Prolactin: this pituitary hormone rose in 6 of 95 men (6.3%). The label asks for a prolactin test before starting and 3–4 months after, and says to stop if it stays high; it is the only one of the three with this warning. [1]
- Blood pressure: 4.3/1.4 mm Hg after about 4 months; the published report of the same study, using a different set of men, gave 3.8 mm Hg. [1], [54]
- Hematocrit checks: about every 3 months in the first year, then every 6 months. [1]
- Age: 16 of the 95 men (16.8%) in the main trial were over 65. [1]
Tlando is sold only in the United States (checked September 2026). [8], [55]
Andriol, Andriol Testocaps and the 40 mg capsule
Andriol is the original oral testosterone undecanoate: a 40 mg capsule whose first authorization, in Ireland, dates from 1978, and which was never approved in the United States. The first version needed a fridge; the reformulated Andriol Testocaps (also sold as Restandol Testocaps) keeps at room temperature. [18], [14], [44]
Levels peaked at about 40 nmol/L (about 1,150 ng/dL) 4–5 hours after a dose, but in men followed for 10 years or more, levels 7–9 hours after a dose averaged 5.4–6.5 nmol/L, below the 8–24 nmol/L normal range, and an older comparison found the most variable levels of any form. [18], [56], [57]
Guidelines now rate it poorly. The European Academy of Andrology says it "is no longer considered a viable therapeutic option, since its absorption is unpredictable and highly dependent on food intake." The UK Society for Endocrinology calls it "not a preferred treatment option," and the British Society for Sexual Medicine says oral therapies are "rarely used in the UK." [58], [16], [21]
Where it is still sold. In Canada, a generic 40 mg capsule (Taro-Testosterone) is marketed, and Ontario's public formulary lists it at CAD 0.5649 per capsule while listing Andriol itself as "not a benefit" (checked September 2026). [8], [59]
Which oral testosterone products are no longer sold?
Checked September 2026.
- Andriol, Canada: cancelled on January 29, 2018. Another generic 40 mg capsule has been dormant since August 1, 2025. [8]
- Restandol Testocaps, United Kingdom: discontinued by its maker, according to an NHS formulary, which gives no date. No oral testosterone undecanoate has current UK product information. [60], [55]
- Andriol Testocaps, Australia: not among Australia's current testosterone product information documents; the cancellation date could not be confirmed. [61]
- Pantestone, France: no longer in France's public medicines database. Other European countries were not checked for this guide. [62]
- Kyzatrex 100 mg capsule, United States: listed as discontinued in the Orange Book; the product listing shows marketing ended in September 2025. [7], [6]
What does oral testosterone do to fertility, estrogen and red blood cells?
These effects come with every form of testosterone and each has its own hub guide; here is what is specific to capsules.
Fertility. Assume capsules lower sperm production. All three labels warn that androgens can suppress it and that effects on fertility may be irreversible. LH and FSH fell by about 70% in Jatenzo's approval trial, and by 77.5% and 60.1% in a 28-day study of an early version of the capsule. A 2025 review notes the hormones often stay within the normal range, "though data on semen parameters remain limited"; no study has measured sperm counts or pregnancies on modern capsules. The AUA says testosterone should not be prescribed to men trying to conceive, and the US male infertility guideline extends that to men interested in future fertility. See TRT and fertility. [4], [5], [33], [63], [11], [64]
Estrogen. Some testosterone is converted into estradiol, and estradiol rises on capsules much as on other forms. On Kyzatrex it rose from 2.3 to 3.5 ng/dL (23 to 35 pg/mL); in Jatenzo's trial it averaged 32 pg/mL, similar to the skin-solution group (33 pg/mL). No guideline sets a routine estradiol target: the AUA measures it mainly when breast symptoms appear, and the US Department of Veterans Affairs (VA) does not recommend aromatase inhibitors. See estrogen on TRT. [32], [5], [11], [65]
Red blood cells. Capsules do not spare hematocrit. In a network meta-analysis of 29 randomized trials (a statistical pooling of trials that compares several treatments at once), hematocrit rose about 4.3 percentage points more than on placebo with oral undecanoate, 4.0 with enanthate and cypionate injections, 3.0 with gel and 1.6 with undecanoate injections. It rose 3.2 points over 4 months on Tlando. The Jatenzo and Kyzatrex labels ask for checks about every 3 months. See hematocrit on TRT. [66], [54], [4], [6]
What do we actually know about oral testosterone in people?
That the capsules restore testosterone to the normal range in most men is shown by their approval trials. What they do to symptoms, the heart and the prostate over years is much less certain: the modern capsule trials were short, mostly without a placebo, and funded by their makers.

Which studies used the modern capsules?
| Study | Who and what | What it found | What it cannot show |
|---|---|---|---|
| Jatenzo approval trial (open-label controlled trial) | 166 men on Jatenzo vs 56 on a skin solution, 3–4 months | 87% in the normal range; systolic pressure up 3–5 mm Hg; more stomach and gut side effects | Symptoms; long-term outcomes [5] |
| Jatenzo year-long trial and extension (open-label) | Jatenzo vs a gel for a year; 69 men completed 2 years | 84% in range at a year; hematocrit stayed under 48%; HDL −9.8 mg/dL; no significant liver-test changes | Only men who chose to continue; maker-funded [28], [27] |
| Kyzatrex approval trial (single-arm) | 155 men, 6 months | 88% in range; hemoglobin 14.7 → 15.2 g/dL; 14.7% above the lab's upper limit | No comparison group; symptoms and hematocrit not measured [32] |
| Tlando main trial (single-arm) | 95 men, fixed dose, 24 days | 80% in range; prolactin up in 6.3% | Only 24 days [35] |
| Tlando 52-week trial (randomized vs AndroGel 1.62%) | 315 men | 87.4% in range; 43.5% never needed a dose change; HDL fell more than on gel | Open-label; 38% stopped early (32% on gel) [26] |
| Switch study (single-arm) | 41 men moved to Jatenzo from other testosterone (30 had a baseline evaluation) | 12 of 30 (40%) needed a higher dose; higher satisfaction than their previous treatment | Small; one clinic [22], [67] |
What did older trials of the 40 mg capsule find?
- Men with hypogonadism: in a 12-man trial, the capsule improved sexual interest and behavior compared with placebo, though testosterone often stayed below normal; in a 15-man comparison, injections maintained sexual function better, with fewer side effects. [68], [57]
- Older men with borderline levels: in trials of 76, 237 and 322 men, the capsule added lean mass, reduced fat and raised bone density at the highest dose, but did not improve strength, mobility or overall symptom scores. [30], [29], [31], [69]
- Against other forms: a skin patch and long-acting injections each gave better testosterone levels than the capsule. [70], [71]
- Pooled results: a 2023 meta-analysis of 12 mostly older trials found the capsule raised testosterone compared with placebo without a significant increase in adverse effects. [72]
No trial of oral capsules has counted heart attacks, strokes, fractures or deaths. The largest safety trial, TRAVERSE, used a daily gel (full results); whether its results apply to capsules, with their twice-daily peaks and blood-pressure rise, is not known. [73]
How does oral testosterone work?
Once the ester reaches the blood through the lymph, enzymes cut off the undecanoate tail and free testosterone (how absorption works). Testosterone then acts like the body's own hormone. In many tissues it works after being converted to DHT, and some is converted to estradiol. In the blood, about 40% is bound to SHBG (sex hormone-binding globulin), 2% is free and the rest is loosely bound to albumin. [4], [1]
Why it switches off your own production. The brain senses testosterone from any source, so the pituitary lowers its LH and FSH signals and the testicles make less testosterone and fewer sperm. [4], [5]
Why blood pressure rises is not known. The labels do not explain it. In Tlando's blood-pressure study, men whose hematocrit rose most had the largest rises (8.3 mm Hg), but that link does not prove cause. [54], [1]
What are the risks and unanswered questions?
Is oral testosterone safe?
For men with a confirmed diagnosis and regular monitoring, its risks are well described: higher blood pressure, lower HDL cholesterol, more red blood cells, fluid retention, breast enlargement, prostate effects and loss of fertility. It is not known to cause the liver damage of old oral steroids. Long-term heart and prostate safety is uncertain, because no outcome trial has used capsules. [4], [6], [1], [74]
Does oral testosterone raise blood pressure?
Yes, on average, and all three labels warn about it. Each label says the capsules "can increase blood pressure," which "can increase cardiovascular risk over time," asks for periodic blood-pressure checks, especially in men with high blood pressure, and does not recommend them with uncontrolled high blood pressure. [4], [6], [1]
The rises come from separate trials using 24-hour ambulatory blood pressure monitoring, a cuff that measures pressure repeatedly through a day and night:
- Jatenzo: +4.9/2.5 mm Hg at about 4 months (+5.4/3.2 in men treated for high blood pressure), not yet leveled off; 7.2% started or increased blood-pressure medicine. [4]
- Tlando: +4.3/1.4 mm Hg at about 4 months (+4.8/1.6 with high blood pressure); 1.4% started blood-pressure medicine. [1]
- Kyzatrex: +1.7/0.6 mm Hg at 4 months and +1.8/0.6 at 6 months (+3.4 systolic in men on blood-pressure medicine); 3.2% started blood-pressure medicine. [6]
For comparison, the Xyosted autoinjector (testosterone enanthate given subcutaneously, under the skin) raised 24-hour pressure 3.9/1.5 mm Hg after 12 weeks, and in TRAVERSE, systolic pressure rose 1.0 mm Hg on testosterone gel and fell 0.5 mm Hg on placebo by 36 months. [75], [6]
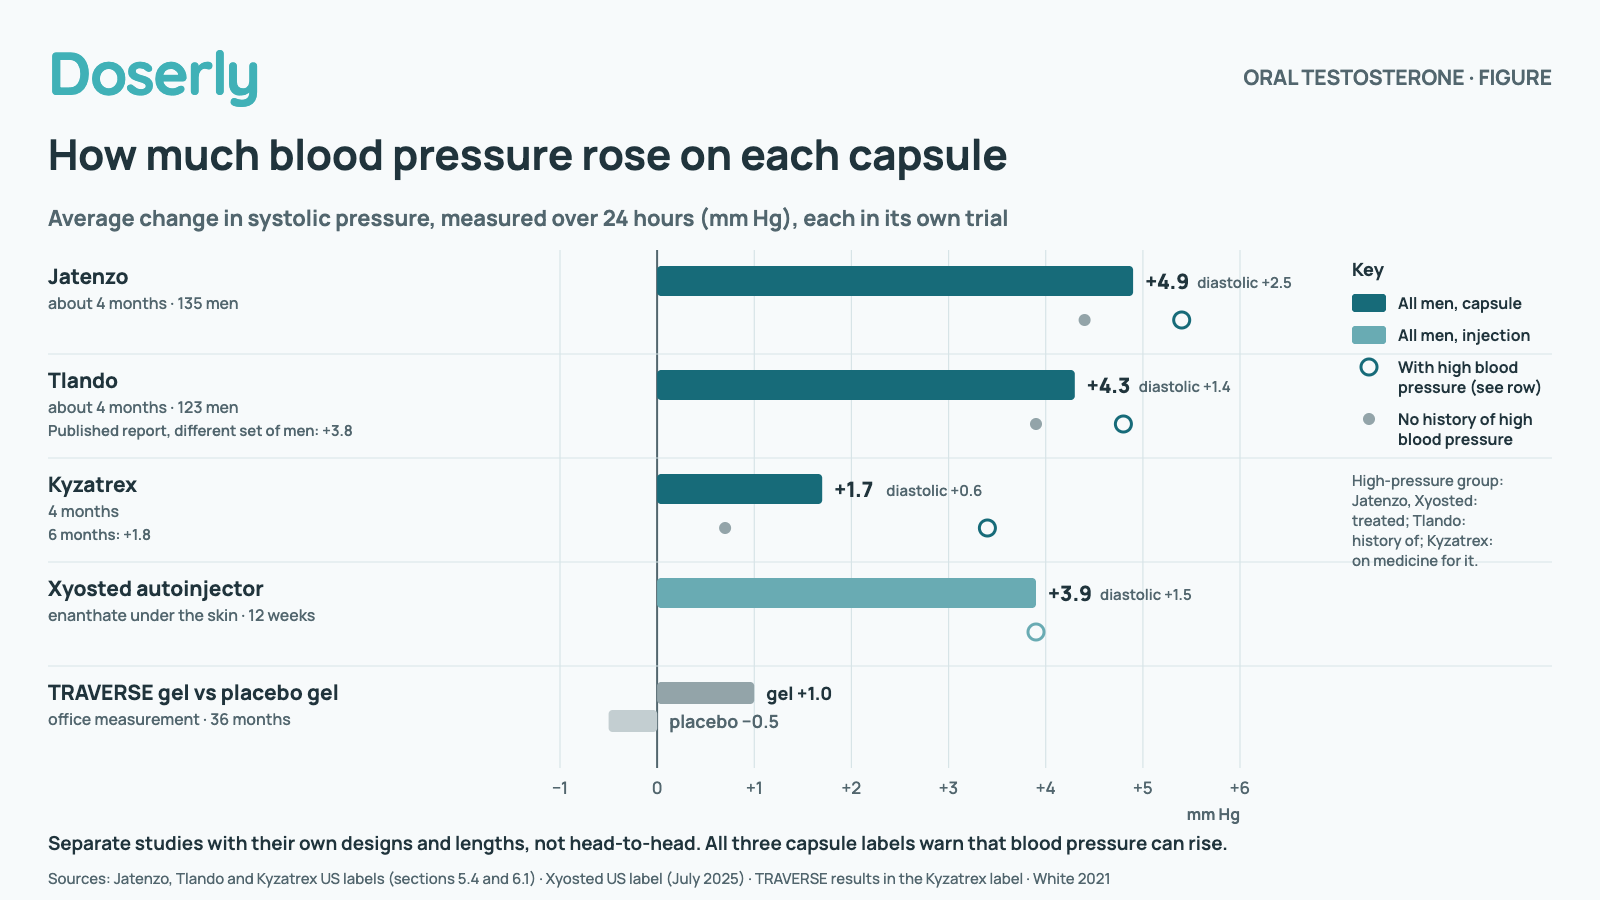
How much blood pressure rose on each capsule
Average change in systolic pressure measured over 24 hours (mm Hg). Bar: all men. Ring: men with high blood pressure. Grey dot: no history of high blood pressure.
- Jatenzo (about 4 months · 135 men)
- All men +4.9 (diastolic +2.5); treated high blood pressure +5.4; no history of high blood pressure +4.4.
- Tlando (about 4 months · 123 men)
- All men +4.3 (diastolic +1.4); history of high blood pressure +4.8; no history of high blood pressure +3.9. Published report, different set of men: +3.8.
- Kyzatrex (4 months)
- All men +1.7 (diastolic +0.6); on blood-pressure medicine +3.4; no history of high blood pressure +0.7. 6 months: +1.8.
- Xyosted autoinjector (enanthate under the skin · 12 weeks)
- All men +3.9 (diastolic +1.5); treated high blood pressure +3.9.
- TRAVERSE gel vs placebo gel (office measurement, 36 months)
- Gel +1.0; placebo −0.5.
Separate studies with their own designs and lengths, not head-to-head. All three capsule labels warn that blood pressure can rise.
Why the boxed warnings went away. All three were approved with a boxed blood-pressure warning. The boxes were removed in labeling approved in July 2025, after FDA's February 2025 class-wide labeling added TRAVERSE results and a blood-pressure warning to every testosterone product. That does not mean FDA now considers the rise unimportant: the warning and trial results remain in each label. Some pain and cold medicines also raise blood pressure, and the labels warn that combining them adds to the rise. [75], [76], [77], [4]
Is oral testosterone bad for your liver?
No liver damage has been linked to modern capsules. The reputation comes from methyltestosterone: in 60 people on long-term treatment, 19 had abnormal liver tests and 33 of 52 abnormal liver scans, and its label warns of hepatitis, jaundice and liver tumors. The AUA and the British Society for Sexual Medicine say alkylated oral testosterone should no longer be prescribed. [78], [10], [11], [21]
Testosterone undecanoate is not alkylated. Its labels say it is "not known to cause" those effects, while still asking patients to report signs such as yellowing skin or eyes (jaundice). No routine liver test is required. The evidence behind that:
- Over 2 years on Jatenzo, liver tests showed no clinically significant changes, and Tlando's main trial reported no liver adverse events. [27], [35]
- In 33 men followed for at least 10 years on the older capsule, liver tests did not change. [56]
- Two 2025 reviews, one by authors who include trial investigators, found no evidence of liver toxicity with the newer formulations. [74], [79]
The VA advises avoiding oral testosterone specifically in men with severe liver disease, because of their already higher risk of blood clots. [65]
Does oral testosterone affect the heart?
The best evidence comes from TRAVERSE, a randomized trial of about 5,200 men aged 45 to 80 with heart disease or high heart risk, given daily testosterone gel or a placebo gel. Among the 2,596 men who used testosterone gel and the 2,602 who used placebo gel, it found:
- Heart attack, stroke or heart death: 182 men (7.0%) on testosterone vs 190 (7.3%) on placebo; hazard ratio 0.96 (1.0 would mean no difference between groups), with a 95% confidence interval of 0.78 to 1.17. The top of that range stayed below the trial's safety margin of 1.5, so a large rise in risk was ruled out. [73], [6]
- Heart rhythm: atrial fibrillation 3.5% vs 2.4%; nonfatal rhythm problems needing treatment 5.2% vs 3.3%. [6]
- Kidneys: acute kidney injury 2.3% vs 1.5%. [6]
- Clots: venous clots 1.7% vs 1.2%, including pulmonary embolism 0.9% vs 0.5%. [4]
- Fractures: 91 of 2,601 men (3.50%) vs 64 of 2,603 (2.46%), counting every randomized man. [80]
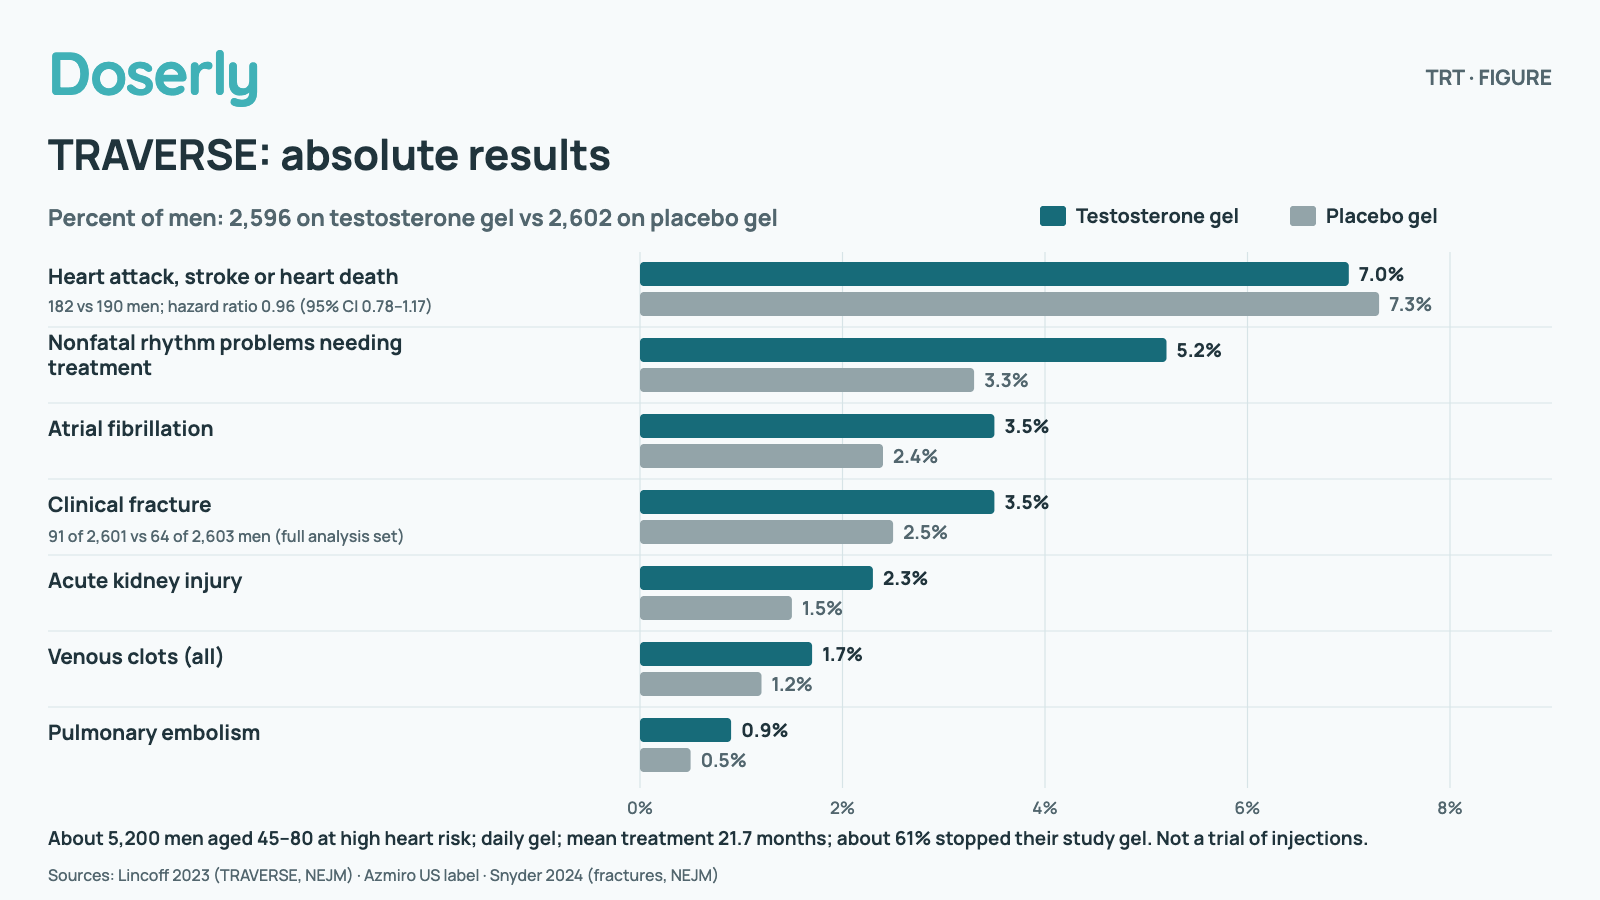
TRAVERSE: absolute results
Testosterone gel (2,596 men)Placebo gel (2,602 men)
- Heart attack, stroke or heart death
- Testosterone 7.0% vs placebo 7.3% (182 vs 190 men; hazard ratio 0.96, 95% CI 0.78–1.17; met the 1.5 safety margin)
- Nonfatal rhythm problems needing treatment
- Testosterone 5.2% vs placebo 3.3%
- Atrial fibrillation
- Testosterone 3.5% vs placebo 2.4%
- Clinical fracture
- Testosterone 3.5% vs placebo 2.5% (91 of 2,601 vs 64 of 2,603 in the full analysis set)
- Acute kidney injury
- Testosterone 2.3% vs placebo 1.5%
- Venous clots (all)
- Testosterone 1.7% vs placebo 1.2%
- Pulmonary embolism
- Testosterone 0.9% vs placebo 0.5%
About 5,200 men aged 45–80 at high heart risk; daily gel; mean treatment 21.7 months; about 61% stopped their study gel. Not a trial of injections.
Its limits matter for capsules. TRAVERSE tested only a gel, the average man used it for 21.7 months, about 61% stopped their study gel early, and it enrolled men at high heart risk. It did not test a medicine that raises blood pressure by several points or lowers HDL as capsules do. A 2025 meta-analysis that pooled 23 trials in 9,280 men, each lasting at least a year, found no increase in death, heart attack or stroke, but about 50% more heart-rhythm problems on testosterone (risk ratio 1.53, 95% confidence interval 1.20 to 1.97: the rate on testosterone was about 1.5 times the rate on placebo). The published summary does not give the absolute rates. [73], [6], [81]
All three oral labels now carry the TRAVERSE results. See TRT and heart health for the full picture. [4], [6], [1]
What side effects do the labels list?
- Jatenzo: across 569 men, reactions in more than 2% were too many red blood cells (polycythemia), diarrhea, indigestion, burping, ankle or leg swelling, nausea, raised hematocrit, headache, prostate enlargement and high blood pressure. In the 4-month trial, headache and raised hematocrit each affected 4.8%; 3 of 166 men (1.8%) stopped because of side effects. [4]
- Kyzatrex: only high blood pressure (2.6%) reached 2% in its 6-month trial; a 12-month study added headache, joint pain, diarrhea, raised hemoglobin, anxiety, constipation, swelling and raised PSA. [6]
- Tlando: high blood pressure (5.1%), raised hematocrit (4.3%) and upper respiratory infection (3.6%) over 4 months; raised prolactin (6.3%) in its 24-day study. [1]
All three carry the class warnings: blood clots, worsening of an enlarged prostate, fluid retention, breast enlargement (gynecomastia), sleep apnea, cholesterol changes and misuse. [4], [6], [1]
What about blood clots, sleep apnea, fluid retention and mood?
- Blood clots. The labels report clots in the legs (deep vein thrombosis) and lungs (pulmonary embolism) after marketing and in TRAVERSE; leg pain, swelling, warmth or redness, or sudden shortness of breath need urgent assessment. [4]
- Sleep apnea. Testosterone may worsen sleep apnea, especially with obesity or lung disease. [4]
- Fluid retention. Swelling, with or without heart failure, can be serious in people with heart, kidney or liver disease. [4]
- Mood. Jatenzo's label reports depression and suicidal thoughts in its trials and asks patients to seek help for new or worsening mood changes, anxiety or suicidal thoughts. [4]
Could oral testosterone affect the prostate?
Testosterone can enlarge the prostate and raise PSA slightly. PSA rose an average of 0.2 ng/mL on Jatenzo, with 1.9% of men meeting the label's threshold for a significant rise; on Kyzatrex it rose 0.15 ng/mL at 6 months, and 2.6% of men rose by more than 1.4 ng/mL. In 23 men given the older capsule for 8 months, prostate volume rose 12% while PSA did not change. The labels contraindicate testosterone in known or suspected prostate cancer. In TRAVERSE, which excluded men with PSA above 3.0 ng/mL, high-grade prostate cancer occurred in 5 of 2,596 men on testosterone (0.19%) vs 3 of 2,602 on placebo (0.12%), a difference that was not significant. [4], [6], [82], [83] See TRT and the prostate.
Is oral testosterone legal? Is it FDA approved?
Checked September 2026. Rules differ by country and change often.
United States. Jatenzo (2019), Tlando (2022) and Kyzatrex (2022) are FDA-approved prescription medicines, and testosterone is a Schedule III controlled substance. The key steps:
- No generic. The Orange Book lists none, with patents listed to 2039 for Jatenzo and 2041 for Kyzatrex. [7]
- 2015. FDA required testosterone labels to say that safety and benefit in "age-related" low testosterone have not been established, and the oral labels still do. [77], [6]
- February 28, 2025, and July 2025. FDA added TRAVERSE results and blood-pressure warnings to testosterone labels, and the oral products' boxed blood-pressure warnings were removed in July 2025. Only Aveed injections and testosterone gels and solutions applied to the skin still carry boxed warnings. [77], [75], [84], [23]
- June 18, 2026. The Department of Health and Human Services (HHS) announced that FDA is requesting label changes: removing the age-related limitation, contraindicating testosterone only in metastatic prostate cancer, and revising the prostate-enlargement warning. These are requests; the Kyzatrex label revised in August 2026 still has the old wording. [85], [6]
- Telehealth. Temporary rules allow prescribing controlled medicines such as testosterone without an in-person visit through December 31, 2026; a permanent Drug Enforcement Administration (DEA) rule is still under review. [86], [87]
- Methyltestosterone. The old alkylated tablet is still marketed, with about 136 Medicare Part D claims in 2024, although the AUA advises against it. [10], [51], [11]
Canada. Testosterone is a Schedule IV controlled substance and prescription-only. Jatenzo is marketed, Kyzatrex is approved but not yet marketed, Tlando is not available, and a generic 40 mg capsule is marketed. [88], [8]
United Kingdom. Testosterone is a Class C controlled drug (Schedule 4 Part II), prescription-only. No oral testosterone undecanoate has current UK product information. [89], [55], [60]
Australia. Testosterone is a Schedule 4 (prescription-only) medicine with extra controls on possession. No oral testosterone undecanoate is among Australia's current testosterone product information documents. [90], [61]
European Union. Rules and products are national. France's oral capsule is no longer in its public medicines database; other member states were not checked for this guide. [62] See TRT in Europe.
A "research use only" label on a product does not make it legal, tested or the same as a licensed medicine.
Is oral testosterone banned in sport? Does it show up on a drug test?
Yes. Testosterone and its esters are on the World Anti-Doping Agency (WADA) Prohibited List in class S1, banned in and out of competition, and the 2027 list keeps that from January 1, 2027. Athletes with a medical need can apply for a therapeutic use exemption, which WADA grants only when low testosterone has an organic cause (such as a testicular or pituitary disorder), not for age, obesity or earlier steroid use. No source gives a detection window for oral capsules, so there is no reliable clearance time to plan around. [91], [92], [93]
Who should be especially cautious?
- Men with high blood pressure or heart disease. The capsules raise blood pressure, most in men already treated for it; they are not recommended with uncontrolled high blood pressure. [4], [6], [1]
- Men who want children now or soon. Testosterone suppresses sperm production; guidelines advise against it for men trying to conceive. [11], [64]
- Men with prostate or breast cancer. Contraindicated on current US labels (known or suspected prostate cancer). [4]
- High hematocrit, past clots or severe liver disease. Guidelines treat a high starting hematocrit as a reason for caution, and the VA advises against oral testosterone in severe liver disease. [14], [65]
- Low HDL or depression. HDL fell about 14% on Jatenzo and Kyzatrex, and Jatenzo's label warns about depression and suicidal thoughts. [5], [32], [4]
- Men over 65. The Jatenzo and Kyzatrex efficacy trials enrolled none, and Jatenzo's label calls long-term heart and prostate data in older men insufficient. [4], [6]
- Women and children. Testosterone is contraindicated in pregnancy and can harm an unborn baby; these guides are for men. Use under 18 is not established and can close growth plates early. [4]
- Drug-tested athletes. Banned at all times. [91]
- People taking other medicines, such as blood thinners, insulin or corticosteroids; see the next question.
Can oral testosterone be taken with other medicines?
The labels list four interactions:
- Insulin and diabetes medicines. Testosterone can lower blood sugar, and the Jatenzo and Kyzatrex labels say this may require a lower dose of diabetes medicine. [4], [6]
- Warfarin and other oral blood thinners. Testosterone can change their effect; the labels advise more frequent blood-clotting tests (INR and prothrombin time), especially when starting and stopping. [4], [1]
- Corticosteroids. Together they can increase fluid retention. [4]
- Medicines that raise blood pressure, including some over-the-counter pain and cold medicines. [4], [1]
Jatenzo at 237 mg had no meaningful effect on three test medicines (midazolam, digoxin and rosuvastatin); the effect of higher doses is unknown. Canada's 40 mg capsule monograph adds that testosterone may increase the kidney toxicity of cyclosporine. Testosterone can also lower thyroxine-binding globulin, which changes total thyroid hormone results without changing thyroid function. Bring a full list of everything you take, including supplements, to a pharmacist or doctor. [4], [9]
Is oral testosterone available, and what does it cost?
Checked September 2026.
In the United States, oral testosterone is far less used than injections: Medicare Part D paid for 7,521 Jatenzo prescriptions and 802 Tlando prescriptions in 2024, against about 1.1 million for generic cypionate. FDA's drug shortage data lists no testosterone shortage (updated September 26, 2026). [51], [94]
There is no single price. As a reference point, US pharmacies paid on average about $17.93 per 237 mg Jatenzo capsule ($8.97 for 158 mg and $8.95 for 198 mg) and $7.17 per 112.5 mg Tlando capsule in September 2026. At the starting doses, that is roughly $1,076 of Jatenzo or $860 of Tlando for 30 days, before markup, insurance or savings programs. Medicare's average gross cost was $1,055 per Jatenzo prescription in 2024. Kyzatrex appears in neither dataset. [50], [51]
For comparison, generic cypionate injections cost Medicare an average of $37.01 per prescription in 2024, and a 2023 review called injectable testosterone "the most cost-effective therapeutic option." In Canada, Ontario's formulary lists the generic 40 mg capsule at CAD 0.5649 per capsule. [51], [24], [59] See the cypionate guide for injection prices.
What people report paying is in the community section.
What should be monitored while using oral testosterone?
The labels ask for testosterone at each product's own time after dosing, blood pressure, hematocrit, PSA and lipids, and for Tlando, prolactin. Numeric hematocrit limits come from guidelines. Use this summary to prepare questions for your prescriber; it is not a personal testing plan. [4], [6], [1]
| Why it matters | What labels and guidelines say | Tracking category |
|---|---|---|
| Testosterone level | Labels: at each product's own time after the morning dose (timing), 7 days after a change (Tlando: 3–4 weeks after starting), then periodically. Endocrine Society: 3–6 months, 12 months, then yearly | Blood work; Libido; Energy Levels |
| Blood pressure | Labels: check periodically, especially with high blood pressure; not for uncontrolled high blood pressure | Blood Pressure |
| Hematocrit | Jatenzo and Kyzatrex: before starting, then about every 3 months. Tlando: every 3 months in year one, then every 6. AUA: intervene at 54% or higher. VA: adjust above 51%, stop above 54%. Society for Endocrinology: adjust above 50% | Blood work |
| Cholesterol | Labels: check the lipid profile periodically, particularly after starting | Blood work |
| PSA and prostate | Labels: evaluate before and during treatment. AUA: PSA before starting in men over 40. Endocrine Society: urology referral if PSA rises by more than 1.4 ng/mL in the first 12 months or exceeds 4.0 ng/mL | Blood work; Urinary Symptoms |
| Prolactin (Tlando only) | Before starting and 3–4 months after; stop if it stays high | Blood work |
| Mood, breasts, sleep | Labels list depression (Jatenzo), breast enlargement and sleep apnea | Mood & Wellbeing; Hormonal Symptoms; Sleep Quality |
| Fertility | Semen analysis only if fertility matters; testosterone suppresses sperm production | Other (semen result) |
[4], [6], [1], [14], [11], [65], [16]
The Canadian Urological Association uses its own hematocrit trigger of 55%. See TRT blood work and hematocrit on TRT. [19]
Write down the timing. For every testosterone result, note the time of the morning capsule, what you ate with it and the time of the draw. On capsules, a result without its timing is hard to interpret. Blood pressure is the other number worth keeping a record of, since all three labels ask for periodic checks.
What do people in public communities report?
Public forums hold every kind of oral testosterone story: men glad to be off needles, men whose levels never rose enough and men who stopped within days. The accounts below come from public Reddit threads from the past year, described without identifying anyone.
What do the positive reports look like?
Better energy, focus and sex drive, usually alongside other changes. A man in his 50s starting at 174 was raised from 200 to 300 mg twice daily of Kyzatrex and after a few months reported a level of 869, clearer thinking, more energy and better workouts, with libido improved but below earlier years; he valued avoiding injections and gel transfer to his family. A man in his 30s on Jatenzo 237 mg twice daily noticed emotional changes after 4–6 weeks, but he also changed his diet and training and credited those with much of his progress. [95], [96]
Capsules also matter to people who cannot use other forms: one man with reactions to injections and pellets said Tlando had helped before, and another person who blamed an injection ingredient for years without relief reported their first improvement on capsules. [97], [98]
Does everyone respond?
No. Several men describe levels that stayed low: around 150–180 after 6 months (that man felt better a month after switching to a compounded cream, while also starting a gym program); 241 after 6–7 months of 200 mg twice daily with fatty meals across two brands; and 267 ng/dL after over 2 months of Jatenzo 237 mg twice daily. Others said early benefit faded, or that 6 months brought little change before a switch to injections. [99], [100], [101], [102], [103]
Some had good levels but little relief: one man's free testosterone was high after 45 days on 300 mg twice daily of an unnamed oral product, yet his libido and erections had not changed. A man on a 40 mg capsule for 45 days felt no better and developed bad acne, and a man with chronic pain said Tlando had not helped. [104], [105], [106]
What does taking it twice a day feel like?
The most distinctive reports are about the two daily peaks:
- A rush a couple of hours after each dose. Several people on 200 mg twice daily describe nervous or restless energy, sometimes with brain fog, about 2 hours after a capsule, easing a few hours later; two switched to injections within about 2 months and felt better. [107], [108], [109]
- Heat and flushing. One person who restarted Kyzatrex at 150 mg twice daily felt hot and flushed a few hours after doses; earlier, 200 mg twice daily had felt too stimulating and 100 mg twice daily did little. [110]
- Wearing off. A man whose level rose from 230 to 1,017 on Kyzatrex 200 mg twice daily later said each dose lasted about 6 hours and his mornings felt poor, and moved to pellets. Another person, also on hCG, described energy swinging at both 400 and 200 mg a day. [111], [112]
What do people say about food, timing and blood tests?
Food is the most common worry: one person whose usual breakfast had 14 g of fat asked how to reach the 30 g a provider mentioned, another wondered whether eggs and avocado were enough, and a Tlando user found keeping meals about 12 hours apart a burden. [113], [114], [115]
Timing explains some confusing results. One person kept gaining strength over a year on Jatenzo, but later results fell to 250 and then 164; they often took both daily capsules together at breakfast, and blood was drawn 2.5–3.5 hours after a capsule, well short of the label's 6 hours. Another took one Tlando capsule after breakfast and one after lunch, following spoken instructions that differed from the label, and after 5 weeks reported a very low level with fatigue and low mood. [116], [117] See when blood should be drawn.
What unwanted effects come up?
- Blood pressure. One person a month into Jatenzo had blurred vision and a reading of 139/98 after never having high blood pressure; an overweight man two weeks in reported an average of 150/93, alongside more energy. [118], [119]
- Anxiety and mood. A man with a history of panic attacks stopped Kyzatrex after 3 days of sharp anxiety. Another developed anxiety and intrusive thoughts after restarting Jatenzo following a month-long gap, with his level lower than before treatment. A Tlando user described paranoia and stress when their free testosterone ran well above range. [120], [121], [115]
- Stomach and other effects. Reports include oily stools in a man also taking enclomiphene; head pressure, an upset stomach and an unpleasant taste within 4 days on Kyzatrex; and weight gain with lower libido on Jatenzo, described by a man's wife. [122], [123], [124]
- Testicles and hormones. One man had testicular pain in weeks 2 and 3; another's LH and FSH were 0.6 at 2 months. [100], [111]
What do people report about getting it and paying for it?
Access is a recurring problem: pharmacies that could not stock Kyzatrex, turns to specialty or online pharmacies, and difficulty outside the United States. Reported costs range from a $0 copay for Tlando and a $77 copay for Jatenzo (later covered by a coupon) to $180 a month in cash for Kyzatrex, or $400 with clinic fees. One insurer required two recent low testosterone results before covering capsules. [125], [126], [127], [128], [129], [95], [130], [131]
Some threads discuss taking capsules once a day or "pulsing" them on top of enclomiphene. Neither is a schedule from a label, guideline or published practice source. [109], [132]
How can you judge an oral testosterone story?
Ask: Which product and dose, taken twice daily as labeled? What was eaten with it? How many hours after the morning capsule was blood drawn? What else changed, such as enclomiphene, hCG, diet or training? What happened a few months later?
These selected discussions show what people experience and the questions research should answer. They are not a survey of all users, a success rate or a substitute for the studies.
How does oral testosterone compare with other testosterone forms?
These are the forms most often weighed against capsules. Status was checked in September 2026.
| Form | What it is | Route and labeled schedule | What stands out | US status |
|---|---|---|---|---|
| Oral testosterone undecanoate (this guide: Jatenzo, Kyzatrex, Tlando) | Capsules absorbed with a meal | Twice daily with food; for example Jatenzo 237 mg to start | No needles or transfer; raises blood pressure, lowers HDL; hematocrit rise like injections | Approved; Schedule III [4], [66] |
| Testosterone cypionate | Ester in oil; half-life about 8 days | Intramuscular, 50–400 mg every 2–4 weeks | Lowest cost per prescription in Medicare data; levels rise and fall across each interval | Approved [133], [51], [15] |
| Testosterone enanthate | Ester in oil; half-life 4 to 5 days; also the Xyosted autoinjector | Xyosted 75 mg weekly, subcutaneous | Xyosted also carries a blood-pressure warning | Approved [75], [15] |
| Testosterone undecanoate injection (Aveed, Nebido) | The same ester, injected into muscle | Aveed: 750 mg at start, at 4 weeks, then every 10 weeks | Few injections; boxed warning for oil cough and allergic reactions | Approved (Aveed) [84] |
| Testosterone gel | Daily gel on the skin | For example AndroGel 1.62%: 40.5 mg each morning | The form used in TRAVERSE; boxed warning about transfer to children and partners | Approved [23] |
| Natesto | Nasal gel | 11 mg (one 5.5 mg spray in each nostril) three times daily | Short-acting, several doses a day | Approved [134] |
| Testosterone pellets (Testopel) | Small pellets implanted subcutaneously (under the skin) near the hip | 150–450 mg every 3–6 months | Hard to adjust once inserted | Approved [135] |
No trial ranks these forms on long-term outcomes. The practical differences are dosing frequency, needles or meals, how much levels swing, blood pressure and hematocrit rises, cost and whether someone else can be exposed. For men who need to keep sperm production, see enclomiphene, clomiphene and hCG. [66], [11]
Common questions about oral testosterone
Is oral testosterone bad for your liver?
Not the modern capsules, as far as the evidence shows. The liver damage linked to "testosterone pills" comes from methyltestosterone, an older alkylated tablet the AUA says should not be prescribed. Jatenzo, Kyzatrex and Tlando contain testosterone undecanoate, which their labels say is not known to cause those effects, and studies of up to 10 years found no significant liver-test changes. The labels still ask you to report yellowing skin or eyes. [10], [11], [4], [27], [56] See liver safety.
Do you have to take oral testosterone with fat? How much?
Take it with an ordinary meal, as every label says. Fasting cut Tlando's total exposure by about 38%, and a 15 g fat breakfast gave 25% less Jatenzo than a 30 g one, while more fat than a normal meal added little. No label sets a gram target; 30 g was Jatenzo's reference breakfast. [1], [4], [32] See how much fat.
Can you take Jatenzo or Kyzatrex once a day?
Only Kyzatrex has a labeled once-daily dose, and it is the lowest step: 100 mg with breakfast. Jatenzo, Tlando and Kyzatrex's other doses are twice daily, because each dose lasts only hours. The label's blood-test band was not built for taking the whole day's amount at once, so change the schedule only with your prescriber. [6], [4], [1] See once a day.
Is Kyzatrex the same as Jatenzo or Tlando? Can I switch?
They contain the same ester but are different products, each with its own strengths, starting dose, blood-test time and blood-pressure data. The Kyzatrex and Tlando labels say they are not substitutable with other oral testosterone undecanoate products, so a switch means starting the new product's own schedule and retesting at its own time. [6], [1], [4] See how they differ.
What should I do if I miss a dose?
The US labels give no missed-dose instruction, so ask your pharmacist or prescriber. Canada's Jatenzo and Kyzatrex information says to skip the missed dose and take the next one at the usual time, and never to take a double dose. If a blood test is due, tell the lab or prescriber about the missed capsule, because it changes the result. [2], [17], [4]
Will oral testosterone affect my fertility?
Assume it lowers sperm production. The capsules lower LH and FSH, the signals the testicles need, by about 70% in Jatenzo's trial, and no study has shown that sperm production is preserved; the labels warn that effects on fertility may be irreversible for some men. Guidelines advise against testosterone for men trying to conceive. [5], [63], [4], [11] See fertility.
Is oral testosterone better than injections?
Neither is better in general. Capsules avoid needles and transfer but need two meals a day, raise blood pressure on their labels and cost far more. No trial has compared them with injections on symptoms or long-term outcomes, and hematocrit rose about as much with capsules (4.3 points) as with injections (4.0) in a meta-analysis. [4], [66], [50] See how the forms compare.
Is Andriol still available?
Mostly no. Andriol was cancelled in Canada in 2018, its UK version was discontinued, and it is not among Australia's current product information documents; it was never approved in the United States. A generic 40 mg capsule of the same type is still marketed in Canada. [8], [60], [61], [14] See Andriol.
Glossary
Plain explanations of the medical, dosing and research terms used in this guide. Underlined terms in the text link here.
- Ambulatory blood pressure monitoring (ABPM)
- A cuff worn for 24 hours that measures blood pressure repeatedly through the day and night. It gives a more reliable average than a single clinic reading.
- Adverse event
- A harmful or unwanted medical event reported after someone used a treatment. A report alone does not prove the treatment caused it.
- Aromatase inhibitor
- A medicine, such as anastrozole, that blocks the enzyme that turns testosterone into estradiol. The VA does not recommend them for men on testosterone.
- Azoospermia
- No sperm at all in a semen sample.
- Bioavailability
- How much of a dose reaches the bloodstream in a usable form. For the older 40 mg oral capsule it is about 7%.
- Chylomicron
- A tiny fat particle made in the gut lining after a meal. It carries dietary fat, and oral testosterone undecanoate, into the lymph vessels.
- Confidence interval
- The range within which the true result probably lies, given the size of the study. A narrow range means a more precise result.
- Controlled substance
- A medicine whose prescribing and possession are restricted by law because it can be misused. Testosterone is Schedule III in the US, Schedule IV in Canada and Class C in the UK.
- Controlled trial
- A study that compares people who receive a treatment with a similar group who do not, often receiving a placebo instead. Randomly assigning people to each group makes the comparison fairer.
- Daily total
- All the amounts taken in one day, added together. For example, 237 mg twice daily is a 474 mg daily total.
- DHT (dihydrotestosterone)
- A stronger hormone the body makes from testosterone. It acts on the prostate, skin and hair. Oral testosterone undecanoate raises it more than other forms do.
- Dose (amount each time)
- The amount given on one occasion. A protocol lists both the dose and how often it is given.
- Ester
- A chemical tail joined to testosterone. The undecanoate tail is a long fatty acid that lets the medicine dissolve in fat and travel through the lymph; the body removes it to free testosterone.
- Estradiol
- The main form of estrogen. In men it is made mostly from testosterone, so it rises when testosterone rises.
- First-pass metabolism
- The breakdown of a swallowed medicine by the liver before it reaches the rest of the body. It is why plain testosterone pills do not work.
- FSH (follicle-stimulating hormone)
- A pituitary hormone that acts on the cells supporting sperm production. Testosterone therapy lowers it.
- Gynecomastia
- Growth of breast tissue in men, often tender at first. It is linked to a higher estrogen-to-testosterone balance.
- Half-life
- The time it takes for the level of a substance in the blood to fall by half. For oral testosterone undecanoate it is about 2 hours. It is not the same as how long an effect lasts.
- Hazard ratio
- A measure comparing how often an event happens over time in two groups. A hazard ratio of 1 means no difference; 0.96 means about 4% lower in the first group.
- HDL cholesterol
- High-density lipoprotein, often called "good" cholesterol. Oral testosterone undecanoate lowers it by roughly 14% on average.
- Hematocrit
- The share of the blood made up of red blood cells. Testosterone raises it, and most guidelines act when it reaches about 54%.
- Hypogonadotropic hypogonadism
- Low testosterone because the brain and pituitary send too little LH and FSH to the testicles. It can be present from birth or start later. Also called secondary hypogonadism.
- Hypogonadism
- Low testosterone caused by a problem in the testicles or in the brain and pituitary signals that control them, confirmed with symptoms and repeated morning blood tests.
- LH (luteinizing hormone)
- A pituitary hormone that tells the testicles to make testosterone. Testosterone therapy switches it off.
- Lymphatic system
- A network of vessels that drains fluid and absorbed fat from the gut and tissues into a large vein near the collarbone, bypassing the liver's first pass.
- Meta-analysis and network meta-analysis
- A meta-analysis combines the results of several studies statistically. A network meta-analysis compares several treatments at once, even ones never tested head to head.
- Methyltestosterone (17-alpha-alkylated androgen)
- An older oral testosterone that is chemically altered to survive the liver. It can cause liver damage, and the AUA says it should not be prescribed. It is not the same as testosterone undecanoate.
- Open-label
- A study in which participants and researchers know who is getting which treatment. It is more open to bias than a blinded trial.
- Oral
- Taken by mouth and swallowed.
- Placebo
- A dummy treatment with no active ingredient, used as a comparison in studies.
- Primary hypogonadism
- Low testosterone because the testicles themselves do not work well, even though the pituitary sends plenty of LH and FSH.
- Prolactin
- A pituitary hormone. A high level can lower sex drive and needs checking; Tlando's label asks for a prolactin test before and after starting.
- PSA (prostate-specific antigen)
- A blood test for a protein made by the prostate. It rises slightly on testosterone and is used to decide whether prostate checks are needed.
- Risk ratio
- The rate of an event in one group divided by the rate in another. A risk ratio of 1 means no difference; 1.5 means the event was about 1.5 times as common in the first group.
- SHBG (sex hormone-binding globulin)
- A blood protein that carries testosterone. Oral testosterone undecanoate lowers it, which changes how much testosterone is free.
- Titration
- Adjusting a dose in steps, usually based on blood tests and symptoms.
- TRT (testosterone replacement therapy)
- Prescribed testosterone, by injection, gel, capsule or other forms, for men with low testosterone. It switches off the brain's LH and FSH signals.
- WADA
- The World Anti-Doping Agency, which publishes the list of substances banned in sport. Testosterone is banned at all times.
How this guide was researched
This guide is built from a thorough review of the sources cited throughout it: product labels and regulatory records from the United States, Canada and Europe, clinical guidelines from the United States, Canada, the United Kingdom, Europe and Australia, published clinical trials and studies, FDA approval letters and review documents, and official drug-cost data. We also reviewed public online forums where people describe their own experiences with oral testosterone.
The guide cites 135 sources, including 14 product labels and product information documents, 10 guidelines and position statements, and 32 original studies in people, plus 38 public community threads. Each type of source answers a different question. Labels, guidelines and trials show what was approved and measured. Practice papers show how prescribers typically use it. Personal accounts show what individual people experienced. Every numbered citation links to its entry below, labeled by source type.
How this guide was made
Research and drafting were AI-assisted. Every cited source was checked against the original, and the guide was reviewed and edited by Doserly before publication. It has not had an independent clinical review, and Doserly does not currently have medical reviewers. Doserly makes a medication and health-tracking app and runs Doserly Academy, both of which are promoted in this guide. Read our editorial policy for how guides are researched, updated and corrected.
This guide is for educational purposes. It summarizes what the reviewed sources report so the research is easier to understand; it is not medical advice. For a deeper dive, or to check any point for yourself, go straight to the cited sources.
Explore the sources
These are the documents cited in this guide. Labels, guidelines, studies and personal accounts answer different questions. A source being listed does not mean every statement on its page is endorsed.
Showing 135 sources
- 01
TLANDO (testosterone undecanoate) capsules, for oral use, CIII ↗
Product label (US)
Full label reviewed.
Detail: fixed 225 mg (two 112.5 mg capsules) twice daily with food; serum testosterone 8–9 hours after the morning dose at 3–4 weeks, continue at 300–1,080 ng/dL; median time to peak about 5 hours; ester half-life about 2 hours; prolactin monitoring.
- 02
JATENZO (testosterone undecanoate capsules): Product Monograph (Canada) ↗
Product monograph (Canada)
Full monograph reviewed.
Detail: Same dosing as the US label; swallow without chewing; if a dose is missed, skip it and take the next scheduled dose; absorption through the lymph "partially circumventing" first-pass liver inactivation; avoid refrigeration.
- 03
Plasma androgen levels in men after oral administration of testosterone or testosterone undecanoate ↗
Human report
Original abstract reviewed.
Detail: Swallowed plain testosterone had no effect on blood androgens; testosterone undecanoate raised them markedly.
- 04
JATENZO (testosterone undecanoate) capsules, for oral use, CIII ↗
Product label (US)
Full label reviewed.
Detail: 237 mg twice daily with food to start (158–396 mg); serum testosterone 6 hours after the morning dose, no change at 425–970 ng/dL; 24-hour blood pressure +4.9/2.5 mm Hg at 4 months; 15 g fat breakfast gave 25% less exposure than 30 g; store at 20–25 °C.
- 05
A New Oral Testosterone Undecanoate Formulation Restores Testosterone to Normal Concentrations in Hypogonadal Men ↗
Human trial (open-label, controlled)
Original full text reviewed.
Detail: 166 men on Jatenzo vs 56 on a skin solution for 3–4 months; 72% moved to a higher dose; LH and FSH fell about 70%; HDL fell 13.9%; systolic pressure rose 3–5 mm Hg; "minty burps" from peppermint oil.
- 06
KYZATREX (testosterone undecanoate) capsules, for oral use, CIII ↗
Product label (US)
Full label reviewed.
Detail: 200 mg twice daily with food to start (100 mg once daily to 400 mg twice daily); serum testosterone 3–5 hours after the morning dose, no change at 460–971 ng/dL; not substitutable with other oral products; 24-hour blood pressure +1.7/0.6 mm Hg at 4 months; carries the TRAVERSE results.
- 07
Orange Book: Approved Drug Products with Therapeutic Equivalence Evaluations (testosterone undecanoate, oral) ↗
FDA product listing
Structured data reviewed.
Detail: Jatenzo approved March 27, 2019; Tlando March 28, 2022; Kyzatrex July 27, 2022; Kyzatrex 100 mg listed as discontinued; no generic oral testosterone undecanoate; patents listed to 2039 (Jatenzo) and 2041 (Kyzatrex).
- 08
Health Canada Drug Product Database: testosterone products and status history ↗
Regulator database (Canada)
Structured data reviewed.
Detail: Jatenzo marketed since April 24, 2026; Kyzatrex approved June 30 and July 2, 2026, not marketed; Taro oral 40 mg marketed; Andriol cancelled January 29, 2018; another oral generic dormant since August 1, 2025; no Tlando.
- 09
Taro-Testosterone (testosterone undecanoate) 40 mg capsules: Product Monograph (Canada) ↗
Product monograph (Canada)
Full monograph reviewed.
Detail: 120–160 mg a day in two doses for 2–3 weeks, then 40–120 mg a day, with a meal; bioavailability about 7%; peak 4–5 hours after a dose, back to baseline after about 10 hours; store at 15–30 °C, do not refrigerate.
- 10
Methyltestosterone capsules USP, 10 mg, CIII ↗
Product label (US)
Full label reviewed.
Detail: Warns that 17-alpha-alkylated androgens cause cholestatic hepatitis and jaundice at relatively low doses, and that prolonged high doses are linked to peliosis hepatis and liver tumors.
- 11
Evaluation and Management of Testosterone Deficiency: AUA Guideline ↗
Clinical practice guideline
Original full text reviewed.
Detail: "Clinicians should not prescribe alkylated oral testosterone"; no testosterone for men trying to conceive; intervene at hematocrit 54% or higher; PSA before starting in men over 40.
- 12
21 CFR 1308.13 Schedule III (anabolic steroids) ↗
Regulation (US)
Original page reviewed.
Detail: Anabolic steroids, including testosterone and its esters, are Schedule III.
- 13
An oral lipidic native testosterone formulation that is absorbed independent of food ↗
Human report
Original abstract reviewed.
Detail: An investigational oral form of plain testosterone; "There is no licensed oral native testosterone."
- 14
Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline ↗
Clinical practice guideline
Original full text reviewed.
Detail: Lists oral testosterone undecanoate 40–80 mg two or three times daily with meals among formulations not approved by the FDA, with variable responses and a high DHT:T ratio; measure 3–5 hours after a fat-containing meal; stop if hematocrit is above 54%.
- 15
EAU Guidelines on Sexual and Reproductive Health, Chapter 3: Male Hypogonadism ↗
Clinical practice guideline
Original full text reviewed.
Detail: Lists self-emulsifying oral testosterone undecanoate at 100–237 mg twice daily with gastrointestinal effects and a blood-pressure rise; its text still refers to a boxed warning that FDA removed in July 2025.
- 16
Society for Endocrinology guidelines for testosterone replacement therapy in male hypogonadism ↗
Clinical practice guideline
Original full text reviewed.
Detail: Oral testosterone undecanoate 40–120 mg two or three times daily with meals, swallowed without chewing; "not a preferred treatment option"; expects lifelong treatment for a confirmed diagnosis.
- 17
KYZATREX (testosterone undecanoate capsules): Product Monograph (Canada) ↗
Product monograph (Canada)
Full monograph reviewed.
Detail: At day 90, 43.8% of trial participants were on 600 mg a day and 8.3% had been reduced to 200 or 100 mg a day; take with a meal, swallow without chewing; missed dose: take the next dose at the scheduled time, never double.
- 18
Restandol Testocaps 40 mg soft capsules: Summary of Product Characteristics (Ireland) ↗
Product information (Ireland, historical)
Full product information reviewed.
Detail: 120–160 mg a day for 2–3 weeks, then 40–120 mg a day, with a meal and swallowed whole; peak about 40 nmol/L 4–5 hours after a dose, raised for at least 8 hours; first authorised November 24, 1978.
- 19
Canadian Urological Association guideline on testosterone deficiency in men: Evidence-based Q&A ↗
Clinical practice guideline
Original full text reviewed.
Detail: Andriol 40 mg: initial 120–160 mg a day in two doses; changes in libido, energy and sexual function expected after 3 months or longer; no taper needed; hematocrit trigger 55%.
- 20
Endocrine Society of Australia position statement on male hypogonadism (part 2): treatment and therapeutic considerations ↗
Position statement
Original full text reviewed.
Detail: Andriol 40 mg two or three times a day; blood test after 2 weeks; trough sampling "not feasible" with oral testosterone because of its "capricious pharmacokinetics."
- 21
The British Society for Sexual Medicine Guidelines on Male Adult Testosterone Deficiency, with Statements for Practice ↗
Clinical practice guideline
Original full text reviewed.
Detail: Oral therapies "rarely used in the UK"; normal testosterone "for only up to 3–5 hours"; alkylated oral forms "should no longer be prescribed."
- 22
Patient Satisfaction with Oral Testosterone Undecanoate in Men Who Received Prior Testosterone Therapy: An Open-Label, Single-Center Clinical Trial ↗
Clinic protocol source (open-label trial)
Original full text reviewed.
Detail: Jatenzo 237 mg twice daily, raised to 316 mg in 12 of 30 men at 1 month; draws 4–6 hours after a dose; 66.7% in the target range at 3 months and 76.0% at 6 months; referral for phlebotomy above hematocrit 52%.
- 23
ANDROGEL (testosterone gel) 1.62%, CIII ↗
Product label (US)
Full label reviewed.
Detail: 40.5 mg each morning; boxed warning about secondary exposure of children and others to testosterone.
- 24
Safety Aspects and Rational Use of Testosterone Undecanoate in the Treatment of Testosterone Deficiency: Clinical Insights ↗
Review
Original abstract reviewed.
Detail: "Injectable TT remains the most cost-effective therapeutic option and is appropriate for most patients as an initial therapy."
- 25
Effect of Testosterone Replacement Therapy on Sexual Function and Hypogonadal Symptoms in Men with Hypogonadism ↗
Human trial (TRAVERSE substudy)
Original abstract reviewed.
Detail: 1,161 men with low libido (587 on testosterone gel, 574 on placebo gel); about 0.5 more sexual acts per day at 6 and 12 months (0.49 and 0.47); desire and hypogonadal symptoms improved, erectile function did not.
- 26
Oral testosterone undecanoate (Tlando) with dose titration versus 1.62% topical testosterone gel: a 52-week randomized trial ↗
Human trial (randomized, open-label)
Original full text reviewed.
Detail: 315 men randomized 2:1; 87.4% in range; 43.5% never titrated; early discontinuation 38% vs 32%; HDL −0.15 vs −0.05 mmol/L; nominally better mental-health and mood scores than gel.
- 27
Two-Year Analysis of a New Oral Testosterone Undecanoate (TU) Formulation in Hypogonadal Men: Efficacy, Impact on Psychosexual Function, and Safety ↗
Human report (open-label extension)
Original abstract reviewed.
Detail: 69 men completed 24 months; hematocrit stayed below 48%; systolic pressure rose 3–6 mm Hg; HDL fell 9.8 mg/dL; no clinically significant liver-test changes. Sponsor-funded.
- 28
A new oral testosterone undecanoate therapy comes of age for the treatment of hypogonadal men ↗
Human trials summary
Original abstract reviewed.
Detail: In a year-long trial against gel, 84% reached the normal range; lean mass +3.2 kg and fat −2.4 kg; hip and spine bone density rose slightly; more mild stomach and gut effects than gel.
- 29
Effect of testosterone supplementation on functional mobility, cognition, and other parameters in older men: a randomized controlled trial ↗
Human trial (randomized, placebo-controlled)
Original abstract reviewed.
Detail: 237 older men with low-normal testosterone, 80 mg twice daily for 6 months; lean mass up and fat down without gains in mobility or strength.
- 30
Oral testosterone supplementation increases muscle and decreases fat mass in healthy elderly males with low-normal gonadal status ↗
Human trial (randomized, placebo-controlled)
Original abstract reviewed.
Detail: 76 men aged 60 or older, 80 mg twice daily for 1 year; lean mass up, fat down, no change in strength; HDL −0.1 mmol/L.
- 31
Oral testosterone replacement in symptomatic late-onset hypogonadism: effects on rating scales and general safety in a randomized, placebo-controlled study ↗
Human trial (randomized, placebo-controlled)
Original abstract reviewed.
Detail: 322 men, 80, 160 or 240 mg a day for 12 months; total symptom score no better than placebo except the sexual domain at 160 mg a day.
- 32
A phase III, single-arm, 6-month trial of a wide-dose range oral testosterone undecanoate product (Kyzatrex) ↗
Human trial (single-arm)
Original full text reviewed.
Detail: 155 men at 19 US sites; 87.8% (worst case) and 96.1% of 90-day completers in range; DHT 21% of testosterone at day 90; estradiol 2.3 to 3.5 ng/dL; HDL −14.0%; body weight and diabetes predicted a higher final dose.
- 33
Reexamination of pharmacokinetics of oral testosterone undecanoate in hypogonadal men with a new self-emulsifying formulation ↗
Human report
Original full text reviewed.
Detail: Trough testosterone steady by day 7; DHT-to-testosterone ratio up threefold; LH −77.5% and FSH −60.1% at 28 days; SHBG 22.2 to 13.3 nmol/L; HDL −19.1%.
- 34
Other action letters: Tlando (NDA 208088) ↗
FDA action letters
Full letters reviewed.
Detail: Complete response letters of June 28, 2016, May 8, 2018 ("clinically meaningful increases in blood pressure") and November 8, 2019 (peak level at or below 1,500 ng/dL in 74% against an 85% target); tentative approval December 8, 2020.
- 35
A new oral testosterone (TLANDO) treatment regimen without dose titration requirement for male hypogonadism ↗
Human trial (single-arm)
Original full text reviewed.
Detail: 95 men on a fixed 225 mg twice daily for 24 days; 80% (95% CI 72–88%) in range; no hepatic adverse events.
- 36
Accurate measurement of androgen after androgen esters: problems created by ex vivo esterase effects and LC-MS/MS interference ↗
Human laboratory study
Original full text reviewed.
Detail: Sodium fluoride tubes read testosterone 15–30% lower after oral undecanoate; the difference was judged to have limited clinical impact.
- 37
Dietary fat modulates the testosterone pharmacokinetics of a new self-emulsifying formulation of oral testosterone undecanoate in hypogonadal men ↗
Human report (crossover)
Original full text reviewed.
Detail: 16 men; 20% and 50% fat meals no different from 30%; fasting gave 50% or less of the exposure.
- 38
The effect of food composition on serum testosterone levels after oral administration of Andriol Testocaps ↗
Human report (crossover)
Original full text reviewed.
Detail: 24 postmenopausal women; exposure 30.7 nmol·h/L with 0.6 g fat, 146 with 19 g and little more with 44 g.
- 39
Recovery of male reproductive endocrine function after ceasing prolonged testosterone undecanoate injections ↗
Human trial follow-up (T4DM)
Original abstract reviewed.
Detail: After 2 years of undecanoate injections, LH and FSH recovered slowly over 12 months, and full recovery may take longer.
- 40
Rate, extent, and modifiers of spermatogenic recovery after hormonal male contraception: an integrated analysis ↗
Pooled analysis of human studies
Original abstract reviewed.
Detail: 1,549 healthy men; sperm returned to 20 million per mL in 67% by 6 months, 90% by 12 and 100% by 24.
- 41
Contribution of lymphatically transported testosterone undecanoate to the systemic exposure of testosterone after oral administration of two Andriol formulations in conscious lymph duct-cannulated dogs ↗
Animal study (dogs)
Original abstract reviewed.
Detail: Lymph carried 91.5–99.7% of the absorbed ester, and about 84% of the testosterone reaching the blood came from it.
- 42
Absolute bioavailability of testosterone after oral administration of testosterone-undecanoate and testosterone ↗
Human report
Original abstract reviewed.
Detail: Absolute testosterone bioavailability 6.83% after oral testosterone undecanoate.
- 43
Steady-state pharmacokinetics of oral testosterone undecanoate with concomitant inhibition of 5alpha-reductase by finasteride ↗
Human trial
Original abstract reviewed.
Detail: 11 men; finasteride 0.5–1 mg twice daily had no significant effect on testosterone or DHT.
- 44
A new oral testosterone undecanoate formulation ↗
Review
Original abstract reviewed.
Detail: Andriol Testocaps moved from oleic acid to castor oil and propylene glycol laurate, stable at room temperature for about 3 years.
- 45
NDA approval letter: Jatenzo (NDA 206089) ↗
FDA approval letter
Full letter reviewed.
Detail: Application dated January 2, 2014; resubmitted after the March 22, 2018 action letter; requires a one-year trial of adrenal function.
- 46
Clinical review: Jatenzo (testosterone undecanoate) oral capsules, NDA 206089 ↗
FDA review document
Relevant sections reviewed (regulatory history, advisory committees, adrenal findings).
Detail: Advisory committee votes of 4 yes, 17 no and 9 yes, 10 no (January 9, 2018); the 2018 action letter cited "a clinically meaningful mean increase in blood pressure"; adrenal atrophy in some dog studies.
- 47
NDA approval letter: Kyzatrex (NDA 213953) ↗
FDA approval letter
Full letter reviewed.
Detail: Application received December 31, 2020; complete response to the October 22, 2021 action letter; 24-month shelf life; not referred to an advisory committee.
- 48
Orange Book cumulative supplement, August 2026: new approvals ↗
FDA product listing
Original document reviewed.
Detail: Kyzatrex 50 mg capsule approved August 25, 2026.
- 49
Effects of the oral testosterone undecanoate Kyzatrex on ambulatory blood pressure in hypogonadal men ↗
Human report (single-arm)
Original full text reviewed.
Detail: 24-hour systolic pressure +1.7 mm Hg at day 120 and +1.8 at day 180; 3.4 vs 0.7 mm Hg with and without blood-pressure treatment; no link with testosterone or hemoglobin levels.
- 50
National Average Drug Acquisition Cost (NADAC), 2026: Jatenzo and Tlando ↗
Government pricing data (US)
Structured data reviewed.
Detail: Per capsule: Jatenzo 158 mg $8.97, 198 mg $8.95, 237 mg $17.93; Tlando 112.5 mg $7.17. No Kyzatrex rows. Acquisition cost, not a retail price.
- 51
Medicare Part D Spending by Drug, data year 2024 ↗
Government spending data (US)
Structured data reviewed.
Detail: Jatenzo 7,521 claims ($1,055 per claim before rebates); Tlando 802 claims; no Kyzatrex rows; generic cypionate 1,118,253 claims ($37.01 per claim); methyltestosterone about 136 claims.
- 52
Treatment of Symptomatic Male Hypogonadism with New Oral Testosterone Therapies: A Comparative Review of Jatenzo, Tlando, and Kyzatrex ↗
Review
Original abstract reviewed.
Detail: 80–88% in range across products; shared risks of hypertension, polycythemia and lipid changes; Kyzatrex offers "self-pay access."
- 53
NDA approval letter: Tlando (NDA 208088) ↗
FDA approval letter
Full letter reviewed.
Detail: Follows the December 8, 2020 tentative approval; 48-month shelf life; pediatric study due 2029.
- 54
Effects of a Novel Oral Testosterone Undecanoate on Ambulatory Blood Pressure in Hypogonadal Men ↗
Human report (single-arm)
Original abstract reviewed.
Detail: Tlando 225 mg twice daily for about 4 months; 24-hour systolic pressure +3.8 mm Hg; hematocrit +3.2 points; largest rises (8.3 mm Hg) in men whose hematocrit rose most.
- 55
Electronic Medicines Compendium (UK) search: testosterone undecanoate ↗
Product information listing (UK)
Search results reviewed.
Detail: Only injection products (Nebido, Roxadin and generics) are listed; no oral capsule.
- 56
A ten-year safety study of the oral androgen testosterone undecanoate ↗
Human report (long-term series)
Original abstract reviewed.
Detail: 33 of 35 men followed for at least 10 years; no change in liver tests; testosterone 5.4–6.5 nmol/L after a dose (normal 8–24).
- 57
Randomized clinical trial of testosterone replacement therapy in hypogonadal men ↗
Human trial (crossover)
Original abstract reviewed.
Detail: 15 men; oral undecanoate gave the most variable levels; sexual function better maintained and fewer side effects with injections.
- 58
European Academy of Andrology guidelines on investigation, treatment and monitoring of functional hypogonadism in males ↗
Clinical practice guideline
Original full text reviewed.
Detail: "Oral T undecanoate (TU) is no longer considered a viable therapeutic option, since its absorption is unpredictable and highly dependent on food intake."
- 59
Ontario Drug Benefit Formulary: testosterone undecanoate 40 mg capsule ↗
Public drug formulary (Canada)
Original page reviewed.
Detail: Taro-Testosterone CAD 0.5649 per capsule; Andriol "Not a Benefit".
- 60
Hertfordshire and West Essex NHS formulary, section 6.4.2: male sex hormones ↗
Local formulary (UK)
Original page reviewed.
Detail: "MSD have discontinued Restandol 40mg capsules from the UK market."
- 61
Therapeutic Goods Administration product information: current testosterone products ↗
Product information listing (Australia)
Current product information documents reviewed.
Detail: Current documents cover undecanoate injections, enanthate, Sustanon 250, gels and a cream; no oral testosterone undecanoate.
- 62
Base de données publique des médicaments: PANTESTONE 40 mg record ↗
Regulator database (France)
Structured data reviewed.
Detail: The oral testosterone undecanoate record returns "Le médicament demandé n'existe pas" (no longer in the database).
- 63
Preserving spermatogenesis in testosterone deficiency: innovations in replacement and stimulatory therapies ↗
Review
Original full text reviewed.
Detail: On oral undecanoate, LH and FSH are reduced but often within range, "though data on semen parameters remain limited."
- 64
Diagnosis and Treatment of Infertility in Men: AUA/ASRM Guideline ↗
Clinical practice guideline
Original full text reviewed.
Detail: Statement 42: do not prescribe testosterone to men interested in current or future fertility.
- 65
Evaluation for and Management of Males with Low Testosterone: Recommendations for Use ↗
Health-system clinical recommendations
Original full text reviewed.
Detail: Oral testosterone "should be specifically avoided" in severe liver disease; adjust above hematocrit 51%, stop above 54%; aromatase inhibitors not generally recommended.
- 66
The Effect of Route of Testosterone on Changes in Hematocrit: A Systematic Review and Bayesian Network Meta-Analysis of Randomized Trials ↗
Meta-analysis of randomized trials
Original abstract reviewed.
Detail: Hematocrit rise vs placebo: oral undecanoate 4.3 points, enanthate or cypionate injections 4.0, gel 3.0, undecanoate injections 1.6.
- 67
Patient Satisfaction After Switching to Jatenzo (Oral Testosterone Undecanoate): Update on an Open-label, Single-arm Clinical Trial ↗
Human report (interim)
Original abstract reviewed.
Detail: Greater satisfaction than with previous testosterone forms and similar symptom improvement.
- 68
Androgen replacement with oral testosterone undecanoate in hypogonadal men: a double blind controlled study ↗
Human trial (crossover, placebo-controlled)
Original abstract reviewed.
Detail: 12 men; sexual interest and behavior improved; testosterone often did not reach the normal range.
- 69
Effects of oral testosterone undecanoate therapy on bone mineral density and body composition in 322 aging men with symptomatic testosterone deficiency ↗
Human trial (randomized, placebo-controlled)
Original abstract reviewed.
Detail: Bone density rose at the spine and hip at 240 mg a day, with a clear dose response.
- 70
Comparison of oral versus transdermal testosterone supplementation in hypogonadal men ↗
Human trial (crossover)
Original abstract reviewed.
Detail: 44 men; a patch gave higher testosterone than oral undecanoate 80 mg twice daily (4.64 vs 2.58 ng/mL).
- 71
Efficacy and safety of two different testosterone undecanoate formulations in hypogonadal men with metabolic syndrome ↗
Human trial
Original abstract reviewed.
Detail: 52 men; injected undecanoate reached target levels more effectively than oral 160 mg a day.
- 72
Oral testosterone therapy: past, present, and future ↗
Review with meta-analysis
Original abstract reviewed.
Detail: 12 trials; testosterone rose vs placebo in men with hypogonadism; no significant increase in adverse effects; oral prescriptions have declined.
- 73
Cardiovascular Safety of Testosterone-Replacement Therapy (TRAVERSE) ↗
Human trial (randomized, placebo-controlled)
Original abstract reviewed.
Detail: About 5,200 men on testosterone gel or placebo gel; heart attack, stroke or heart death 7.0% vs 7.3% (hazard ratio 0.96, 95% CI 0.78–1.17).
- 74
Newer formulations of oral testosterone undecanoate: development and liver side effects ↗
Review
Original abstract reviewed.
Detail: No clinically significant liver toxicity in trials of the newer formulations; authors include trial investigators.
- 75
XYOSTED (testosterone enanthate) injection, for subcutaneous use: prescribing information (NDA 209863 S-020) ↗
Product label (US)
Full label reviewed.
Detail: Boxed blood-pressure warning removed in labeling approved July 11, 2025, as for Jatenzo, Tlando and Kyzatrex; 24-hour blood pressure +3.9/1.5 mm Hg after 12 weeks; 75 mg weekly, subcutaneous.
- 76
openFDA Drugs@FDA records for NDA 206089 (Jatenzo), 208088 (Tlando) and 213953 (Kyzatrex) ↗
FDA application records
Structured data reviewed.
Detail: Labeling supplements for all three products approved July 11, 2025; current holders Tolmar, Verity and Marius; Kyzatrex 100 mg marked discontinued.
- 77
FDA issues class-wide labeling changes for testosterone products ↗
Regulator statement (US)
Original page reviewed.
Detail: Adds TRAVERSE results and blood-pressure warnings to all testosterone labels, removes boxed-warning language about heart outcomes and keeps the age-related limitation first required in 2015.
- 78
Liver damage from long-term methyltestosterone ↗
Human report
Original abstract reviewed.
Detail: 60 people on methyltestosterone 50 mg three times daily; 19 had abnormal liver tests and 33 of 52 abnormal liver scans.
- 79
Testosterone deficiency and treatments: common misconceptions and practical guidance for patient care ↗
Review
Original abstract reviewed.
Detail: No evidence that the newer oral formulations cause liver toxicity.
- 80
Testosterone Treatment and Fractures in Men with Hypogonadism ↗
Human trial (TRAVERSE substudy)
Original abstract reviewed.
Detail: Clinical fractures 91 of 2,601 on testosterone vs 64 of 2,603 on placebo.
- 81
Long-Term Cardiovascular Safety of Testosterone-Replacement Therapy in Middle-Aged and Older Men: A Meta-analysis of Randomized Controlled Trials ↗
Meta-analysis of randomized trials
Original abstract reviewed.
Detail: 23 trials, 9,280 men, at least a year; no increase in death, heart attack or stroke; heart-rhythm problems risk ratio 1.53 (95% CI 1.20–1.97); absolute rates not given in the abstract.
- 82
Effect of long-term oral testosterone undecanoate treatment on prostate volume and serum prostate-specific antigen concentration in eugonadal middle-aged men ↗
Human trial
Original abstract reviewed.
Detail: 23 men for 8 months; prostate volume +12%; PSA unchanged.
- 83
Prostate Safety Events During Testosterone Replacement Therapy in Men With Hypogonadism: A Randomized Clinical Trial ↗
Human trial (TRAVERSE substudy)
Original full text reviewed.
Detail: High-grade prostate cancer in 5 of 2,596 on testosterone vs 3 of 2,602 on placebo; men with PSA above 3.0 ng/mL excluded.
- 84
AVEED (testosterone undecanoate) injection, for intramuscular use, CIII ↗
Product label (US)
Full label reviewed.
Detail: 750 mg at start, at 4 weeks, then every 10 weeks; boxed warning for oil microembolism and allergic reactions with 30 minutes' observation.
- 85
HHS Announces Requested Updates to Testosterone Therapy Product Labels ↗
Regulator announcement (US)
Original page reviewed.
Detail: FDA is requesting removal of the age-related limitation, a contraindication only in metastatic prostate cancer and a revised prostate-enlargement warning. Requested, not yet in labels (checked September 2026).
- 86
Fourth Temporary Extension of COVID-19 Telemedicine Flexibilities for Prescription of Controlled Medications ↗
Regulation (US)
Original notice reviewed.
Detail: Telemedicine prescribing of controlled medicines without a prior in-person visit allowed through December 31, 2026.
- 87
OIRA review record: Special Registrations for Telemedicine (RIN 1117-AB40), final rule ↗
Regulatory review record (US)
Original record reviewed.
Detail: The final special-registration rule is under review, not yet published (checked September 2026).
- 88
Controlled Drugs and Substances Act (S.C. 1996, c. 19), Schedule IV ↗
Legislation (Canada)
Original text reviewed.
Detail: Anabolic steroids, including testosterone, are in Schedule IV.
- 89
Misuse of Drugs Act 1971, Schedule 2 Part III (Class C drugs) ↗
Legislation (UK)
Original text reviewed.
Detail: Testosterone is a Class C drug and is in Schedule 4 Part II of the Misuse of Drugs Regulations 2001.
- 90
Therapeutic Goods (Poisons Standard—June 2026) Instrument 2026 ↗
Legislation (Australia)
Original text reviewed.
Detail: Testosterone is Schedule 4 (prescription-only medicine) with Appendix D controls on possession.
- 91
World Anti-Doping Code International Standard: Prohibited List 2026 ↗
Anti-doping rules
Original document reviewed.
Detail: Testosterone prohibited at all times (S1.1).
- 92
World Anti-Doping Code International Standard: Prohibited List 2027 ↗
Anti-doping rules
Original document reviewed.
Detail: Keeps testosterone prohibited at all times.
- 93
TUE Physician Guidelines: Male Hypogonadism, Version 9 ↗
Anti-doping guidance
Original document reviewed.
Detail: Exemptions only for organic hypogonadism, not functional low testosterone from age, obesity or earlier steroid use.
- 94
openFDA Drug Shortages dataset ↗
Government shortage data (US)
Structured data reviewed.
Detail: No entry for any testosterone product.
- 95
Kyzatrex - T 174 > 869 ↗
Community account
Public thread reviewed: opening post and 5 comments.
Detail: A man in his 50s describes starting Kyzatrex at 200 mg twice daily, a later increase to 300 mg twice daily and a cash price.
- 96
Progress after one year of Jatenzo ↗
Community account
Public thread reviewed: opening post and 7 comments.
Detail: A man in his 30s on Jatenzo 237 mg twice daily describes a year of treatment alongside diet and training changes.
- 97
Any suggestions? Seriously, any? ↗
Community account
Public thread reviewed: opening post and 10 comments.
Detail: A man with reactions to injections and pellets describes earlier benefit from Tlando and trouble filling it.
- 98
Kyzatrex, left in car for couple hours. Is it okay? ↗
Community account
Public thread reviewed: opening post and 1 comments.
Detail: A person who blamed an injection ingredient for years without relief reports first improvement on capsules and asks about heat-exposed capsules.
- 99
What to expect or monitor over coming weeks/months? ↗
Community account
Public thread reviewed: opening post.
Detail: A man in his 40s whose levels stayed low on oral testosterone for 6 months describes switching to a compounded cream.
- 100
Switched Jatenzo / Kyzatrex ↗
Community account
Public thread reviewed: opening post and 8 comments.
Detail: A man in his 40s describes 6–7 months on two oral brands, a low later result and a move to injections.
- 101
Clinically Diagnosed Hypogonadism - Want to Try Xyosted ↗
Community account
Public thread reviewed: opening post and 12 comments.
Detail: A man on Jatenzo 237 mg twice daily for over 2 months reports a total testosterone of 267 ng/dL.
- 102
Starting injections in a few days. ↗
Community account
Public thread reviewed: opening post and 3 comments.
Detail: A man who used pellets and then Jatenzo says the capsules helped at first and then faded.
- 103
Swapping from Jatenzo to Xyosted ↗
Community account
Public thread reviewed: opening post and 2 comments.
Detail: A person describes about 6 months of twice-daily capsules with little change before a switch to a weekly injection.
- 104
No relief in symptoms ↗
Community account
Public thread reviewed: opening post and 15 comments.
Detail: A man on an unnamed oral product at 300 mg twice daily reports no symptom change after 45 days.
- 105
Will TRT help me? Oral Test and Clomid didnt ↗
Community account
Public thread reviewed: opening post and 9 comments.
Detail: A man in his 30s describes 45 days on a 40 mg oral capsule without improvement and with acne.
- 106
Nothing works and I’m starting to lose the fight. ↗
Community account
Public thread reviewed: opening post and 42 comments.
Detail: A man in his 40s with chronic pain describes no benefit from Tlando after reactions to other forms.
- 107
Kyzatrex (or similar) experiences ↗
Community account
Public thread reviewed: opening post and 11 comments.
Detail: A person on Kyzatrex 200 mg twice daily describes restless energy about 2 hours after doses.
- 108
Has anyone been on Kyzatrex (or similar) for over a year? ↗
Community account
Public thread reviewed: opening post and 21 comments.
Detail: A person describes nervous energy and brain fog after doses, stopping at about 2 months and later feeling better on injections.
- 109
Has anyone taken oral undecanoate (Jatenzo, Kyzatrex, Tlando) only once per day? ↗
Community account
Public thread reviewed: opening post and 17 comments.
Detail: A man in his 40s on 200 mg twice daily describes surges of nervous energy and a later switch to injections.
- 110
Hot flashes from Kyzatrex ↗
Community account
Public thread reviewed: opening post and 10 comments.
Detail: A person restarting Kyzatrex at 150 mg twice daily describes flushing and restlessness a few hours after doses.
- 111
How long before my balls shrink and/or loads are smaller? ↗
Community account
Public thread reviewed: opening post and 55 comments.
Detail: A man on Kyzatrex 200 mg twice daily for about 4 months reports a level rising from 230 to 1,017, LH and FSH of 0.6 and a later switch to pellets.
- 112
Energy ups & downs on Kyzatrex considering switch to Cypionate. Anyone experienced similar? ↗
Community account
Public thread reviewed: opening post and 6 comments.
Detail: A person on oral testosterone with hCG describes energy swings at 400 and 200 mg a day.
- 113
Suggestions for 30g fat intake for oral TRT (undecanoate) ↗
Community account
Public thread reviewed: opening post and 10 comments.
Detail: A person about to start oral testosterone asks how to reach a 30 g fat breakfast.
- 114
kyzatrex and fat intake?? help ↗
Community account
Public thread reviewed: opening post and 3 comments.
Detail: A person who switched from injections for travel reasons asks whether eggs and avocado provide enough fat.
- 115
What kind of food should I be taking with Tlando? ↗
Community account
Public thread reviewed: opening post and 9 comments.
Detail: A person on Tlando describes the burden of meal timing and later paranoia with a high free testosterone.
- 116
Jatenzo stopped working after a year ↗
Community account
Public thread reviewed: opening post and 13 comments.
Detail: A person describes a year on Jatenzo, often taking both daily capsules together, with later low results drawn 2.5–3.5 hours after a capsule.
- 117
Seeking guidance on Tlando ↗
Community account
Public thread reviewed: opening post and 7 comments.
Detail: A person describes taking Tlando after breakfast and lunch on spoken instructions that differed from the label.
- 118
Jatenzo blood pressure ↗
Community account
Public thread reviewed: opening post and 2 comments.
Detail: A person a month into Jatenzo describes blurred vision and a blood pressure of 139/98.
- 119
Jatenzo Experience’s ↗
Community account
Public thread reviewed: opening post.
Detail: A man in his 40s two weeks into Jatenzo reports more energy and an average blood pressure of 150/93.
- 120
Considering TRT (Kyzatrex) — looking for advice from those with experience ↗
Community account
Public thread reviewed: opening post and 88 comments.
Detail: A man in his 40s with a history of panic attacks stopped Kyzatrex after 3 days of anxiety.
- 121
Can TRT affect mood this drastically? ↗
Community account
Public thread reviewed: opening post and 5 comments.
Detail: A man on Jatenzo 237 mg twice daily describes anxiety and intrusive thoughts after restarting following a month-long gap.
- 122
Just started enclomiphene+ oral testosterone and have some questions ↗
Community account
Public thread reviewed: opening post and 24 comments.
Detail: A man in his 40s on oral testosterone with enclomiphene describes oily stools and later lab results.
- 123
Low dose (80mg per week or less) and Hematocrit ↗
Community account
Public thread reviewed: opening post and 4 comments.
Detail: A person describes several unwanted effects within 4 days of starting Kyzatrex.
- 124
Husband having terrible experience, need advice ↗
Community account
Public thread reviewed: opening post and 76 comments.
Detail: A woman describes her husband's weight gain and lower libido on Jatenzo before other medicines were tried.
- 125
Where are you all getting kyzatrex? ↗
Community account
Public thread reviewed: opening post and 13 comments.
Detail: A person describes pharmacies being out of stock of Kyzatrex.
- 126
Doctor Prescribed Kyzatrex (oral testosterone) but Unable to Find a Pharmacy ↗
Community account
Public thread reviewed: opening post and 11 comments.
Detail: A person describes finding Kyzatrex through an online pharmacy after local pharmacies could not fill it.
- 127
Trt advice and oral trt ↗
Community account
Public thread reviewed: opening post and 9 comments.
Detail: A man in his 30s with a needle phobia describes difficulty getting Kyzatrex outside the United States.
- 128
TLando Experience? ↗
Community account
Public thread reviewed: opening post.
Detail: A person prescribed Tlando reports a $0 copay quote.
- 129
starting Jatenzo today ↗
Community account
Public thread reviewed: opening post and 12 comments.
Detail: A man in his 30s starting Jatenzo 237 mg twice daily reports a $77 copay later covered by a coupon.
- 130
Kyzatrex- Where to buy and how much do you pay? ↗
Community account
Public thread reviewed: opening post and 16 comments.
Detail: A person in the third week of Kyzatrex reports paying $400 a month for the medicine and clinic charges.
- 131
Post-shot bloodwork timing for low levels to get Jatenzo approval ↗
Community account
Public thread reviewed: opening post and 17 comments.
Detail: A person describes an insurer requiring two recent low testosterone results before covering capsules.
- 132
Oral testosterone as a “pulse” on top of enclomiphene? ↗
Community account
Public thread reviewed: opening post and 25 comments.
Detail: A man in his 30s asks about adding oral testosterone to enclomiphene; no outcome is reported.
- 133
DEPO-Testosterone (testosterone cypionate) injection, USP CIII ↗
Product label (US)
Full label reviewed.
Detail: 50–400 mg intramuscular every 2–4 weeks.
- 134
NATESTO (testosterone) nasal gel, CIII ↗
Product label (US)
Full label reviewed.
Detail: 11 mg (one 5.5 mg spray in each nostril) three times daily, 33 mg a day.
- 135
TESTOPEL (testosterone pellets) for subcutaneous implantation, CIII ↗
Product label (US)
Full label reviewed.
Detail: 150–450 mg (two to six 75 mg pellets) every 3 to 6 months.
No matching sources
Try a different term or show the full list.
Updates and corrections
Updated September 29, 2026. This version replaces the earlier oral testosterone, Jatenzo, Kyzatrex, Tlando and Andriol guides with one rewrite based on the current US and Canadian labels, FDA approval records and current clinical guidelines. It adds a protocol table with each schedule's source, each product's blood-draw window, the food studies, the blood-pressure data from each label, storage rules, what happens when capsules stop, the full TRAVERSE results and a dated legal-status summary. It corrects the earlier pages on several points: the capsules are absorbed mostly, not entirely, past the liver; estradiol rises on capsules rather than staying at baseline; capsules raise hematocrit about as much as injections rather than less; Kyzatrex's lowest dose is 100 mg once daily, its 100 mg capsule is discontinued and a 50 mg capsule was added in 2026; Tlando's label says to stop if levels are above 1,080 ng/dL as well as below 300; the missed-dose advice now follows the Canadian product information; and Andriol is no longer marketed in Canada, the UK or Australia. The date describes this revision, not a fresh check of every source.
Found an error or a relevant study we missed? Report a correction with the guide title, the specific passage and a supporting source if available. Please leave out personal health records. See our editorial policy for how we handle attribution, evidence limits and corrections.