
In this guide
What is enclomiphene?
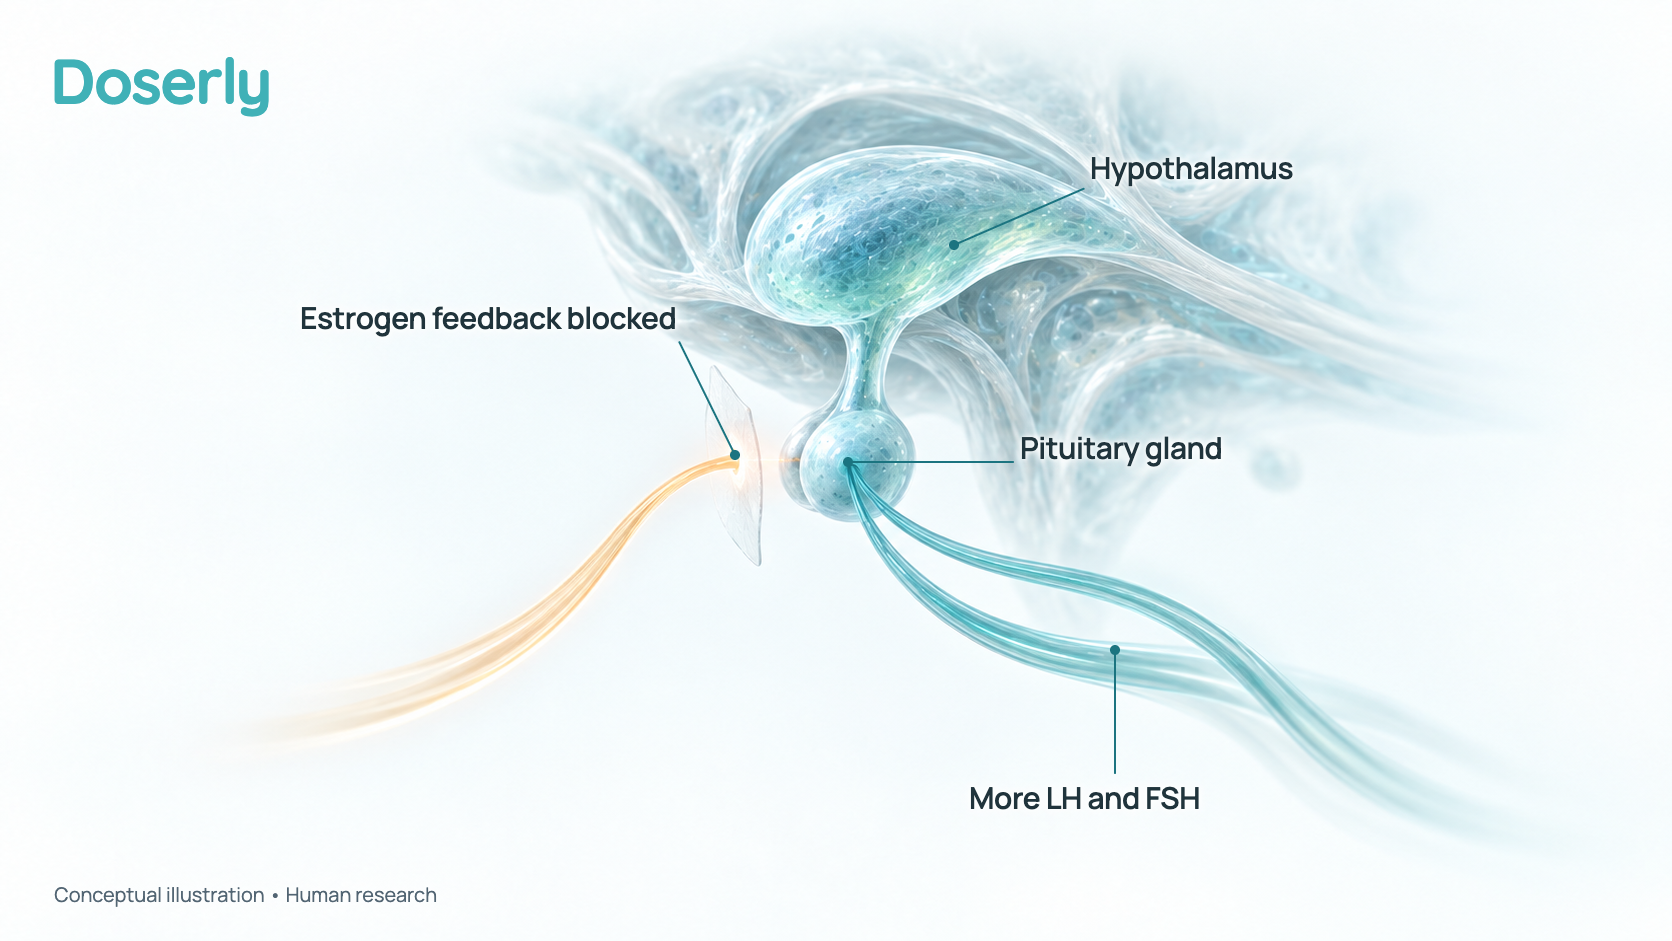
Enclomiphene is a tablet or capsule that raises a man's own testosterone instead of replacing it. It blocks estrogen's "slow down" signal at the base of the brain, so the pituitary gland releases more of the hormones that tell the testicles to make testosterone and sperm. It has never been approved as a medicine anywhere. [1], [2], [3]
The name comes from its parent drug. Clomiphene (Clomid), an approved fertility pill for women, is a mix of two forms of the same molecule whose atoms are arranged differently in space (stereoisomers): zuclomiphene and enclomiphene. Enclomiphene is the "trans" form, also written enclomifene in Europe. Zuclomiphene makes up 30–50% of clomiphene, lingers in the body for over a month and acts partly like estrogen; enclomiphene clears within days and, in laboratory tests, only blocks estrogen. [4], [5], [1]
It belongs to a group of medicines called SERMs (selective estrogen receptor modulators), which also includes clomiphene and tamoxifen. Taking enclomiphene alone is meant to keep clomiphene's testosterone-raising half without its longer-lasting, estrogen-like half. [6], [3]
| Name | What it is | Status (checked September 2026) |
|---|---|---|
| Enclomiphene citrate | The salt form in trials and compounded products | Not approved in any country |
| Androxal | Development name in the US trials (Repros Therapeutics) | FDA application not approved (2015); development stopped |
| EnCyzix | Proposed European brand | Refused by the European Union (2018) |
| Compounded enclomiphene | Capsules, tablets, sublingual liquids and combination tablets made by pharmacies | Allowed in the US only while FDA evaluates it |
Men meet it as an alternative to testosterone replacement therapy (TRT), usually because they want to keep their fertility, dislike injections or want to see whether their own production can recover. That reason matters, because the choice between the two is really a choice between two different strategies (compare).
Typical Enclomiphene Protocols
| Source | Amount each time | How often | Weekly total | Adjusted by | Source type |
|---|---|---|---|---|---|
| Approved label · any country | Not applicable | Not applicable | Not applicable | No approved product exists in the US, EU, UK, Canada or Australia | Regulator Checked September 2026. There is no labeled dose to anchor the table |
| Proposed EU label · EnCyzix, refused in 2018 | 8.5 mg enclomiphene base (about 12.5 mg as citrate) | Once daily | About 87.5 mg as citrate (175 mg after an increase) | Morning testosterone after 4–6 weeks: increase to 17 mg base (about 25 mg citrate) if below 450 ng/dL | Regulator (refused application) Proposed for overweight men aged 60 or under; never authorized |
| British Society for Sexual Medicine (BSSM) 2026 · position statement | 6.25 mg, rising weekly as tolerated to 25 mg | Once daily | 43.75–175 mg (up to 350 mg) | Tolerance; up to 50 mg daily only if the clinical or blood-test response is inadequate | Guideline Advises use only by experienced clinicians in specialist or research settings |
| Phase 3 trials ZA-304 and ZA-305 · overweight men 18–60, 16 weeks | 12.5 mg, increased to 25 mg if needed | Once daily, in the morning | 87.5 or 175 mg | Morning testosterone at week 4: increase if below 450 ng/dL | Human trial |
| Phase 3 trials ZA-301 and ZA-302 · overweight men 18–60, 12 weeks | 12.5 mg, increased to 25 mg if needed | Once daily, 7–10 a.m. | 87.5 or 175 mg | Morning testosterone at week 6: increase if below 300 ng/dL | Human trial Only 21 of 113 men in ZA-301 needed the increase |
| Open-label safety trial ZA-300 · 499 men, 26 weeks | 12.5 mg, increased to 25 mg if needed | Once daily | 87.5 or 175 mg | Morning testosterone at weeks 6 and 16: increase if below 450 ng/dL | Human trial |
| Phase 2 trial ZA-203 · 3 months | 12.5 mg or 25 mg (fixed) | Once daily | 87.5 or 175 mg | Not adjusted | Human trial |
| Phase 2 trial ZA-204 · 6 weeks | 6.25, 12.5 or 25 mg (fixed) | Once daily | 43.75–175 mg | Not adjusted | Human trial |
| Trial ZA-205 · obese men on a diet and exercise program, 48 weeks | 12.5 mg or 25 mg (fixed) | Once daily, in the morning | 87.5 or 175 mg | Not adjusted | Human trial |
| US university urology practice (2023) · men seen for infertility, abnormal semen results or low testosterone | 12.5 mg (30% of men) or 25 mg (70%) | Once daily | 87.5 or 175 mg | Not reported; at least 3 months of treatment | Clinic protocol source |
Every trial, and the one published clinic study, used 12.5 or 25 mg once a day, usually starting at 12.5 mg. The British position statement starts lower, at 6.25 mg, and is the only source that allows 50 mg. [1], [17], [3]
- Titration Adjusting the dose in steps
- The trials measured morning testosterone after 4 to 6 weeks and increased 12.5 mg to 25 mg if it was below 450 ng/dL (about 15.6 nmol/L) or, in two trials, below 300 ng/dL (about 10.4 nmol/L). The American Urological Association (AUA) gives a rule for the SERM class: if testosterone stays low four weeks after starting and LH is low or normal, a higher dose may help; if LH is high, the testicles themselves are probably failing and a higher dose is unlikely to help. [1], [18]
- Breaks and cycles
- Not established. No study tested cycling, planned breaks or every-other-day schedules. The effect lasts only while it is taken: testosterone was back to its starting level about a month after stopping (what happens when you stop). [19], [1]
Read the units. Doses are in milligrams (mg) of enclomiphene citrate, the salt form. The salt adds weight, so 12.5 mg of enclomiphene citrate contains about 8.5 mg of enclomiphene itself; that is why the European application wrote its doses as 8.5 mg and 17 mg. Check which one a product label states. There is no injection, so no syringe arithmetic applies. For testosterone results, 300 ng/dL is about 10.4 nmol/L, and the testosterone unit converter does the rest. [20], [1]
These are trial, guideline and published clinic doses for an unapproved drug; prescribers adjust them using blood tests and symptoms. These guides are for men; for women, see testosterone therapy for women.
Cautions for every schedule above. No approved product means no approved leaflet, no tested product standard and no label warnings. The European review found blood clots and a fatal stroke only in men taking enclomiphene, and the British statement rules it out with liver disease. It will not work if the testicles have failed. Men who might change their minds about fertility, or who have had clots, strokes, eye problems or liver disease, have the most to discuss first (risks). [1], [3], [21]
Where these numbers come from
There is no approved label anywhere (checked September 2026), so the first row records that absence. The refused European proposal comes from the European Medicines Agency's 2018 assessment report, which quotes the proposed product information: 8.5 mg once daily, increased to 17 mg if morning testosterone stays below 450 ng/dL after 4–6 weeks. The citrate equivalents use the molecular weights in PubChem (406.0 for enclomiphene, 598.1 for the citrate). [1], [7], [20]
The guideline row comes from the British Society for Sexual Medicine position statement on enclomiphene (2026), which gives the only dose instruction in any guideline; no US, European or Canadian guideline gives an enclomiphene dose. Three of its five authors list an affiliation with a UK online men's-health company, while the article declares no conflicts of interest. [3]
The trial rows come from the European assessment report's description of each protocol (ZA-304/305, ZA-301/302, ZA-300) and from the ClinicalTrials.gov records with posted results (ZA-203, ZA-204, ZA-205); ZA-204 is also published in full. All were run by the drug's developer. The clinic row comes from a retrospective study at a US university urology practice that published the dose split of its patients. [1], [11], [12], [13], [14], [22], [15], [16], [17]
Not used for any row: every-other-day, three-times-a-week or 6.25 mg every-other-day schedules (common online and in some clinic offers, but no study has tested them), 50 mg as a routine dose (only the British statement's ceiling), a sublingual multi-ingredient product studied in 15 men without a comparison group, enclomiphene added to TRT or to hCG after stopping TRT (never studied), and aromatase inhibitor add-ons. [10]
What is enclomiphene commonly used for?
It is used to raise testosterone in men whose low testosterone comes from the brain and pituitary rather than the testicles, especially men who want to keep making sperm. That was the use its developer asked regulators to approve, and neither the US nor the European regulator was convinced it helps men feel better. [2], [1]
- Raising testosterone without TRT. The trials enrolled men with secondary hypogonadism, mostly overweight men with low testosterone and low or normal LH. Testosterone rose in most of them. [1]
- Keeping fertility. Unlike TRT, it does not shut down sperm production in most men. It is not proven to improve the chance of a pregnancy. [1], [2]
- Recovery after TRT or steroids. Widely discussed online, but not studied. [23]
The VA notes that enclomiphene "is sometimes used in isolation, because it has less estrogenic effect than zuclomiphene"; the European Academy of Andrology calls the evidence for such anti-estrogens "poor". [6], [24]
Does enclomiphene raise testosterone?
Yes, in men whose pituitary and testicles work. In the two 12-week phase 3 trials, 78.8% of 113 men and 81.3% of 134 men reached an average testosterone of 300–1,040 ng/dL (about 10.4–36.1 nmol/L). In a 3-month phase 2 trial, morning testosterone rose by about 259 ng/dL (9.0 nmol/L) on 12.5 mg and 197 ng/dL (6.8 nmol/L) on 25 mg, similar to the 254 ng/dL (8.8 nmol/L) rise on a testosterone gel, against a fall of 17 ng/dL (0.6 nmol/L) on placebo. [12], [14]
A 2025 meta-analysis of randomized trials of clomiphene or enclomiphene found they raised testosterone by about 274 ng/dL (about 9.5 nmol/L) more than placebo, similar to testosterone gel. In obese men, a 2023 meta-analysis found enclomiphene raised testosterone by an average of 7.50 nmol/L (about 216 ng/dL) from before treatment. [25], [26]
It does this by raising LH and FSH, the opposite of TRT. In the phase 3 trials, LH and FSH rose on enclomiphene, stayed the same on placebo and fell on testosterone gel. [1], [27]
Does enclomiphene help symptoms like libido, energy and mood?
No trial has shown that it does, and that is why it was never approved. The trials chose men by their blood tests, not their symptoms, and most measured only hormones and sperm. [1], [2]
The one submitted trial that measured symptoms with questionnaires, ZA-003 (194 men aged 18 to 68), found:
- Testosterone: normal by month 3 in 63.8% on 12.5 mg and 64.0% on 25 mg, against 22.4% on placebo and 54.2% on AndroGel. [1]
- Sex drive: only AndroGel improved the libido score of the International Index of Erectile Function at every time point. [1]
- Erections: only the placebo group improved at every time point. [1]
- Other questionnaires: sexual desire and sexual distress scores improved in every group, including placebo, and the European committee found that these questionnaires showed no benefit for enclomiphene compared with placebo. [1]
The European committee concluded that "restoration of testosterone levels alone would not be sufficient" to show a benefit, and FDA wrote in 2022 that the trials "did not demonstrate that enclomiphene citrate provides clinically meaningful improvement in symptoms or signs of hypogonadism". The AUA adds that the benefits of testosterone therapy "cannot be extrapolated" to these alternative medicines. A 2026 meta-analysis of clomiphene, enclomiphene's parent, found libido improved less on clomiphene than on TRT. [1], [2], [18], [28]
The same gap is the most common theme in what people report (community).
Does enclomiphene protect fertility?
It keeps sperm production running in most men, which testosterone does not, but no study has shown it leads to pregnancies. In two 16-week phase 3 trials, sperm concentration held steady on enclomiphene and fell sharply on testosterone gel: [1]
| Trial (16 weeks) | Median change in sperm concentration | Men ending below 10 million/mL |
|---|---|---|
| ZA-304 | AndroGel −77.5% · enclomiphene −3.3% · placebo −10% | AndroGel 19 of 43 (44.2%) · enclomiphene 1 of 41 (2.4%) · placebo 0 |
| ZA-305 | AndroGel −39.49% · enclomiphene +8.95% · placebo −4.39% | AndroGel 10 of 42 (23.8%) · enclomiphene 1 of 44 (2.3%) · placebo 1 of 41 (2.4%) |
The picture is not all one way. In the 12-week trials ZA-301 and ZA-302, 14.2% of men on enclomiphene had their sperm concentration fall by half or more, against 2.6% and 4.3% on placebo, and the European committee called the sperm results "inconclusive". The company then removed sperm preservation from the use it asked to have approved. [12], [1]
A sperm count is not a pregnancy. FDA's advisory committee voted in 2016 that, for low testosterone linked to obesity, raising testosterone and keeping sperm counts is not enough to show a benefit, and that, in men with low or absent sperm counts, raising sperm concentration above a threshold would not show a benefit either: pregnancy outcomes would be needed. No enclomiphene study has reported one. A 2024 meta-analysis of SERMs in men with secondary hypogonadism found limited pregnancy or live-birth data. [2], [29]
For infertile men with low testosterone, the AUA/American Society for Reproductive Medicine (ASRM) guideline allows SERMs, hCG or aromatase inhibitors (conditional recommendation, low-certainty evidence), and notes that only hCG is FDA-approved for men. See TRT and fertility. [30]
Can enclomiphene replace TRT? Can it restart production after TRT or steroids?
It can stand in for TRT only in men whose pituitary still works, and it has not been studied after TRT or steroids. Every trial tested enclomiphene instead of testosterone. In a small phase 2B trial of 12 men switched off testosterone gel, testosterone reached similar levels on enclomiphene and gel at 6 months, and sperm counts were 75–334 million/mL in all 7 men on enclomiphene at 3 months, while the gel did not raise any of the 5 men above 20 million/mL at 3 months. [19], [31]
After longer TRT or anabolic steroids, the pituitary has been switched off for months or years, and that situation has not been studied: a 2026 review called enclomiphene a possible future option that "lack[s] validation" after steroid use. Published recovery regimens after TRT are built around hCG, sometimes with a SERM added. See stopping TRT and hCG vs gonadorelin vs enclomiphene. [23], [32]
Does enclomiphene help weight, muscle or blood sugar?
Not in a way the trials could show; weight fell more on placebo. In the 48-week ZA-205 trial, 50 obese men (18, 17 and 15 per group) all followed a diet and exercise program. Men on placebo lost significantly more weight than on either dose (14.5 kg vs 4.4 kg on 12.5 mg and 6.2 kg on 25 mg), and the small differences in lean mass (up 3.1 and 2.4 kg vs 1.1 kg on placebo) were not statistically significant, according to the tests posted in the registry. The European committee noted that body fat, muscle and bone were never studied as main outcomes. [16], [1]
How long does enclomiphene take to work?
Blood levels respond within weeks; whether symptoms follow is not known. LH had already risen by week 2 in the phase 2 dose study, trials judged the dose at 4 to 6 weeks, and the phase 3 results were measured at 12 and 16 weeks. The AUA checks testosterone no sooner than 4 weeks after starting a SERM. [22], [1], [18]
Where do enclomiphene protocols differ?
With no label, sources disagree on where to start, how high to go, how often to take it and what to measure. Most of what circulates online has never been tested.
6.25 mg or 12.5 mg to start?
The trials started at 12.5 mg; the British statement starts at 6.25 mg and steps up weekly "as tolerated". The dose study behind the lower start (ZA-204) gave 6.25, 12.5 or 25 mg for 6 weeks and found average testosterone rose from about 262 to 392 ng/dL (9.1 to 13.6 nmol/L) on 6.25 mg, from 374 to 461 (13.0 to 16.0 nmol/L) on 12.5 mg and from 298 to 587 (10.4 to 20.4 nmol/L) on 25 mg, so every dose raised it and 25 mg raised it most. The groups were small, and the 12.5 mg group was the smallest (7 to 10 men, depending on the source), so the steps between the lower doses are not reliable. [1], [3], [22]
The practical difference is how fast the level climbs and how many side effects appear on the way. In the European review, adverse events were reported more often at the lower dose, but men were not randomized between doses, so that comparison is unreliable. [1]
Is 25 mg the ceiling, or 50 mg?
25 mg is the highest dose tested for more than two weeks. Only the British statement allows 50 mg daily "if there is an inadequate clinical or biochemical response". A 14-day study found testosterone rose less than in proportion to the dose between 25 and 50 mg, and blood levels of the drug itself also rose less than in proportion. [3], [1]
A 2026 case report describes a new heart-rhythm problem (atrial flutter) found shortly after a man accidentally took 50 mg instead of 25 mg daily; a formal assessment rated the link "possible" only. [33]
Every day, every other day or three times a week?
Every source with data used once a day. Every-other-day and three-days-a-week schedules are common in online advice and some clinic offers, but no enclomiphene study tested them. The every-other-day habit comes from clomiphene, which the AUA lists at 25–50 mg every 1 to 2 days and whose zuclomiphene half lingers for weeks. Enclomiphene's half-life is about 8 to 10 hours; in the phase 2 study, levels had not returned to baseline 24 hours after a dose, so it builds up somewhat on daily dosing. [18], [4], [1], [2]
What that means in practice is unknown: no one has measured testosterone or sperm on spaced schedules. What people report on them is in the community section.
What target, and when should blood be drawn?
The trials drew blood in the morning, judged success as an average testosterone of 300–1,040 ng/dL, and adjusted at 450 ng/dL (or 300 ng/dL in two trials). The AUA measures LH four weeks after starting a SERM if testosterone stays low, and again if a man who responded stops responding. It suggests measuring estradiol on SERMs as optional. [1], [18]
Because the drug has a short half-life, how many hours passed between the last dose and the blood draw may shift the result; no study has measured by how much. Recording both times makes results easier to compare. See TRT blood work.
Alone, or with TRT, hCG or an aromatase inhibitor?
Every trial used enclomiphene alone. Adding it to TRT has never been studied, and there is little for it to act on: TRT switches off the pituitary signals that enclomiphene works through. hCG plus enclomiphene has not been tested in a published trial. The VA does not generally recommend aromatase inhibitors, and no source gives an aromatase inhibitor dose alongside enclomiphene. [1], [34], [6]
Enclomiphene or clomiphene?
The head-to-head evidence is two retrospective records studies. In 66 men switched from clomiphene to enclomiphene, testosterone rose similarly, estradiol fell slightly instead of rising, and fewer reported side effects (13.8% vs 47%), though the study had no washout and recorded no doses. In 78 men seen for infertility, abnormal semen results or low testosterone at another practice there was no significant difference, and estradiol rose on enclomiphene. [35], [17] See how they differ and the clomiphene guide.
What happens when you stop enclomiphene?
The drug leaves within days, and testosterone falls back to where it started within about a month. [1], [19]
- The drug itself. With a half-life of about 8 to 10 hours, at least 90% of a dose would be eliminated within 14 days, according to the European review. [1]
- Hormones. LH, FSH and testosterone stayed raised for at least a week after the last dose in the phase 2 and phase 3 trials, then fell: in the phase 2B study of 12 men, testosterone was back to its pretreatment level one month after stopping. Enclomiphene raises a man's own production only while he takes it; it is not expected to fix the underlying cause. [15], [1], [19]
- Sperm. No study has followed sperm after stopping enclomiphene.
- Tapering and rebound. No source describes a taper or a rebound below the starting level. No study has looked.
Men who stop because it did not help may move to TRT; that switch shuts down sperm production, so it is worth settling fertility plans first. See stopping TRT and TRT and fertility.
How is enclomiphene taken, and how long does it last?
By mouth, once a day, in every study. The trials used 12.5 mg and 25 mg capsules; the nomination FDA reviewed for compounding proposed capsules or tablets of 12.5, 25 and 50 mg. [2], [1]
How long does enclomiphene last in the body?
Its pharmacokinetics (how the body absorbs and clears it) are simple: it is absorbed quickly and cleared in hours, not days. Blood levels peak about 2 to 3 hours after a dose, and the European review gives an elimination half-life of 8 to 10 hours (FDA's 2022 review says about 10 hours). The effect on hormones outlasts the drug: LH and testosterone stayed up for at least a week after stopping. [15], [1], [2]
The body breaks it down mainly through two liver enzymes, CYP2D6 and CYP3A4/5, and removes it mostly in the stool (61.5% of a dose) rather than urine (8.2%). Exposure rose more than in proportion to the dose from 12.5 to 25 mg: FDA's review reports blood exposure about 4.5 times higher at 25 mg than at 12.5 mg. [1], [2]
Should it be taken with food?
No food rule exists, because no label exists. In a study of 12 healthy men, a 25 mg dose taken with food gave slightly higher blood levels and a peak half an hour later (2.5 vs 2.0 hours). The European review judged the difference "not of clinical consequence"; the trials dosed in the morning. [1], [2]
How is enclomiphene different from clomiphene?
Clomiphene is the mix; enclomiphene is one half of it. The difference that matters is how long each half stays in the body:
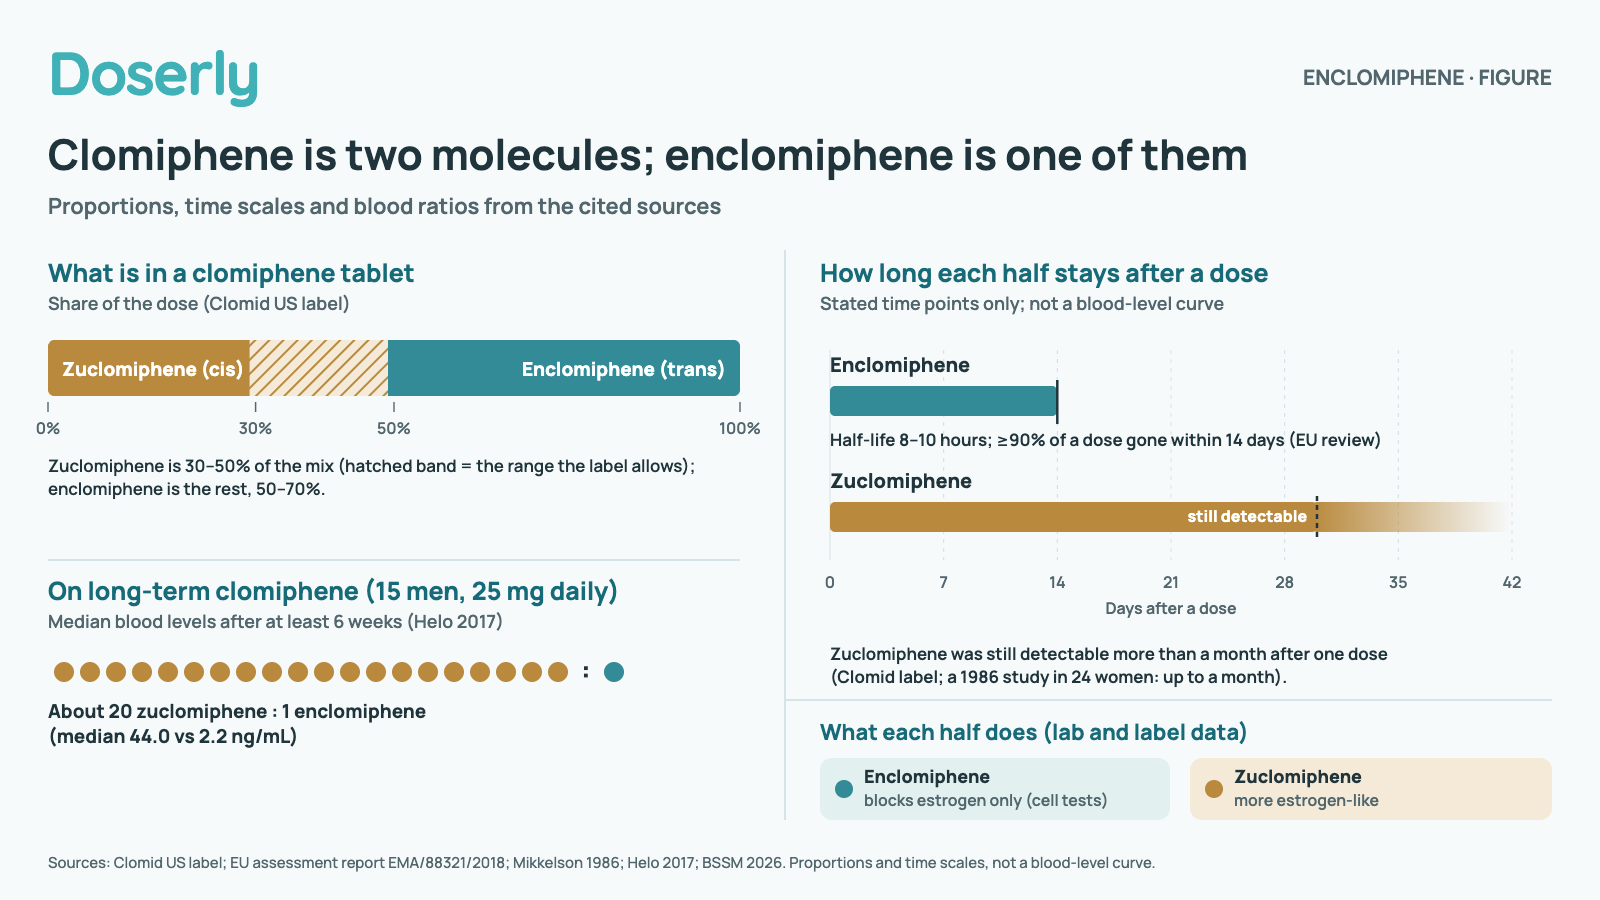
Clomiphene is two molecules; enclomiphene is one of them
Zuclomiphene (cis)Enclomiphene (trans)
- What is in a clomiphene tablet
- Zuclomiphene 30–50% (the paler band is the range the label allows); enclomiphene the rest, 50–70%. Clomid US label.
- Enclomiphene: how long it stays
- Half-life 8–10 hours; at least 90% of a dose gone within 14 days (EU review).
- Zuclomiphene: how long it stays
- Still detectable more than a month after one dose (Clomid label; a 1986 study in 24 women).
Bars run from 0 to 42 days after one dose; they mark stated time points, not blood levels.
On long-term clomiphene (15 men, 25 mg daily)
Median blood levels: zuclomiphene 44.0 ng/mL vs enclomiphene 2.2 ng/mL, about 20 to 1 (Helo 2017).
What each half does
Enclomiphene blocks estrogen only in cell tests (EU review); zuclomiphene is more estrogen-like (Clomid label, BSSM 2026).
Proportions and time scales from a US label, the EU assessment report and two human studies; not a blood-level curve.
- Clearance. In women given clomiphene, the zuclomiphene half was eliminated much more slowly than the enclomiphene half and was still detectable a month later. In 15 men on long-term clomiphene 25 mg daily, zuclomiphene outnumbered enclomiphene in the blood by about 20 to 1. [5], [36]
- Activity. In cell tests, the European review describes enclomiphene's activity as "solely antagonistic" (blocking only). The British statement calls zuclomiphene "more oestrogenic" and says pure enclomiphene avoids clomiphene's estrogen-like side effects. Support is limited: one records study found fewer side effects, and another found estradiol still rose. [1], [3], [35], [17]
- Status. Clomiphene is FDA-approved for ovulation problems in women and used off-label in men; enclomiphene is approved for no one. The Clomid label says there are no adequate studies showing it works for male infertility. [4]
Health Canada's view is blunter: "Enclomiphene is the active component of clomiphene; therefore, the risks and limitations of clomiphene also apply to enclomiphene." [37]
What forms are sold?
Because nothing is approved, every product is either compounded by a pharmacy under a prescription or sold outside the medical system:
- Compounded capsules or tablets, proposed in 12.5, 25 and 50 mg strengths in the nomination FDA reviewed. [2]
- Combination tablets, such as tadalafil 8.5 mg plus enclomiphene citrate 12.5 mg, listed in a June 2026 FDA inspection report. [9]
- Sublingual liquids. The only published data come from one practice: 15 men on a multi-ingredient liquid with 25 mg per dose, whose average testosterone rose from 347 to 805 ng/dL (12.0 to 27.9 nmol/L) over 60 days, with no comparison group and no LH, FSH or symptom data. [10]
- "Research use only" products sold online, which are not medicines and whose contents are unknown (product quality). [38], [39]
How should enclomiphene be stored?
Follow the pharmacy's label; no official storage rule exists. No approved product means no approved storage conditions or in-use period. FDA's review notes that clomiphene citrate is stable at controlled room temperature, protected from light, and expects enclomiphene citrate to behave the same way. For compounded enclomiphene, the dispensing pharmacy sets the storage instructions and the use-by date. [2]
What does enclomiphene do to fertility, estrogen and red blood cells?
Each of these has its own hub guide. Here is what is specific to enclomiphene.
Fertility. Enclomiphene raises LH and FSH instead of switching them off, and sperm concentration held steady in most men in trials where testosterone gel cut it, although 14.2% of men in two trials had a fall of half or more. No pregnancy data exist (details above). See TRT and fertility. [1], [12]
Estrogen. Because it raises testosterone, it raises estradiol too: the European review found significant rises on both enclomiphene and testosterone gel compared with placebo, and flagged them as a possible added clot risk. In 18 men on enclomiphene with before-and-after results, median estradiol rose from 29.5 to 67 pg/mL (about 108 to 246 pmol/L). Breast enlargement was reported in 0.2% of men on enclomiphene (none on testosterone gel or placebo) and gynecomastia in 0.07%, against 0.7% on testosterone gel. No guideline sets an estradiol target, and the VA does not generally recommend aromatase inhibitors. See estrogen on TRT. [1], [17], [6]
Red blood cells. It raises hematocrit less often than testosterone gel in the trial records: an increase was reported as a side effect at least possibly caused by the drug in 0.6% on enclomiphene, 1.4% on AndroGel and none on placebo. One man in ZA-300 reached a hematocrit of 55.4% before a deep vein clot and clots in both lungs. The trials excluded men with hematocrit above 54%. See hematocrit on TRT. [1]
The guide does not try to settle whether fertility goals should steer the choice of medicine; that depends on timing, the cause of low testosterone and a semen analysis. The Academy note below covers that planning conversation.
What do we actually know about enclomiphene in people?
That it raises testosterone, LH and FSH and spares sperm production in most men is well shown in trials of up to 16 weeks. Whether men feel or function better, and what happens over years, is not known. Almost all of the evidence comes from one developer's trial program, reviewed in detail by the US and European regulators.

Which trials tested enclomiphene?
| Study | Who and what | What it found | What it cannot show |
|---|---|---|---|
| ZA-304 and ZA-305 (Kim 2016, controlled trials) | Overweight men 18–60; enclomiphene vs AndroGel 1.62% vs placebo, 16 weeks | Testosterone up on both drugs; LH, FSH and sperm kept up only on enclomiphene | Symptoms; pregnancy; anything past 16 weeks [27], [1] |
| ZA-301 and ZA-302 | 113 and 134 men on enclomiphene vs placebo, 12 weeks | About 4 in 5 reached normal testosterone; sperm fell by half or more in 14.2% | Symptoms; not published as papers [12], [40] |
| ZA-003 | 194 men 18–68; enclomiphene vs placebo vs AndroGel, with symptom questionnaires | Normal testosterone in about 64% vs 22.4% on placebo; no symptom benefit shown over placebo | Planned as phase 3, later treated as supportive [1] |
| ZA-300 (open-label) | 499 men, 26 weeks | Testosterone up about 215–281 ng/dL (7.5–9.7 nmol/L); serious events included 2 leg clots and a lung clot | No comparison group [13], [2] |
| ZA-203 (Wiehle 2014) | Enclomiphene vs Testim gel vs placebo, 3 months | Testosterone rose as much as on gel; lower sperm counts in 8 of 33 on gel, none on enclomiphene | Symptoms; small groups [14], [41] |
| ZA-204 (Wiehle 2013) | 48 men; three doses vs AndroGel, 6 weeks | Testosterone rose on every dose (most on 25 mg) and stayed up a week after stopping | Anything past 6 weeks [15], [22] |
| ZA-205 | 50 obese men on diet and exercise, 48 weeks | Testosterone up about 174–237 ng/dL (6.0–8.2 nmol/L) vs 43 ng/dL (1.5 nmol/L); placebo lost significantly more weight | Small groups (18, 17 and 15 men); weight and lean mass were not the main outcomes [16] |
| Kaminetsky 2013 (phase 2B) | 12 men switched off testosterone gel, 6 months | Similar testosterone; sperm counts high only on enclomiphene | Very small; open-label [19], [31] |
The trial program was large for its length: 1,403 men took enclomiphene in phase 2 and 3 trials, 482 for more than 6 months and 116 for 12 months or more. Registry records list further studies (on age, kidney function, drug interactions and heart rhythm, and one-year extensions), none with posted results. No trial outside the developer's program is registered (searched September 2026). [1], [34]
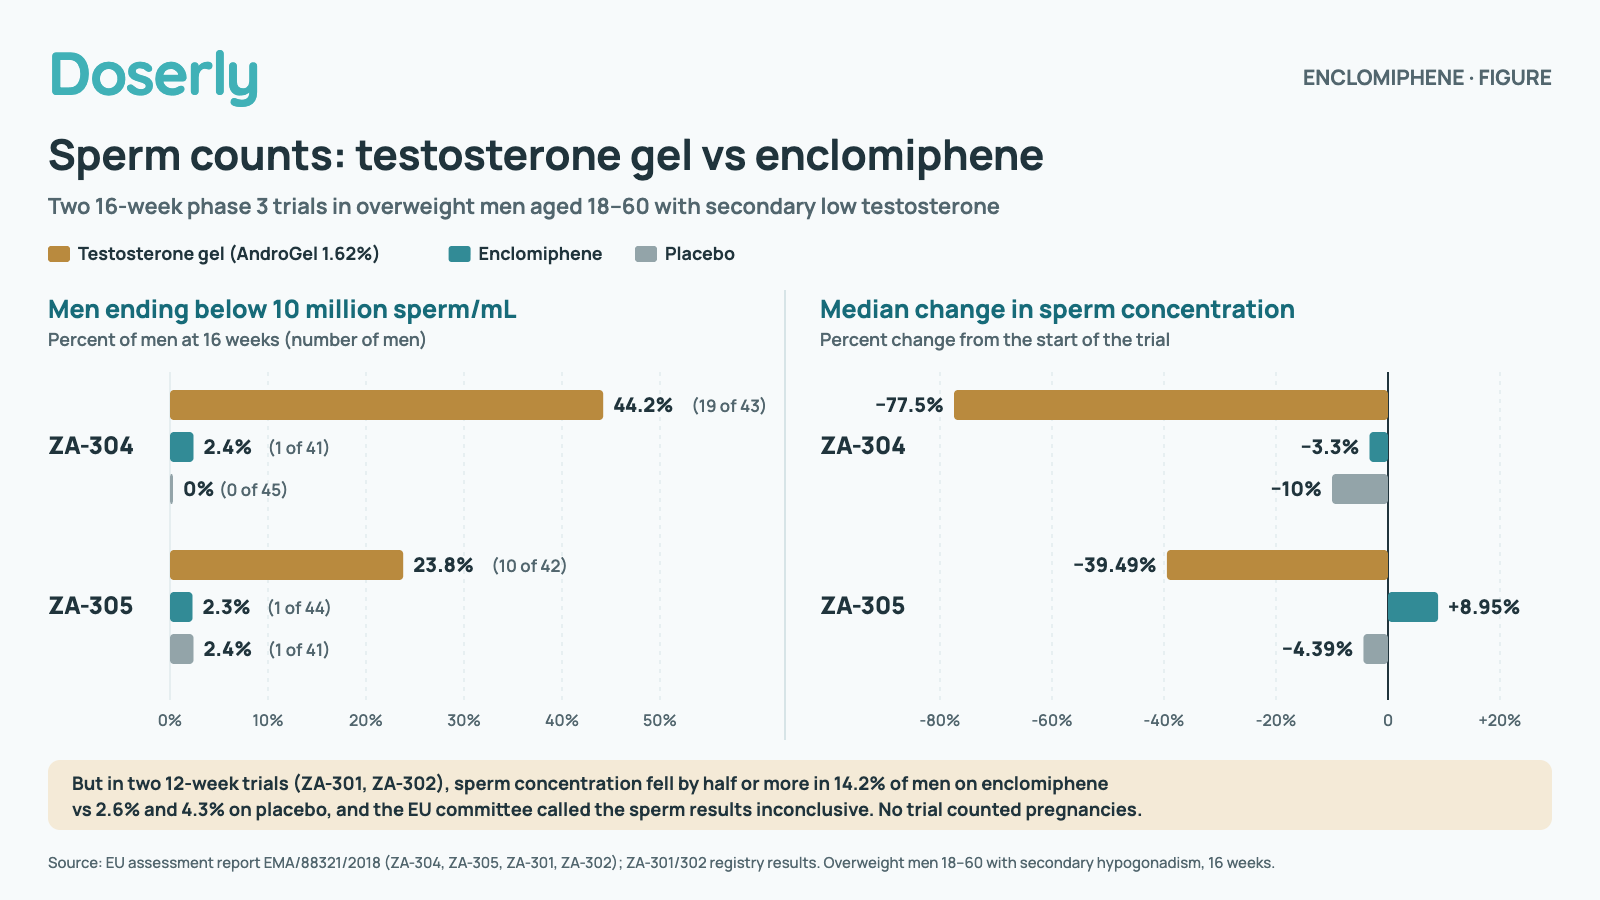
Sperm counts: testosterone gel vs enclomiphene
Two 16-week phase 3 trials in overweight men aged 18–60 with secondary low testosterone.
Testosterone gel (AndroGel 1.62%)EnclomiphenePlacebo
Men ending below 10 million sperm/mL
Bars run from 0 to 50% of men.
- ZA-304
- Testosterone gel 44.2% (19 of 43); Enclomiphene 2.4% (1 of 41); Placebo 0% (0 of 45)
- ZA-305
- Testosterone gel 23.8% (10 of 42); Enclomiphene 2.3% (1 of 44); Placebo 2.4% (1 of 41)
Median change in sperm concentration
Bars run from −80% to +20%; the line marks no change.
- ZA-304
- Testosterone gel −77.5%; Enclomiphene −3.3%; Placebo −10%
- ZA-305
- Testosterone gel −39.49%; Enclomiphene +8.95%; Placebo −4.39%
But in two 12-week trials (ZA-301, ZA-302), sperm concentration fell by half or more in 14.2% of men on enclomiphene vs 2.6% and 4.3% on placebo, and the EU committee called the sperm results inconclusive. No trial counted pregnancies.
Overweight men 18–60 with secondary hypogonadism, 16 weeks. Source: EU assessment report (EMA/88321/2018).
Why did regulators turn it down?
Both regulators read the same trials and reached the same conclusion: higher testosterone and preserved sperm counts are lab results, and the trials did not show the lab results made men better.
- United States, 2015. A planned FDA advisory committee meeting was cancelled over questions about how the trial blood tests were validated. In December 2015 the developer received a Complete Response Letter saying its phase 3 design was "no longer adequate to demonstrate clinical benefit", with concerns about entry criteria, dose titration and the blood-test method. [2]
- United States, 2016. At an FDA advisory committee on drugs for this condition, a majority voted that, for obesity-related low testosterone, raising testosterone and maintaining sperm concentration is not sufficient evidence of clinical benefit. [2]
- European Union, 2018. The committee gave a negative opinion on January 25, 2018: the trials did not select men by symptoms, used no validated symptom questionnaire, and the clot signal could not be excluded. [7], [1]
- United States, 2022. Reviewing enclomiphene for compounding, FDA listed safety concerns (heart and clot events, estradiol, PSA and hematocrit rises) and proposed that it not be added to the list of substances pharmacies may compound; its advisory committee voted 8 to 4 against adding it (4 in favor). FDA has not made a final decision. [2], [42], [8]
The British statement summarizes the evidence as coming "from small, short-term studies with limited safety and fertility data", while calling enclomiphene "a promising therapy". Its maker stopped development in 2021, according to the same statement. [3]
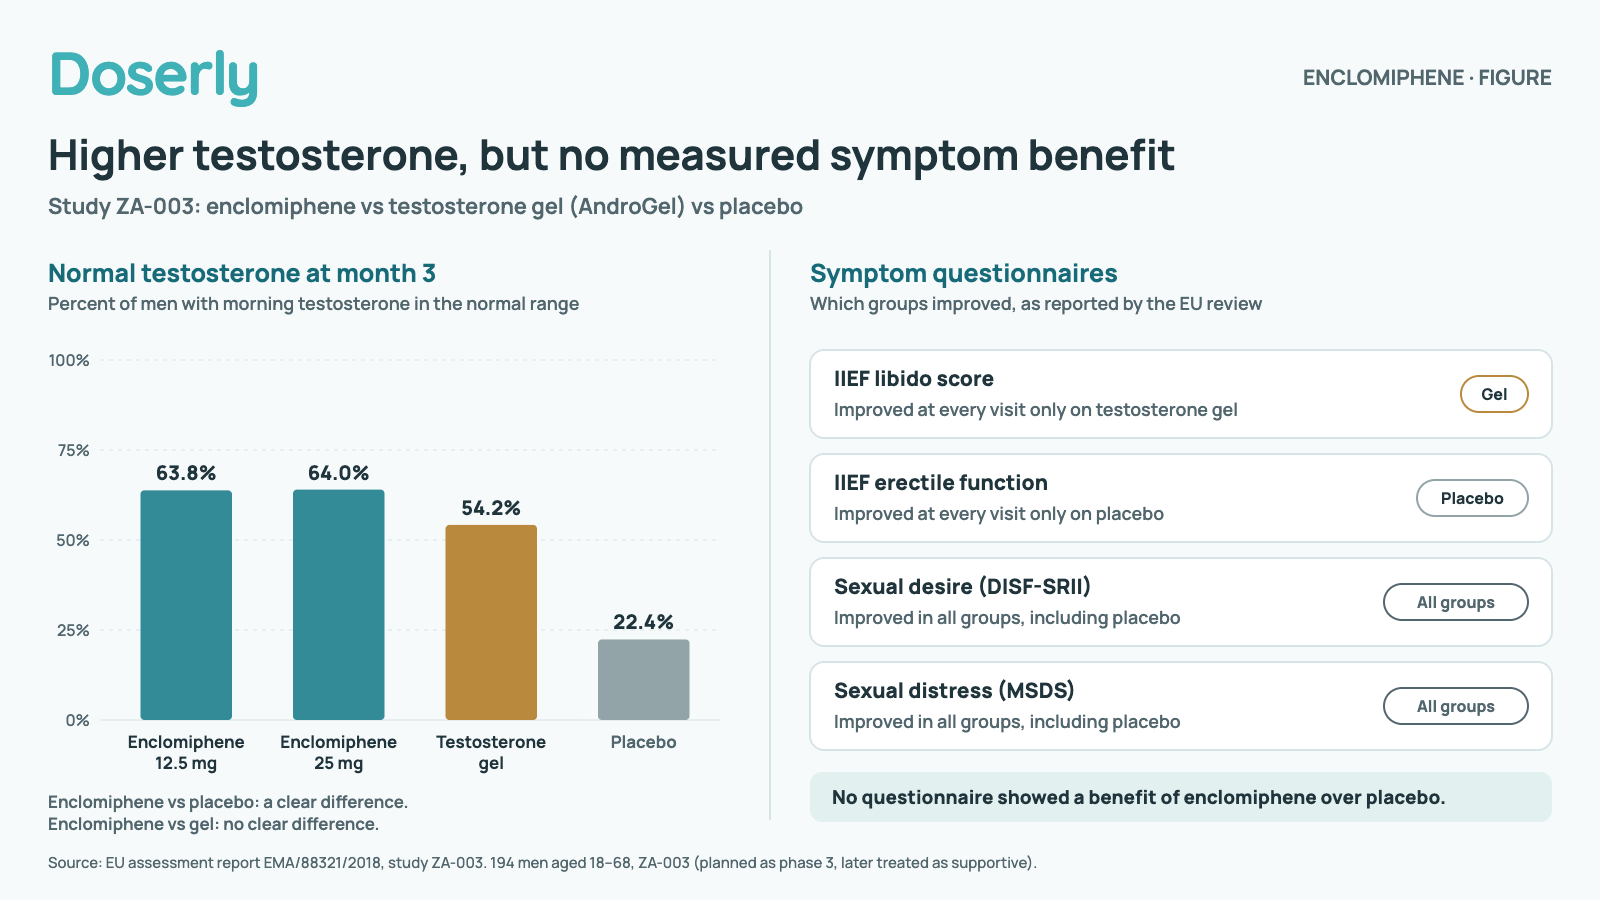
Higher testosterone, but no measured symptom benefit
Study ZA-003: enclomiphene vs testosterone gel (AndroGel) vs placebo.
Normal testosterone at month 3
- Enclomiphene 12.5 mg
- 63.8% of men
- Enclomiphene 25 mg
- 64.0% of men
- Testosterone gel (AndroGel)
- 54.2% of men
- Placebo
- 22.4% of men
Enclomiphene vs placebo: a clear difference. Enclomiphene vs gel: no clear difference.
Symptom questionnaires
- IIEF libido score
- Improved at every visit only on testosterone gel
- IIEF erectile function
- Improved at every visit only on placebo
- Sexual desire (DISF-SRII)
- Improved in all groups, including placebo
- Sexual distress (MSDS)
- Improved in all groups, including placebo
No questionnaire showed a benefit of enclomiphene over placebo. 194 men aged 18–68, ZA-003 (planned as phase 3, later treated as supportive).
What is still unknown?
Symptom benefit, pregnancies, safety beyond a year (only 116 men took it that long) and use after TRT, alongside TRT or on spaced schedules have not been studied, and every trial came from the developer. Bone density results from a 52-week study appear only as tables the published report does not make readable. [1], [2], [34]
How does enclomiphene work?
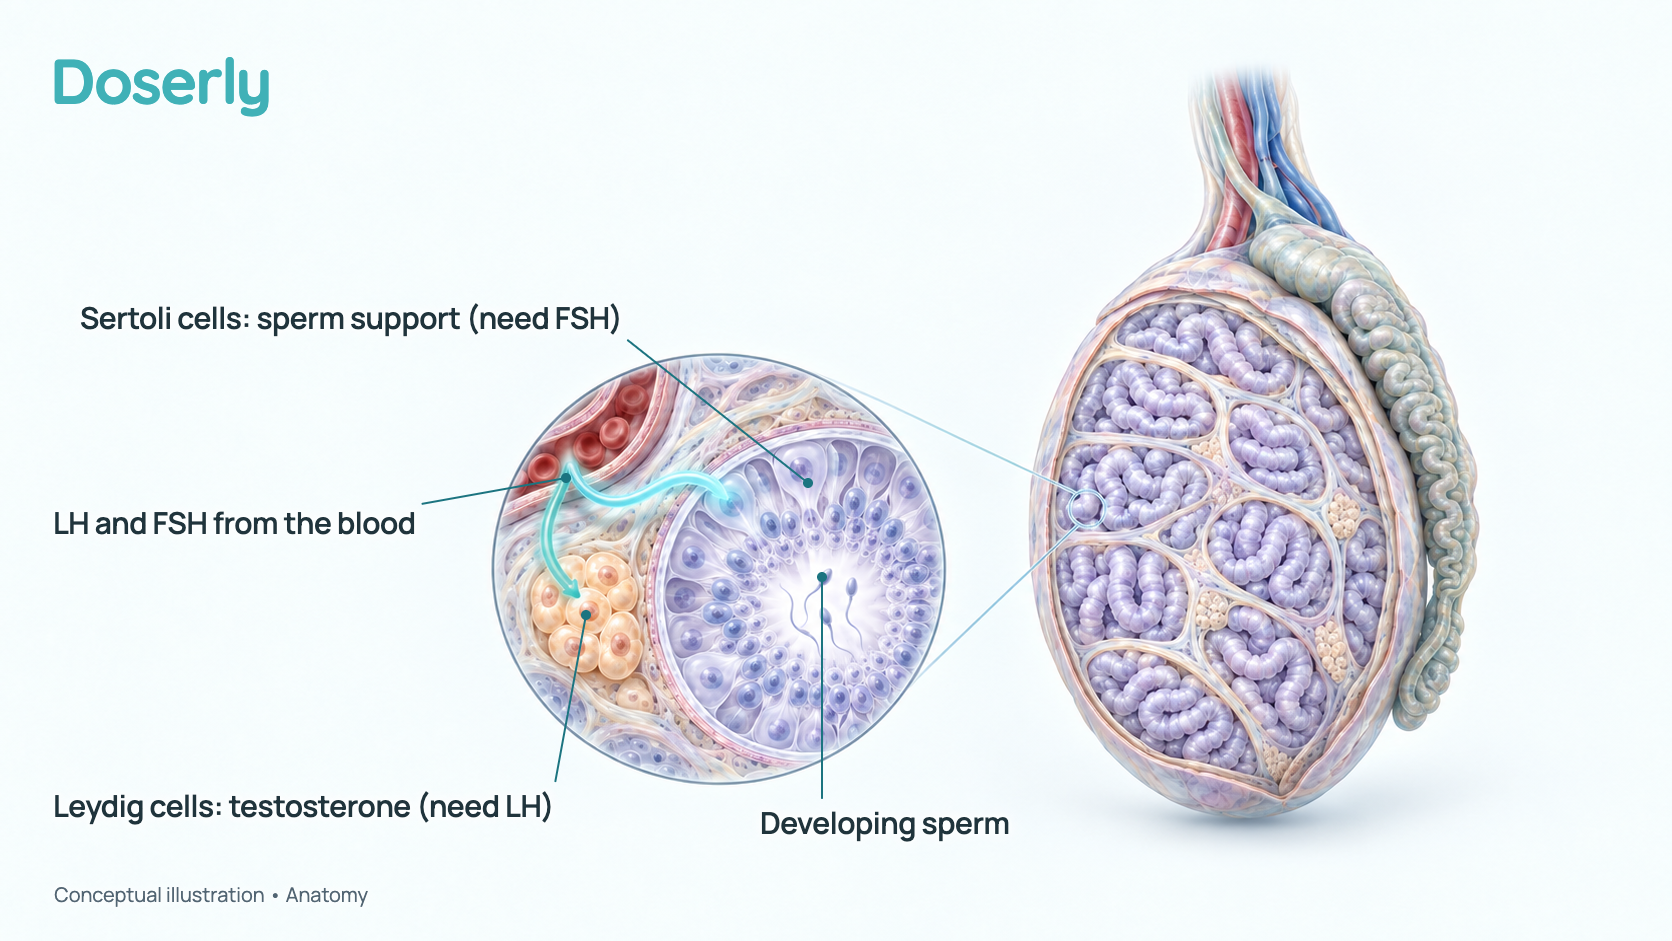
Testosterone production is a chain of signals. The hypothalamus at the base of the brain releases GnRH, which tells the pituitary gland to release LH and FSH. LH tells the testicles to make testosterone; FSH, together with the high testosterone level inside the testicle, drives sperm production. Estradiol, made partly from testosterone, feeds back to the hypothalamus and pituitary as a signal to slow down. [3], [18]
Enclomiphene blocks that feedback. It occupies the estrogen receptors in the hypothalamus and pituitary, so the brain reads estrogen as low and turns up LH and FSH. Working testicles respond by making more testosterone and sperm. This is established human pharmacology: LH, FSH and testosterone rose in the trials. [3], [1]
Why it needs a working chain. Every step has to work. If the testicles have failed (primary hypogonadism), LH is already high and more of it does nothing; if the pituitary is damaged, it cannot respond. The European urology guideline says SERMs "cannot work" in either case, and the AUA advises against raising the dose when LH is high. [21], [18]
Why TRT is different. Testosterone from outside does the opposite: the brain senses it and turns LH and FSH down, so the testicles make less of their own testosterone and sperm. Enclomiphene raises the same number by the opposite route. [27]
Why estradiol still rises. Blocking estrogen receptors in the brain does not stop the body making estradiol. As testosterone rises, more is converted to estradiol, and levels in the blood go up. [1]
What are the risks and unanswered questions?
Is enclomiphene safe?
Its short-term side effects in trials were mostly mild, but it carries a clot signal and has no long-term safety record or approved product. In the European review of 1,403 men, side effects occurred in 17.7% on enclomiphene, 19.7% on AndroGel and 8.7% on placebo; most were mild (12.1%) or moderate (4.6%), with 0.9% severe. The review also found blood clots and a fatal stroke only in men taking enclomiphene, and it concluded that a higher risk of clot-related events "cannot be excluded". [1]
What side effects were reported in trials?
The British statement's summary of the trial data lists headache (1.6%), hot flashes (1.1%), nausea (1.0%), muscle spasms (0.9%) and dizziness (0.7%) as the most common. The hot flash figure matches the European review's count of events judged at least possibly caused by the drug, so these are drug-related rates, not the overall chance of having a headache: in the open-label ZA-300 study, headache of any cause was reported by 12 of 207 men on 12.5 mg (5.8%) and 23 of 283 on 25 mg (8.1%). Compared with the other groups in the European review: [3], [1]
- Hot flashes: 1.1% vs 0.5% on placebo and none on testosterone gel. [1]
- Aggression: 0.5% vs none on placebo; anxiety was similar (0.4% in both). [1]
- Erectile dysfunction: 0.6% vs none on gel or placebo. [1]
- Testicular pain: 0.4% vs none on placebo and 0.7% on gel. [1]
- Stopping because of side effects: 74 men (5.3%) on enclomiphene, 8 (5.4%) on AndroGel and 6 (1.5%) on placebo; the most common reasons were blurred vision, muscle spasm, headache and aggression. [1]
Does enclomiphene cause blood clots or strokes?
A signal was seen, and it could not be ruled out. The European review counted 4 clot-related events across the trials, all on enclomiphene (one deep vein clot with clots in the lungs, two deep vein clots and one fatal ischemic stroke, a stroke caused by a blocked artery), and none on testosterone or placebo. The developer had also listed a heart attack on placebo, which the reviewers did not accept as a clot event. All four men on enclomiphene had other risk factors; the man who died had untreated atrial fibrillation. [1]
That is 4 of 1,403 men exposed, and most took it for only 12 to 18 weeks. The European committee noted that these events happened only on enclomiphene in a population already at high risk, and that the true size of the risk is unknown. In the 48-week ZA-205 trial, 1 heart attack and 1 ischemic stroke occurred among 18 men on 12.5 mg, against none among 17 on 25 mg or 15 on placebo. [1], [16]
Its parent drug adds context. Case reports describe clots in the lungs, brain veins and gut veins, and a heart attack in a man in his early 30s, in men taking clomiphene; such reports cannot give a rate. A US insurance-claims study of 12,318 men prescribed clomiphene, most for less than 6 months, found no increased risk of the side effects it tracked, including clots, vision problems and liver disease. The European urology guideline warns that SERMs may raise the risk of clots in the veins (venous thromboembolism). [43], [44], [45], [46], [47], [21]
What about the heart?
Heart problems were uncommon in trials: 5 men (1.0%) on enclomiphene against 1 (0.4%) on placebo, and 0.9% against 0.7% compared with testosterone. Serious events in ZA-300 included a mini-stroke, a slow heart rate and low blood pressure (each in 1 of 207 men on 12.5 mg) and atrial flutter (1 of 283 men on 25 mg). Two studies of the QT interval (a heart-rhythm measure on an ECG) found no meaningful change with 3 days of dosing at 25 mg (within about 1.5 milliseconds) or 100 mg (at most about 4 milliseconds); at 250 mg, ten times the top trial dose, the peak average change was about 12 milliseconds. No outcome trial exists. [1], [2], [13]
Testosterone therapy's own heart data. TRAVERSE, the largest heart-safety trial of testosterone, compared daily testosterone gel with placebo gel in about 5,200 men aged 45 to 80 at high heart risk. Among the 2,596 men on testosterone and 2,602 on placebo in the safety analysis, heart attack, stroke or cardiovascular death occurred in 182 (7.0%) and 190 (7.3%), a hazard ratio of 0.96 (95% confidence interval 0.78 to 1.17), which met the trial's safety margin. Atrial fibrillation (3.5% vs 2.4%), acute kidney injury (a sudden drop in kidney function; 2.3% vs 1.5%) and lung clots (pulmonary embolism; 0.9% vs 0.5%) were more common on testosterone. It tested only a gel, men used it for 21.7 months on average and about 61% stopped their study gel early. It did not test enclomiphene, so its results do not transfer. See TRT and heart health. [48], [49]
Can enclomiphene affect your eyes?
Blurred vision was reported in trials, and clomiphene's label treats vision changes as a reason to stop. In the placebo-controlled trials, eye disorders overall were reported in 1.6% on enclomiphene and 2.4% on placebo; blurred vision in 14 men (1.0%) and 3 on placebo (0.8%), with 12 of the 14 on 12.5 mg. Cataract and blurred vision judged at least possibly related were reported in 0.3% and 0.5%, against none on placebo. [1]
Dogs given enclomiphene for 9 months showed minimal lens swelling; eye examinations in the human trials found no conclusive evidence of new or worsening cataracts, and the European committee asked for ongoing eye monitoring. The Clomid label says to stop and have a prompt eye examination for any visual symptom, and warns that effects can be permanent; a case report describes sudden vision loss in a man taking clomiphene 100 mg daily. [1], [4], [50]
Can it affect the liver?
The British statement lists liver disease as a reason not to use it, as the Clomid label does for clomiphene. In the dog studies, deaths at high doses were due to liver toxicity. The trials published no liver-enzyme results that could be read for this guide, and a case report describes liver injury in a 31-year-old man after five days of clomiphene. [3], [4], [1], [51]
Moderate liver impairment also raised enclomiphene levels, and severe impairment was not studied. [1]
What about the prostate and PSA?
PSA (prostate-specific antigen, a prostate blood test) rose about as often on enclomiphene as on testosterone gel, and slightly more often than on placebo, with no sign of a dose effect. No prostate cancers were reported during the trials; one testicular cancer (seminoma) was reported as a serious event in ZA-300. [1], [2]
Is compounded or online enclomiphene the same as a tested medicine?
No product has been tested to a medicine standard, because none has been approved. US compounding pharmacies make it under an FDA interim policy, and an FDA inspection in June 2026 found one making tadalafil-plus-enclomiphene tablets on a shared press without a deactivating cleaning step (observations, not a final finding). Health Canada seized an enclomiphene-labelled product from a store in December 2025. Products sold online as "research chemicals" have contained undeclared clomiphene, according to an FDA debarment order in February 2026 and an Italian study that found undeclared drugs, including clomifene, in 30% of 13 online muscle-building products. [8], [9], [37], [38], [39]
No independent test of enclomiphene-labelled products was found (searched September 2026). A "research use only" label does not make a product legal, tested or safe to take.
Is enclomiphene legal? Is it FDA approved?
Checked September 2026. Rules differ by country and change often.
United States. Not approved. FDA did not approve the developer's application (2015), and no enclomiphene product has FDA approval. Enclomiphene citrate is in Category 1 of FDA's list of substances nominated for compounding (the list dated May 14, 2026), which means pharmacies may compound it under an interim policy while FDA evaluates it; FDA proposed in 2022 not to add it to the approved list, and its advisory committee voted 8 to 4 against (4 in favor). It is not a federally controlled substance: neither enclomiphene nor clomiphene appears on the Drug Enforcement Administration list (August 27, 2026). State rules were not checked. [2], [8], [42], [52], [53]
European Union. Refused. The committee's negative opinion on EnCyzix came on January 25, 2018, and no enclomiphene product is authorized. [7]
United Kingdom. Unlicensed; the British Society for Sexual Medicine advises use only by experienced clinicians in specialist settings, ideally within research. [3]
Canada. Health Canada states that "Enclomiphene was never approved in Canada", and no product appears in its drug database. Clomiphene has also been removed from the Canadian market for business reasons. [37], [54]
Australia. No enclomiphene entry exists in the Poisons Standard. Clomiphene is a prescription-only (Schedule 4) medicine with extra prescribing limits, and the Standard's rule that a listed substance includes every stereoisomer reads, by our interpretation, as covering enclomiphene; this is not a statement from Australia's medicines regulator. [55]
Is enclomiphene banned in sport? Does it show up on a drug test?
Yes. The World Anti-Doping Agency (WADA) bans anti-estrogens, including SERMs such as clomifene, at all times in class S4.2. Enclomiphene is not named separately, but the class covers substances "including, but not limited to" those listed, and the 2027 list keeps SERMs banned from January 1, 2027. WADA's exemption guidance for low testosterone covers testosterone or hCG, and only for an organic cause such as pituitary or testicular disease; it does not list SERMs such as enclomiphene. Low testosterone linked to age, weight or earlier steroid use does not qualify. [56], [57], [58]
How long enclomiphene itself can be detected has not been published. In a study of clomiphene 50 mg daily for 30 days, its zuclomiphene half was detectable in urine for 121 to more than 261 days; that is clomiphene, not pure enclomiphene. [59]
Who should be especially cautious?
- Men with high LH or failing testicles. It is not expected to work, and guidelines advise against raising the dose when LH is high. [21], [18]
- Men with a history of blood clots, stroke or heart rhythm problems, given the clot events in trials and the class warning for SERMs. [1], [21]
- Men with liver disease (a contraindication in the British statement) or kidney disease, which roughly doubled exposure. [3], [1]
- Men with eye problems, given the blurred-vision reports and clomiphene's label warning. [4], [1]
- Men with uncontrolled thyroid or adrenal disease, certain pituitary conditions, or an allergy to clomiphene, all contraindications in the British statement. [3]
- Men over 60. The phase 3 trials enrolled men aged 18 to 60 and the refused EU product was meant only for men up to 60, so older men are barely studied; men over 75 had slightly higher exposure, which the European review judged unlikely to matter. [1]
- Men who want children now. It keeps sperm production running in most men, but its effect on pregnancy is unknown; a semen analysis before and during treatment is the only way to know. [2]
- Women and teenagers. These guides are for men. Use in teenagers is specialist care only.
- Drug-tested athletes. Banned at all times. [56]
Can enclomiphene be taken with other medicines?
Interactions were studied only in small drug-level studies, and no official interaction rules exist. What those studies found: [1]
- CYP2D6. This liver enzyme does most of the work of breaking enclomiphene down. In three overweight men whose genes make the enzyme work poorly, peak levels were about 5 times and total exposure about 7 times higher, with no toxicity seen. The review accepted that no dose change was needed but asked for more data in these men. A computer model predicts that strong CYP2D6 blockers, such as the antidepressant paroxetine, would raise levels too; that has not been tested in people. [1], [60], [61]
- CYP3A4. Three days of 25 mg lowered levels of midazolam, a test drug broken down by this enzyme, by about 27–31%, which suggests enclomiphene can speed up the breakdown of some other medicines. [1]
- Effects on other drugs. In lab tests enclomiphene moderately blocked CYP2D6, but in 30 healthy men, three days of 25 mg had little effect on test drugs for CYP2D6 and four other enzymes, including the blood thinner warfarin. [1]
It is often combined with tadalafil, aromatase inhibitors, weight-loss medicines or TRT itself; none of those combinations has been studied. Bring a full list of everything you take, including supplements, to a pharmacist or prescriber. [9]
Is enclomiphene available, and what does it cost?
Checked September 2026.
In the US it is available only by prescription from compounding pharmacies. There is no official price because there is no approved product. Elsewhere, supply is unclear: Australia's Poisons Standard has no enclomiphene entry, and one Australian man who was prescribed it reported in January 2026 that several compounding pharmacies told him they could not supply it (one person's account, not a statement from a regulator). There is no FDA shortage listing for clomiphene. [8], [55], [62], [63]
What should be monitored while taking enclomiphene?
There is no label, so there are no official monitoring rules. The trials and guidelines point to what matters: whether testosterone and LH respond, whether sperm is kept, and the side effects seen in trials. Use this summary to prepare questions for your prescriber; it is not a personal testing plan. [1], [18]
| Why it matters | What trials and guidelines did | Tracking category |
|---|---|---|
| Testosterone response | Trials: morning testosterone at 4–6 weeks to decide the dose, then at 12–16 weeks. AUA: first check no sooner than 4 weeks after starting a SERM | Blood work; Libido; Energy Levels |
| LH (and FSH) | AUA: measure LH 4 weeks after starting if testosterone stays low, and again if the response fades | Blood work |
| Semen analysis | Trials: two samples at the start and two at the end; the only way to know about sperm | Other (semen result) |
| Estradiol | AUA: optional on SERMs; measure with breast symptoms | Blood work; Hormonal Symptoms |
| Hematocrit and PSA | Both rose in trials; FDA listed them as safety concerns | Blood work |
| Eyes | European review: ongoing eye monitoring requested; Clomid label: eye exam for any visual symptom | Other (vision symptoms) |
| Clot symptoms | Leg swelling or pain, sudden breathlessness, chest pain or stroke signs need urgent care | Other (symptoms) |
| Symptoms | The reason for treatment; no trial proved they improve | Libido; Energy Levels; Mood & Wellbeing |
The AUA also says that when testosterone levels are normal but symptoms have not improved after 3 to 6 months of testosterone therapy, it is time to discuss stopping; for enclomiphene, where symptom benefit is unproven, that review point matters even more. See TRT blood work. [18]
What do people in public communities report?
Public forums hold every kind of enclomiphene story: men who felt better within weeks, men whose numbers doubled while nothing else changed, and men who stopped because of their eyes, mood or sex drive. The accounts below come from public Reddit threads posted between September 2025 and September 2026 and are described without identifying anyone. Doses are as the posters reported them, and several used schedules no study has tested.
What do the positive reports look like?
Better energy, mood, sex drive and gym performance within weeks, usually with a large rise in testosterone. A man in his 30s on 12.5 mg daily went from 229 to 1,051 (units not stated) by his second blood test and described better sleep, sex drive and energy, but he also lost about 30 pounds over the same months. Another, on 12.5 mg daily for about 7 weeks, noticed sex drive and training improve sharply in the first couple of weeks and then settle at a level above where he started. [64], [65]
For one man recovering from leg surgery, mood was the clearest change as his testosterone rose from 429 to 1,430 ng/dL over 8 months on 12.5 mg daily; his estradiol rose too, and he planned to halve the dose. Another, who felt great on 25 mg daily, was weighing a switch to TRT because no one could tell him what years of enclomiphene would do. [66], [67]
Why do labs improve without feeling better?
It is the most common story, and it matches the trial results (symptoms). A man on 12.5 mg daily for about four months doubled his testosterone (384 to 741 ng/dL) but felt no difference in energy, and later wondered whether he was simply eating too little during heavy weight loss. Another, five weeks in with testosterone up from 496 to 889 (units not stated), had better libido only on some days. A third felt no better after two and a half months and had not repeated his blood tests, so he could not tell whether the drug had worked at all. [68], [69], [70] One man's urologist switched him to testosterone injections because his numbers had improved but he still felt unwell. [71]
Does the effect fade?
Several men describe feeling much better for a few weeks to a couple of months, then losing the benefit while their testosterone stayed high. One on 25 mg daily felt markedly better for a short period, then the benefit disappeared; his erection problem, the reason he started, never improved. Another's symptoms returned after about two months with testosterone near 948. A man on 12.5 mg daily felt great at two and a half months but tired, with lower sex drive, by three and a half, with testosterone at 1,268 and estradiol at 52 (units not stated). [72], [73], [74] The AUA advises rechecking LH when a man stops responding to a SERM; none of these posters reported doing so. [18]
What unwanted effects come up?
- Vision. A man taking 25 mg three days a week, chosen because he and his partner were trying for a baby, reported eye pressure and intermittent blurred vision, alongside very low sex drive and acne, and stopped after about seven weeks; after his first TRT injection he felt better. Another, on 12.5 mg every other day for a year and a half, described more eye floaters and pressure behind his eyes that eased during breaks. [75], [76]
- Mood and anxiety. The same man described waves of anxiety and hot flashes. Others describe feeling emotionally flat for months, or anxious and hot with a racing heart in the second week, easing when a dose was skipped. [76], [77], [78]
- Headaches, sweats and skin. Daily headaches on 25 mg; severe night sweats straight after a dose increase; and night sweats with oily skin and joint pain, with no gain in sex drive. [79], [80], [81]
- Liver tests. One man on an unusually high 44 mg three times a week, later with anastrozole, watched his AST, a liver enzyme, climb from 18 to 56 across successive tests. [82]
- Head pressure and dry eyes. One man on 6.25 mg daily developed migraines, ear pressure and dry eyes over 10 months, while his free testosterone stayed low, and moved to TRT. [83]
The trials found each of these effects in a small percentage of men (side effects).
What happens with estradiol?
Rising estradiol is a frequent worry. One man's estradiol went from 30 to 90 in nine weeks, with aches and tiredness; another's rose so far that his online service told him to see a doctor in person. [84], [85]
Adding an aromatase inhibitor to lower it did not reliably help. A man with a pituitary tumor felt worse after anastrozole was added, although his testosterone stayed high; another said an aromatase inhibitor lowered estradiol and made his sexual symptoms worse. One man went through anastrozole and then exemestane for breast symptoms and water retention, and felt his sexual function came closer to normal only when he took enclomiphene less often. [86], [87], [88] The VA does not generally recommend aromatase inhibitors (estrogen).
What do people report about fertility?
Fertility is the most common reason men choose it, and outcomes are rarely measured. One man who had spent years on TRT, then hCG, started enclomiphene 25 mg daily when he and his partner were struggling to conceive; five weeks later his partner had a positive pregnancy test. He believed the earlier hCG may have contributed, and he had no semen test. Another man stopped TRT for fertility and felt exhausted, with no sex drive or erections, two weeks into enclomiphene 25 mg daily. [89], [90]
Some men are given enclomiphene alongside TRT and told it will protect fertility or testicles, which no study supports. One developed puffy nipples two weeks into 120 mg of testosterone a week plus enclomiphene; another, on testosterone, hCG and enclomiphene, had only a home sperm test to go on. [91], [92]
What do people report about doses, schedules and supply?
Schedules vary far beyond the trials, from 6.25 mg three times a week to 50 mg capsules four days a week, offered to one man because the pharmacy stocked only that strength. Another felt better for six weeks on 25 mg three days a week; after a fourth day was added, his testosterone fell to 230 and his doctor recommended TRT. [93], [94]
Supply shapes the story too: one man whose LH and FSH fell on 6.25 mg three times a week wondered whether his product was genuine, and others bought it from online "research" sellers. [95], [96], [97]
How can you judge an enclomiphene story?
Ask: What was the dose, how often, and from what source (a pharmacy, or an online "research" seller)? Was LH low or normal before starting? When was blood drawn, and was it morning? Did symptoms change, or only the numbers, and did the change last past two or three months? What else changed at the same time, such as weight loss, diet, training, sleep, TRT, hCG or an aromatase inhibitor? Was there a semen analysis, before and after?
These selected discussions show what people experience and the questions research should answer. They are not a survey of all users, a success rate or a substitute for the trials.
How does enclomiphene compare with other options?
These are the options most often weighed against enclomiphene. Status was checked in September 2026.
| Option | What it does | How it is taken | Evidence in men | US status |
|---|---|---|---|---|
| Enclomiphene (this guide) | Blocks estrogen feedback so the pituitary sends more LH and FSH | Tablet or capsule, 12.5–25 mg daily in trials | Raises testosterone and keeps sperm in most men over up to 16 weeks; no symptom benefit shown | Not approved; compounded while FDA evaluates it [1], [8] |
| Clomiphene (Clomid) | Same mechanism; a mix of enclomiphene and zuclomiphene | Tablet; AUA lists 25–50 mg every 1–2 days | Longer use in men; 88% of long-term users reached normal testosterone in one records study | Approved for women; off-label in men [4], [18], [98] |
| Testosterone therapy | Replaces testosterone; switches off LH, FSH and sperm production | Injections, gel, oral capsules and other forms | Large trials in men with confirmed deficiency, including symptom outcomes | Approved; Schedule III [18] |
| hCG | Copies LH and acts directly on the testicles | Injection, several times a week | Raises testosterone and supports sperm production; studied alongside TRT | The only one of these FDA-approved for men, for pituitary-level low testosterone [18] |
| Tamoxifen | Another SERM, with a half-life of days | Tablet, 20 mg daily in the AUA table | Listed by the AUA as an alternative to testosterone; small studies | Approved for breast cancer; off-label for low testosterone [18] |
| Anastrozole | An aromatase inhibitor: lowers estradiol | Tablet | Small studies; the VA cites heart, belly-fat and bone concerns | Approved for breast cancer; off-label in men [6] |
No trial has compared enclomiphene with hCG or with TRT on symptoms, and none has compared any of them on pregnancies. The practical differences are whether sperm production keeps running, whether symptom benefit is proven, how the medicine is taken and whether an approved product exists. See hCG vs gonadorelin vs enclomiphene for the fertility comparison.
Common questions about enclomiphene
Is enclomiphene the same as Clomid?
No. Clomid (clomiphene) is a mix of two forms of the molecule, enclomiphene and zuclomiphene; enclomiphene is one of them on its own. Zuclomiphene lasts over a month in the body and acts partly like estrogen, while enclomiphene clears within days. Clomiphene is approved for women's fertility; enclomiphene is approved nowhere. [4], [5], [1] See enclomiphene vs clomiphene.
What is the usual dose of enclomiphene?
Every trial used 12.5 or 25 mg by mouth once a day, starting at 12.5 mg and increasing to 25 mg if morning testosterone stayed low after 4 to 6 weeks. The British Society for Sexual Medicine starts at 6.25 mg and allows up to 50 mg. There is no approved label, and every-other-day schedules have not been studied. [1], [3] See typical protocols.
Is enclomiphene better than TRT?
Neither is better across the board; they answer different needs. Enclomiphene keeps a man's own testosterone and sperm production running, but only if his pituitary works, and no trial has shown it improves symptoms. TRT reliably raises testosterone and improves sexual desire in men with confirmed deficiency, but it shuts down sperm production. [1], [18] See compare.
Why do my levels look good on enclomiphene but I feel the same?
That matches the trials: testosterone reached the normal range in most men, but no symptom score improved more than on placebo, which is why regulators refused it. Other causes of tiredness or low sex drive, such as sleep, weight change or other medicines, deserve a look with a clinician. [1], [2] See symptoms.
Can I take enclomiphene with TRT to keep my fertility?
It has not been studied, and it is unlikely to do much: enclomiphene works through the pituitary, and TRT switches the pituitary's signals off. Men who want children now are advised not to use testosterone at all, and the US infertility guideline calls the evidence for adding any medicine to TRT too limited to recommend. [34], [30] See TRT and fertility.
Does enclomiphene raise estrogen?
Yes. As testosterone rises, more is converted to estradiol, and the European review found significant rises compared with placebo. Breast enlargement was reported rarely in trials. No guideline sets an estradiol target on enclomiphene, and the VA does not generally recommend aromatase inhibitors. [1], [6] See estrogen.
Is enclomiphene a steroid? Is it legal?
No, it is not a steroid: it is a nonsteroidal SERM that works through the body's own hormone signals, and it is not a federally controlled substance in the US. It is not approved either: US pharmacies may compound it only while FDA evaluates it. It is refused in the EU, unlicensed in the UK and was never approved in Canada. It is banned in sport at all times. Checked September 2026. [3], [52], [8], [7], [37], [56] See legal status.
What happens when I stop taking enclomiphene?
Testosterone returns to its starting level within about a month, after staying raised for at least a week. Enclomiphene raises a man's own production only while he takes it. No taper has been studied, and no study has followed sperm after stopping. [19], [15] See stopping.
Glossary
Plain explanations of the medical, dosing and research terms used in this guide. Underlined terms in the text link here.
- Adverse event
- A harmful or unwanted medical event reported after someone used a treatment. A report alone does not prove the treatment caused it.
- Aromatase inhibitor
- A medicine, such as anastrozole, that blocks the enzyme that turns testosterone into estradiol. The VA does not generally recommend them for men.
- Atrial fibrillation
- An irregular, often fast heart rhythm that starts in the heart's upper chambers. It raises the risk of stroke.
- Atrial flutter
- A fast, regular heart rhythm problem in the heart's upper chambers, related to atrial fibrillation.
- Citrate (salt form)
- The form in which enclomiphene is made into capsules. The salt adds weight, so 12.5 mg of enclomiphene citrate contains about 8.5 mg of enclomiphene itself.
- Compounding
- When a pharmacy prepares a medicine itself, rather than dispensing a factory-made, approved product. Compounded drugs are not FDA-approved or tested the way approved medicines are.
- Controlled trial
- A study that compares people who receive a treatment with a similar group who do not, often receiving a placebo instead. Randomly assigning people to each group makes the comparison fairer.
- CYP2D6
- A liver enzyme that breaks down enclomiphene and many other medicines. Some people's genes make it work poorly, which raises their drug levels.
- Dose (amount each time)
- The amount given on one occasion. A protocol lists both the dose and how often it is given.
- Estradiol
- The main form of estrogen. In men it is made mostly from testosterone, so it rises when testosterone rises.
- FSH (follicle-stimulating hormone)
- A pituitary hormone that acts on the cells supporting sperm production. Enclomiphene raises it; testosterone therapy lowers it.
- Gynecomastia
- Growth of breast tissue in men, often tender at first. It is linked to a higher estrogen-to-testosterone balance.
- Half-life
- The time it takes for the level of a substance in the blood to fall by half. For enclomiphene it is about 8 to 10 hours. It is not the same as how long an effect lasts.
- Hazard ratio
- A way of comparing how often something happens in two groups over time. 1.0 means no difference; 0.96 means slightly fewer events in the first group. It is a relative measure, so read it beside the actual counts.
- Hematocrit
- The share of the blood made up of red blood cells. Raising testosterone can raise it, which is why it is checked.
- Secondary hypogonadism (hypogonadotropic hypogonadism)
- Low testosterone because the brain and pituitary send too little LH and FSH to the testicles. It can be present from birth or start later, for example with obesity. Enclomiphene was studied in this group.
- International Index of Erectile Function (IIEF)
- A standard questionnaire that scores erections, sex drive, orgasm and satisfaction. Trials use it to measure sexual symptoms.
- LH (luteinizing hormone)
- A pituitary hormone that tells the testicles to make testosterone. Enclomiphene raises it; testosterone therapy switches it off.
- Meta-analysis
- A study that pools the results of several earlier studies to get a more precise overall answer. It is only as good as the studies it combines.
- Off-label
- Use of an approved medicine for a purpose, dose or group of people not listed on its label. Enclomiphene is not approved for anything, so it is not even off-label; clomiphene in men is.
- Open-label
- A trial in which everyone, the researchers and the men taking the medicine, knows what is being given. It has no placebo group, so it cannot show whether a medicine works better than nothing.
- Pharmacokinetics
- How the body absorbs, moves, breaks down and removes a substance.
- Placebo
- A dummy treatment with no active ingredient, used as a comparison in studies.
- Primary hypogonadism
- Low testosterone because the testicles themselves do not work well, even though the pituitary sends plenty of LH and FSH. Enclomiphene is not expected to help.
- PSA (prostate-specific antigen)
- A blood test for a protein made by the prostate. It can rise when testosterone rises.
- Research use only
- A label on products sold for laboratory research. It does not mean a product is approved, tested for human use or legal to sell as a medicine.
- Semen analysis
- A lab test of a semen sample that measures sperm count, concentration, movement and shape. It is the only way to know how a medicine affects sperm.
- SERM (selective estrogen receptor modulator)
- A tablet, such as clomiphene, enclomiphene or tamoxifen, that blocks estrogen's feedback in the brain so the pituitary releases more LH and FSH.
- Stereoisomer
- One of two or more forms of a molecule with the same atoms arranged differently in space. Enclomiphene (trans) and zuclomiphene (cis) are the two stereoisomers in clomiphene.
- Titration
- Adjusting a dose in steps, usually starting lower and increasing if needed based on blood tests.
- Trial phases (phase 2, phase 3)
- The stages of testing a medicine in people. Phase 2 trials look at dose and early effects, usually in dozens to a few hundred people. Phase 3 trials are the large comparison trials that regulators expect before approval.
- TRT (testosterone replacement therapy)
- Prescribed testosterone, by injection, gel or other forms, for men with low testosterone. It switches off the brain's LH and FSH signals.
- Venous thromboembolism (VTE)
- A blood clot in a vein, usually in the leg (deep vein thrombosis), that can travel to the lungs (pulmonary embolism).
- WADA
- The World Anti-Doping Agency, which publishes the list of substances banned in sport. SERMs, including clomifene, are banned at all times.
- Weekly total
- All the amounts taken in one week, added together. For example, 12.5 mg once a day is an 87.5 mg weekly total.
- Zuclomiphene
- The other half of clomiphene. It stays in the body for over a month and acts partly like estrogen.
How this guide was researched
This guide is built from a thorough review of the sources cited throughout it: regulatory assessments and records from the United States, the European Union, Canada and Australia, clinical guidelines and position statements, published clinical trials and their registry results, and case reports. We also reviewed public online forums where men describe their own experiences with enclomiphene.
The guide cites 98 sources, including 19 regulatory documents and product records, 6 guidelines and position statements, and 31 original studies and trial records in people, plus 35 public community threads. Each type of source answers a different question. Regulators' reviews show what was tested and why it was refused. Guidelines show what clinicians are told to do. Trials and studies show what was measured, and in whom. Personal accounts show what individual people experienced. Every numbered citation links to its entry below, labeled by source type.
How this guide was made
Research and drafting were AI-assisted. Every cited source was checked against the original, and the guide was reviewed and edited by Doserly before publication. It has not had an independent clinical review, and Doserly does not currently have medical reviewers. Doserly makes a medication and health-tracking app and runs Doserly Academy, both of which are promoted in this guide. Read our editorial policy for how guides are researched, updated and corrected.
This guide is for educational purposes. It summarizes what the reviewed sources report so the research is easier to understand; it is not medical advice. For a deeper dive, or to check any point for yourself, go straight to the cited sources.
Explore the sources
These are the documents cited in this guide. Regulator reviews, guidelines, studies and personal accounts answer different questions. A source being listed does not mean every statement on its page is endorsed.
Showing 98 sources
- 01
EnCyzix (enclomifene): public assessment report, refusal (EMA/88321/2018) ↗
Regulator assessment (EU)
Full report text reviewed (tables that are images were not used).
Detail: Half-life 8–10 hours; trial protocols and titration; ZA-304/305 sperm results; ZA-003 questionnaires; 1,403 men exposed; 4 thromboembolic events on enclomiphene; eye, heart, estradiol, hematocrit and PSA findings; restoring testosterone alone judged not sufficient.
- 02
FDA briefing document, Pharmacy Compounding Advisory Committee, June 8, 2022: Tab 1, enclomiphene citrate ↗
FDA review (US)
Full section reviewed.
Detail: Half-life about 10 hours; peak 2–3 hours; exposure at 25 mg about 4.5 times that at 12.5 mg; the 2015 Complete Response Letter and 2016 advisory committee votes; trials did not show clinically meaningful improvement in symptoms; safety concerns listed.
- 03
British Society of Sexual Medicine: Position Statement for the Potential Use of Enclomiphene in the Treatment of Male Hypogonadism ↗
Position statement (UK)
Original full text reviewed.
Detail: Unlicensed in the UK; not recommended for routine use outside specialist settings; start 6.25 mg daily, rising weekly to 25 mg, up to 50 mg for an inadequate response; contraindications include liver disease; side effects headache 1.6%, hot flashes 1.1%, nausea 1.0%.
- 04
CLOMID (clomiphene citrate) tablets, USP ↗
Product label (US)
Full label reviewed.
Detail: Approved for ovulation problems in women; a mix of zuclomiphene (cis, 30–50%) and enclomiphene; no adequate studies show it works for male infertility; stop and have a prompt eye exam for visual symptoms; contraindicated in liver disease.
- 05
Single-dose pharmacokinetics of clomiphene citrate in normal volunteers ↗
Human study (pharmacokinetics)
Original abstract reviewed.
Detail: The zuclomiphene isomer was eliminated much more slowly than enclomiphene and was still detected up to a month after treatment.
- 06
Evaluation for and Management of Males with Low Testosterone: Recommendations for Use ↗
Health-system clinical recommendations
Original full text reviewed.
Detail: Enclomiphene "is sometimes used in isolation, because it has less estrogenic effect than zuclomiphene"; clomiphene case by case for fertility; aromatase inhibitors not generally recommended.
- 07
EnCyzix: refusal of the marketing authorisation for EnCyzix (enclomifene) ↗
Regulator decision (EU)
Official page reviewed.
Detail: Negative opinion of January 25, 2018: testosterone rose, but a benefit on symptoms was not shown and there is a risk of venous thromboembolism.
- 08
Bulk Drug Substances Nominated for Use in Compounding Under Section 503A of the FD&C Act (categories list) ↗
FDA compounding list (US)
Full list reviewed.
Detail: Enclomiphene citrate is in Category 1 (under evaluation), which allows 503A compounding under an interim policy; this is not approval.
- 09
FDA Form 483 inspectional observations: 503A compounding pharmacy, inspection June 8–17, 2026 ↗
FDA inspection record (US)
Full document reviewed.
Detail: Lists compounded tadalafil 8.5 mg plus enclomiphene citrate 12.5 mg tablets made on a shared press cleaned without a deactivating agent; observations, not a final agency determination.
- 10
Changes in serum testosterone after sublingual enclomiphene citrate combined with a mineral oxide delivery system: a retrospective case series of 15 men ↗
Human report (case series)
Original abstract reviewed.
Detail: Mean testosterone 347 to 805 ng/dL over 60 days on a multi-ingredient sublingual product; no comparison group, no LH, FSH or symptom data.
- 11
ZA-304 (NCT01993212) and ZA-305 (NCT01993225): enclomiphene 12.5/25 mg vs AndroGel 1.62% vs placebo, 16 weeks ↗
Trial registry record
Registry records reviewed (no posted results).
Detail: Randomized, double-blind, double-dummy design; results appear in the European assessment report and Kim 2016.
- 12
ZA-301: Phase III study of enclomiphene vs placebo in men with secondary hypogonadism (NCT01532414) ↗
Trial registry results
Posted results reviewed.
Detail: 78.8% of 113 men on enclomiphene reached an average testosterone of 300–1,040 ng/dL at 12 weeks; sperm concentration fell by half or more in 14.2% vs 2.6% on placebo.
- 13
ZA-300: open-label 26-week safety study of enclomiphene in men with secondary hypogonadism (NCT01534208) ↗
Trial registry results
Posted results reviewed.
Detail: 499 men; testosterone up 280.9 and 214.7 ng/dL; serious events included deep vein thrombosis (2), pulmonary embolism, atrial flutter and a seminoma; headache 12/207 and 23/283.
- 14
ZA-203: phase IIb enclomiphene 12.5/25 mg vs Testim vs placebo (NCT01270841) ↗
Trial registry results
Posted results reviewed.
Detail: Morning testosterone change +258.5 (12.5 mg), +197.3 (25 mg), +253.7 (Testim) and −16.9 ng/dL (placebo); lower sperm concentration reported in 8 of 33 on Testim and none on enclomiphene.
- 15
Testosterone restoration by enclomiphene citrate in men with secondary hypogonadism: pharmacodynamics and pharmacokinetics ↗
Human trial (phase 2)
Original full text reviewed.
Detail: 48 men; 6.25, 12.5 or 25 mg daily vs AndroGel for 6 weeks; drug peak 2–3 hours; effects on LH and testosterone persisted at least a week after stopping.
- 16
ZA-205: 48-week enclomiphene 12.5/25 mg vs placebo with diet and exercise (NCT02651688) ↗
Trial registry results
Posted results reviewed.
Detail: 50 obese men; testosterone +173.8, +237.2 and +43.3 ng/dL; weight −4.4, −6.2 and −14.5 kg (placebo lost significantly more: p=0.014 and 0.023, Wilcoxon rank-sum test); lean mass +3.1, +2.4 and +1.1 kg (p=0.71 and 0.45); testosterone p=0.003 for both doses; 1 heart attack and 1 ischemic stroke among 18 men on 12.5 mg, none among 17 on 25 mg or 15 on placebo.
- 17
Efficacy of clomiphene citrate versus enclomiphene citrate for male infertility treatment: a retrospective study ↗
Human report (retrospective; clinic protocol source)
Original full text reviewed.
Detail: 46 men on enclomiphene (12.5 mg daily in 30.4%, 25 mg daily in 69.6%) vs 32 on clomiphene 50 mg every other day; no significant difference between groups; median estradiol 29.5 to 67 pg/mL on enclomiphene.
- 18
Evaluation and Management of Testosterone Deficiency: AUA Guideline ↗
Clinical practice guideline
Original full text reviewed.
Detail: SERMs for men with low or low-normal LH, especially to keep fertility; measure LH 4 weeks after starting a SERM if testosterone stays low; escalate only if LH is low or normal; benefits of testosterone therapy "cannot be extrapolated" to alternative therapies.
- 19
Oral enclomiphene citrate stimulates the endogenous production of testosterone and sperm counts in men with low testosterone: comparison with testosterone gel ↗
Human trial (phase 2B)
Original abstract reviewed.
Detail: 12 men previously on topical testosterone; sperm counts 75–334 million/mL in all men on enclomiphene at 3 and 6 months; testosterone returned to pretreatment levels one month after stopping.
- 20
PubChem compound records: Enclomiphene (CID 1548953) and Enclomiphene Citrate (CID 6420009) ↗
Chemical reference database
Records reviewed.
Detail: Molecular weights 406.0 (enclomiphene) and 598.1 (enclomiphene citrate); the (E), or trans, isomer.
- 21
EAU Guidelines on Sexual and Reproductive Health: Male Hypogonadism (2026 edition) ↗
Clinical practice guideline
Original full text reviewed.
Detail: SERMs and aromatase inhibitors need an intact brain-to-testes axis and cannot work in primary hypogonadism or organic secondary hypogonadism; off-label with poor evidence; SERMs may raise the risk of blood clots (enclomiphene is not named).
- 22
ZA-204: phase II enclomiphene 6.25/12.5/25 mg vs AndroGel, 24-hour LH and testosterone (NCT01386606) ↗
Trial registry results
Posted results reviewed.
Detail: 24-hour average testosterone from baseline 262.3, 373.6 and 298.3 to 392.4, 460.8 and 586.7 ng/dL at week 6 on 6.25, 12.5 and 25 mg (AndroGel 322.4 to 543.9); analysis groups of 12, 10, 13 and 13 men in the registry (the FDA review lists 12, 7, 12 and 13); LH raised by week 2.
- 23
Clomiphene citrate in off-label post-cycle therapy: mechanisms, efficacy and diagnostic challenges in endocrine recovery following anabolic steroid use ↗
Review
Original abstract reviewed.
Detail: Enclomiphene and kisspeptin analogues suggested as future directions that "lack validation" after anabolic steroid use.
- 24
European Academy of Andrology (EAA) guidelines on investigation, treatment and monitoring of functional hypogonadism in males ↗
Clinical practice guideline
Original full text reviewed.
Detail: Anti-estrogens (clomiphene, tamoxifen, enclomiphene) and aromatase inhibitors suggested off-label; "the available evidence is poor".
- 25
Clomiphene or enclomiphene citrate for the treatment of male hypogonadism: a systematic review and meta-analysis of randomized controlled trials ↗
Systematic review and meta-analysis
Original abstract reviewed.
Detail: Total testosterone up 273.76 ng/dL vs placebo, with LH and FSH rising; similar to testosterone gel.
- 26
Selective modulation of estrogen receptor in obese men with androgen deficiency: a systematic review and meta-analysis ↗
Systematic review and meta-analysis
Original abstract reviewed.
Detail: Seven studies, 292 obese men; enclomiphene 12.5–25 mg daily raised testosterone by 7.50 nmol/L (95% CI 6.52 to 8.48) from baseline.
- 27
Oral enclomiphene citrate raises testosterone and preserves sperm counts in obese hypogonadal men, unlike topical testosterone: restoration instead of replacement ↗
Human trial (phase 3)
Original abstract reviewed.
Detail: Two 16-week trials in overweight men 18–60: testosterone, LH and FSH rose on enclomiphene; sperm concentration kept in the normal range; testosterone gel markedly reduced sperm production.
- 28
Clomiphene citrate versus testosterone replacement therapy in male hypogonadism: a systematic review of literature and meta-analysis ↗
Systematic review and meta-analysis
Original abstract reviewed.
Detail: Clomiphene raised testosterone about as much as testosterone gel, but libido improved less than on TRT.
- 29
Effect of oestrogen modulation on semen parameters in men with secondary hypogonadism: systematic review and meta-analysis ↗
Systematic review and meta-analysis
Original abstract reviewed.
Detail: Heterogeneous effects of SERMs on sperm concentration in randomized trials; limited pregnancy or live-birth data.
- 30
Diagnosis and Treatment of Infertility in Men: AUA/ASRM Guideline (2020; amended 2024) ↗
Clinical practice guideline
Original full text reviewed.
Detail: Aromatase inhibitors, hCG, SERMs or a combination may be used for infertile men with low testosterone (conditional, Grade C); only hCG is FDA-approved in men; no testosterone for men interested in fertility; evidence for adding medicines to testosterone too limited to recommend.
- 31
ZA-201: phase IIB fertility study, enclomiphene 25 mg vs Testim in men previously on topical testosterone (NCT00706719) ↗
Trial registry results
Posted results reviewed.
Detail: Sperm concentration 182.6 million/mL at month 3 on enclomiphene vs 3.00 on Testim; groups of 5–7 men.
- 32
Age and duration of testosterone therapy predict time to return of sperm count after human chorionic gonadotropin therapy ↗
Human report
Original abstract reviewed.
Detail: 66 men with infertility after testosterone treated with hCG plus a SERM; 70% reached a total motile count above 5 million within 12 months.
- 33
Newly detected atrial flutter after enclomiphene dose escalation in a patient with prior mitral valve repair and chronic immune thrombocytopenia: a case report ↗
Human report (case report)
Original abstract reviewed.
Detail: Atrial flutter found after an accidental increase from 25 mg to 50 mg daily; causality rated "possible" only.
- 34
ClinicalTrials.gov search: enclomiphene (Androxal) program records ↗
Trial registry search
Structured data reviewed.
Detail: Age, kidney, drug-interaction, heart-rhythm and one-year extension studies registered without posted results; no trial outside the developer's program and none of enclomiphene added to TRT.
- 35
Safety and efficacy of enclomiphene and clomiphene for hypogonadal men ↗
Human report (retrospective)
Original full text reviewed.
Detail: 66 men switched from clomiphene to enclomiphene with no washout: median testosterone change 166 vs 98 ng/dL (not significant); estradiol −5.92 vs +17.50 pg/mL; side effects 13.8% vs 47%; no doses recorded.
- 36
Serum levels of enclomiphene and zuclomiphene in men with hypogonadism on long-term clomiphene citrate treatment ↗
Human report
Original abstract reviewed.
Detail: 15 men on clomiphene for at least 6 weeks: median zuclomiphene to enclomiphene ratio 20:1.
- 37
Unauthorized health products seized from two stores in Maple Ridge, BC may pose serious health risks (advisory RA-81404) ↗
Regulator advisory (Canada)
Full advisory reviewed.
Detail: "Enclomiphene was never approved in Canada"; the risks of clomiphene also apply to enclomiphene; clomiphene removed from the Canadian market for business reasons.
- 38
Final debarment order (Federal Register document 2026-02786) ↗
FDA enforcement record (US)
Full document reviewed.
Detail: Products sold online contained an undeclared drug, clomiphene, alongside ostarine.
- 39
Illegal products containing selective androgen receptor modulators purchased online from Italy: health risks for consumers ↗
Product analysis study
Original abstract reviewed.
Detail: 13 products sold online "for research only"; undeclared drugs, including clomifene, in 30% of samples.
- 40
ZA-302: Phase III study of enclomiphene vs placebo in overweight men with secondary hypogonadism (NCT01739595) ↗
Trial registry results
Posted results reviewed.
Detail: 81.3% of 134 men on enclomiphene reached the normal range at 12 weeks; sperm concentration fell by half or more in 14.2% vs 4.3% on placebo.
- 41
Enclomiphene citrate stimulates testosterone production while preventing oligospermia: a randomized phase II clinical trial comparing topical testosterone ↗
Human trial (phase 2)
Original abstract reviewed.
Detail: Testosterone rose as with a topical gel while LH and FSH rose and sperm counts were kept.
- 42
Pharmacy Compounding Advisory Committee meeting transcript, June 8, 2022 ↗
Advisory committee record (US)
Transcript reviewed.
Detail: The committee voted 8 to 4 against placing enclomiphene citrate on the 503A bulks list (8 no, 4 yes); FDA had proposed not listing it.
- 43
Pulmonary embolism as a rare complication of clomiphene therapy: a case report and literature review ↗
Human report (case report)
Original abstract reviewed.
Detail: A 56-year-old man on clomiphene for two years for hypogonadism developed a large pulmonary embolism.
- 44
Intracranial venous thrombosis in a man taking clomiphene citrate ↗
Human report (case report)
Original abstract reviewed.
Detail: A clot in the brain's veins three weeks after starting clomiphene for infertility.
- 45
Clomiphene-induced portal vein thrombosis and superior mesenteric venous thrombosis ↗
Human report (case report)
Original abstract reviewed.
Detail: A 32-year-old man developed clots in the gut veins after three months of clomiphene; clomiphene judged a possible provoking factor.
- 46
Clomiphene-induced myocardial infarction in a young male: a case report of a rare cardiovascular complication ↗
Human report (case report)
Original abstract reviewed.
Detail: A man in his early 30s with no known risk factors had a heart attack caused by a clot while taking clomiphene.
- 47
Demographics, usage patterns, and safety of male users of clomiphene in the United States ↗
Human report (claims database)
Original abstract reviewed.
Detail: 12,318 men prescribed clomiphene, median use 3.6 months; no increased risk of the side effects tracked, including clots, vision problems and liver disease.
- 48
Cardiovascular Safety of Testosterone-Replacement Therapy ↗
Human trial (phase 4)
Original abstract reviewed.
Detail: TRAVERSE: about 5,200 men aged 45–80 with heart disease or high heart risk on daily testosterone gel or placebo gel; heart attack, stroke or heart death in 182 of 2,596 (7.0%) vs 190 of 2,602 (7.3%), hazard ratio 0.96 (95% CI 0.78 to 1.17); gel only; average treatment 21.7 months. Not a trial of enclomiphene.
- 49
KYZATREX (testosterone undecanoate) capsules, prescribing information, section 5 and 6.1 (TRAVERSE class text) ↗
Product label (US)
Full label reviewed.
Detail: Class labeling with TRAVERSE results: atrial fibrillation 3.5% vs 2.4%, acute kidney injury 2.3% vs 1.5%, pulmonary embolism 0.9% vs 0.5%; about 61% stopped the study gel.
- 50
Presumed clomiphene-induced optic neuropathy: a case report ↗
Human report (case report)
Original abstract reviewed.
Detail: A 33-year-old man lost vision in one eye after two weeks of clomiphene 100 mg daily.
- 51
Liver injury induced by clomiphene citrate: a case report and literature reviews ↗
Human report (case report)
Original abstract reviewed.
Detail: A 31-year-old man developed liver injury and cholecystitis after five days of clomiphene; liver enzymes normalized after stopping.
- 52
Controlled Substances: Alphabetical Order ↗
Regulatory list (US)
Full list searched.
Detail: No entry for clomiphene, clomifene or enclomiphene (federal list only).
- 53
Clomiphene citrate tablets, USP (generic) prescribing information ↗
Product label (US)
Full label reviewed.
Detail: "DEA Schedule: None"; drug interactions "have not been documented".
- 54
Drug Product Database: active-ingredient search for enclomiphene and enclomifene ↗
Regulatory database (Canada)
Structured data searched.
Detail: No product found under either spelling, at any status. A negative search, not a Health Canada statement.
- 55
Therapeutic Goods (Poisons Standard—June 2026) Instrument 2026 ↗
Regulation (Australia)
Original text reviewed.
Detail: No enclomiphene entry; clomifene is Schedule 4 with an Appendix D condition; a listed substance includes every stereoisomer.
- 56
World Anti-Doping Code International Standard: Prohibited List 2026 ↗
Anti-doping rule
Full list reviewed.
Detail: S4.2 anti-estrogenic substances, including clomifene, tamoxifen and raloxifene, prohibited at all times; the class is "including, but not limited to" the named examples.
- 57
World Anti-Doping Code International Standard: Prohibited List 2027 ↗
Anti-doping rule
Full list reviewed.
Detail: Keeps SERMs, including clomifene, prohibited at all times from January 1, 2027.
- 58
TUE Physician Guidelines: Male Hypogonadism, Version 9 ↗
Anti-doping guidance
Full document reviewed.
Detail: The guidance covers treatment with testosterone or hCG only (no SERM is listed) and grants an exemption only for organic hypogonadism, not for functional low testosterone such as age, obesity or earlier anabolic steroid use.
- 59
Hypothalamic-pituitary-testicular axis effects and urinary detection following clomiphene administration in males ↗
Human study
Original abstract reviewed.
Detail: 12 healthy men on clomiphene 50 mg daily for 30 days; zuclomiphene detectable in urine for 121 to more than 261 days.
- 60
CYP2D6 is primarily responsible for the metabolism of clomiphene ↗
Cell study (human liver tissue)
Original abstract reviewed.
Detail: In human liver microsomes, CYP2D6 was primarily responsible for enclomiphene metabolism.
- 61
Prediction of drug-drug-gene interaction scenarios of (E)-clomiphene and its metabolites using physiologically based pharmacokinetic modeling ↗
Modeling study
Original abstract reviewed.
Detail: (E)-clomiphene (enclomiphene) is eliminated mainly through CYP2D6 and CYP3A4; the model predicts effects of CYP2D6 variants and inhibitors such as paroxetine.
- 62
Compounding Chemists in Australia for Enclomiphene? Nowhere stocks it! ↗
Community account
Public thread reviewed: opening post and 14 comments.
Detail: The poster was prescribed enclomiphene for low libido and energy but had not started it.
- 63
openFDA Drug Shortages dataset ↗
Government data (US)
Structured data reviewed.
Detail: No shortage record for clomiphene or any testosterone product.
- 64
Enclomiphene changed my life - Results April to mid June ↗
Community account
Public thread reviewed: opening post and 5 comments.
Detail: The poster, in his 30s, began enclomiphene after fatigue, daytime naps, poor sleep, weight gain, and reduced interest in exercise.
- 65
Enclo experiment update ↗
Community account
Public thread reviewed: opening post and 1 comments.
Detail: The poster took enclomiphene daily and compared baseline labs with results after about seven weeks.
- 66
Enclomiphene *HYPER RESPONDER* 12.5mg qd 8 month results + questions ↗
Community account
Public thread reviewed: opening post and 18 comments.
Detail: The poster took enclomiphene through recovery from major leg surgery.
- 67
Enclomiphene before and after (bloods only) ↗
Community account
Public thread reviewed: opening post and 0 comments.
Detail: The poster started enclomiphene 25 mg daily through a clinic after total testosterone measured 271.
- 68
I think I made a mistake taking enclomiphene ↗
Community account
Public thread reviewed: opening post and 29 comments.
Detail: The poster started enclomiphene after a low testosterone result while losing substantial weight.
- 69
Started enclomiphene, but still feel 'meh' most of the time. ↗
Community account
Public thread reviewed: opening post and 0 comments.
Detail: The poster started enclomiphene after months of reduced libido and weaker erectile responsiveness.
- 70
Is TRT the right next step if enclomiphene hasn’t improved my symptoms? ↗
Community account
Public thread reviewed: opening post and 2 comments.
Detail: The poster took enclomiphene daily for about two and a half months for fatigue, brain fog, and low energy.
- 71
Off Enclomiphene, started on T, fertility question ↗
Community account
Public thread reviewed: opening post and 2 comments.
Detail: The poster took enclomiphene for low testosterone symptoms while hoping to preserve fertility.
- 72
Very good results with enclomiphene but the benefits have disapered almost overnight ↗
Community account
Public thread reviewed: opening post and 18 comments.
Detail: The poster took enclomiphene 25 mg daily for about two months, initially seeking help with erectile difficulty.
- 73
Switching from enclomiphene to TRT? ↗
Community account
Public thread reviewed: opening post and 6 comments.
Detail: The poster began enclomiphene after years of low testosterone and initially reported better mood, energy, strength, libido, and erections.
- 74
Enclomiphene 3.5 month update. ↗
Community account
Public thread reviewed: opening post and 6 comments.
Detail: The poster took enclomiphene 12.5 mg daily for 3.5 months.
- 75
My Enclo Experience ↗
Community account
Public thread reviewed: opening post and 15 comments.
Detail: The poster chose enclomiphene because he and his partner were trying to start a family and wanted to avoid the fertility risk of TRT.
- 76
My Mostly Good (But Occasionally Terrifying) Enclomiphene Experience ↗
Community account
Public thread reviewed: opening post and 7 comments.
Detail: The poster used enclomiphene for about a year and a half and reported better workouts, recovery, confidence and mood when it felt effective.
- 77
Enclomiphene from September of 2025 - not worth it ↗
Community account
Public thread reviewed: opening post and 5 comments.
Detail: The poster took enclomiphene 12.5 mg for about five months, increased to 25 mg, then reduced the dose.
- 78
Recently started Enclomiphine - feeling off from it ↗
Community account
Public thread reviewed: opening post and 41 comments.
Detail: The poster started enclomiphene after previously receiving testosterone injections.
- 79
enclomiphene vs TRT results ↗
Community account
Public thread reviewed: opening post and 33 comments.
Detail: The poster used enclomiphene for fatigue, brain fog, poor sleep, and weak workouts.
- 80
34M Severe ED and Zero Libido After Weight Loss and Enclomiphene. Need Protocol Advice. ↗
Community account
Public thread reviewed: opening post and 4 comments.
Detail: The poster tried daily enclomiphene after low free testosterone and severe libido concerns.
- 81
Enclomiphene not working... Or not enough? ↗
Community account
Public thread reviewed: opening post and 4 comments.
Detail: The poster started enclomiphene 12.5 mg every other day for low libido and low testosterone.
- 82
steady AST increase on enclo ↗
Community account
Public thread reviewed: opening post and 1 comments.
Detail: The poster took enclomiphene 44 mg three times weekly after gradually increasing to that dose.
- 83
Stopping enclo to start TRT-What to expect ↗
Community account
Public thread reviewed: opening post and 4 comments.
Detail: The poster had fatigue, low libido, and sleep problems despite raising total testosterone through lifestyle changes.
- 84
Enclomiphene/ High Estrogen ↗
Community account
Public thread reviewed: opening post and 6 comments.
Detail: The poster took enclomiphene 12.5 mg daily for nine weeks.
- 85
Enclomiphene raised my E2 to the roof, any other options? ↗
Community account
Public thread reviewed: opening post and 1 comments.
Detail: The poster sought treatment for fatigue, difficulty gaining muscle, and difficulty managing body fat.
- 86
Enclomiphene Use - Secondary Hypogonadism ↗
Community account
Public thread reviewed: opening post and 6 comments.
Detail: The poster had low testosterone and a pituitary tumor, then started enclomiphene 25 mg every other day.
- 87
Enclomiphene libido and/or erectile dysfunction thoughts. ↗
Community account
Public thread reviewed: opening post and 5 comments.
Detail: The poster described secondary low testosterone associated with shift work and reflected on libido problems during enclomiphene use.
- 88
Enclomiphene, high E2, ED issues. ↗
Community account
Public thread reviewed: opening post and 2 comments.
Detail: The poster started enclomiphene after erectile problems that began while he was using finasteride.
- 89
TRT, HCG, Enclomiphene and Fertility ↗
Community account
Public thread reviewed: opening post and 11 comments.
Detail: The poster had used TRT for years without a fertility regimen, then began hCG and tapered TRT when he and his partner wanted another child.
- 90
Off TRT - Enclomiphene 25mg - Feeling Rough ↗
Community account
Public thread reviewed: opening post and 1 comments.
Detail: The poster stopped TRT after about a year because he wanted to prepare for having children, continued hCG briefly, then started enclomiphene.
- 91
Started 120mg test c, and enclomiphene 2 weeks ago noticed puffy nips this week ↗
Community account
Public thread reviewed: opening post and 30 comments.
Detail: The poster started testosterone injections at 120 mg per week with enclomiphene three times weekly, then noticed puffy nipples during the second week.
- 92
Anyone try adding enclomiphene to their trt protocol for fertility boost(trying to conceive) and notice MAJOR positive effects? ↗
Community account
Public thread reviewed: opening post and 37 comments.
Detail: The poster added enclomiphene to testosterone and hCG while trying to conceive and reported much better sleep, energy, mood, appearance, and ejaculate volume.
- 93
Enclomiphene 50mg doses? ↗
Community account
Public thread reviewed: opening post and 8 comments.
Detail: The poster had not started treatment but said a provider proposed enclomiphene capsules at a dose and schedule he considered unusually high.
- 94
Enclomiphene results ↗
Community account
Public thread reviewed: opening post and 2 comments.
Detail: The poster started enclomiphene after low testosterone results and felt more focused and generally better after about six weeks.
- 95
44M - Secondary Hypo for 6 years. 2 Months on Enclomiphene (6.25mg 3x/week) LH/FSH tanked, Zero Libido. Bloodwork included. ↗
Community account
Public thread reviewed: opening post and 6 comments.
Detail: The poster had longstanding low testosterone and previously stopped clomiphene after poor libido and eye problems despite higher testosterone labs.
- 96
Enclomiphene Before and After Results! (not bad!) ↗
Community account
Public thread reviewed: opening post and 10 comments.
Detail: The poster used enclomiphene several nights per week and repeated labs after nearly seven weeks.
- 97
Trt feeling bad, but enclomiphene was great. ↗
Community account
Public thread reviewed: opening post and 17 comments.
Detail: The poster started enclomiphene from an online peptide seller after low testosterone results and uncertainty about thyroid problems.
- 98
Long-term safety and efficacy of clomiphene citrate for the treatment of hypogonadism ↗
Human report (retrospective)
Original abstract reviewed.
Detail: 400 men on clomiphene; of 120 treated for more than 3 years, 88% reached normal testosterone and 8% reported side effects.
No matching sources
Try a different term or show the full list.
Updates and corrections
Updated September 29, 2026. This version replaces the earlier enclomiphene guide with a rewrite based on the European Medicines Agency's full assessment report, FDA's 2022 compounding review, the trial registry results and current guidelines. It adds a protocol table with each schedule's source, the regulators' reasons for refusing it, the sperm results in full (including the trials where sperm fell), side-effect rates from the pooled trials, what happens when it stops, a dated legal-status summary and a comparison with related options. It corrects the earlier page on several points: blood clots were more common on enclomiphene than on testosterone in the trials, not similar; the half-life is 8 to 10 hours in the European review; zuclomiphene makes up 30–50% of clomiphene, not a fixed 62%; the sperm percentages quoted from a review are replaced by the regulator's figures; data exist beyond 6 months (48-week and one-year records); and failing testicles make it unlikely to work rather than being a formal contraindication. Every-other-day and cycling schedules, aromatase inhibitor add-on doses, storage and missed-dose rules, and claims that it avoids a post-treatment crash or keeps testicle size were removed because no source supports them. The date describes this revision, not a fresh check of every source.
Found an error or a relevant study we missed? Report a correction with the guide title, the specific passage and a supporting source if available. Please leave out personal health records. See our editorial policy for how we handle attribution, evidence limits and corrections.