
In this guide
What is dydrogesterone?
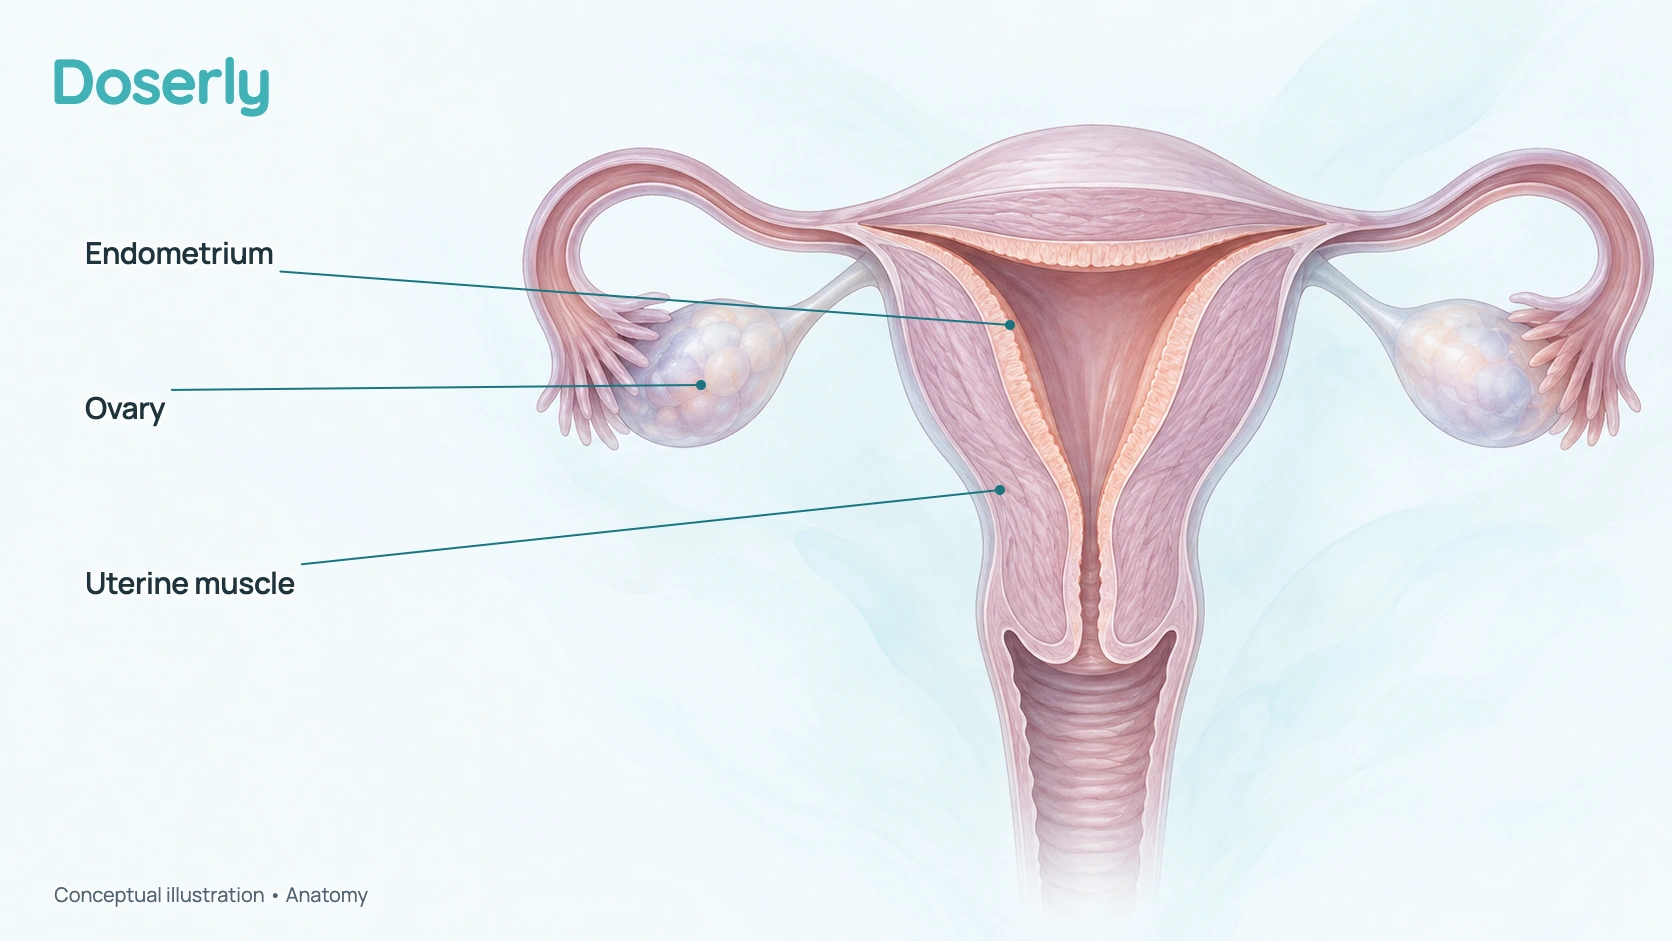
Dydrogesterone is an oral prescription progestogen, a medicine that acts at progesterone receptors. In menopausal hormone replacement therapy (HRT), its main role is opposing systemic estrogen’s stimulation of the endometrium, the lining inside the uterus. It can be prescribed as a separate tablet with estrogen or supplied in a fixed estrogen/dydrogesterone product. [1], [2], [3], [10]
It is a synthetic molecule related to progesterone, not micronized progesterone in another brand. Its milligram amounts, metabolism and evidence differ. A 10 mg dydrogesterone tablet cannot be compared by mass with a 100 mg progesterone capsule. Nor does “progesterone-like” mean that a product is identical to the body’s hormone or automatically better tolerated. [1], [4], [16]
The most useful opening question is the complete prescription: which estrogen, which dydrogesterone product, and which days? A sequential 10 mg tablet, a continuously combined 5 mg tablet and a lower-dose experimental combination answer different questions. They should not be merged into a single “usual dose.” [1], [3], [8], [10]
Typical Dydrogesterone Protocols
| Product and population | Amount each time | Schedule and total | Context and source |
|---|---|---|---|
| UK Nalvee, estrogen-treated menopause with uterus | Dydrogesterone 10 mg orally once daily | Continuous estrogen; dydrogesterone last 14 days of each 28-day cycle | Continuous-sequential label regimen; 14 doses per cycle, not every day [1] |
| UK Nalvee, cyclic estrogen course | Dydrogesterone 10 mg orally once daily | Estrogen 21 days, 7 off; dydrogesterone last 12–14 estrogen days | Cyclic label option; not last 14 calendar days including estrogen-off week [1] |
| Ireland Duphaston, HRT with estrogen | Dydrogesterone 10 mg orally once daily | Last 14 days of each 28-day estrogen cycle | Labeled adjustment to 10 mg twice daily for described clinical/tissue response; not automatic [2] |
| UK Femoston 1/10, sequential combination | One oral tablet: E2 1 mg first; E2 1 mg + dydrogesterone 10 mg second | First 14 days estrogen-only tablets; next 14 combined; next pack immediately | One tablet daily throughout; no seven-day pack break [3] |
| UK Femoston-conti 1/5, continuous combination | One oral tablet: E2 1 mg + dydrogesterone 5 mg | Every day without a break; both hormones daily | Natural menopause at least 12 months after last period; surgical menopause can start immediately [10] |
The ordinary pattern is a source-defined estrogen/progestogen pair, with either selected progestogen days or both hormones daily. Nalvee allows adjustment to 20 mg/day; its multiple doses are spread across the day. Duphaston describes 10 mg twice daily for early withdrawal bleeding or inadequate tissue response. These adjustments remain attached to the reviewed label and clinical assessment, not a universal escalation. Follow up at three months, then annually or earlier for trouble. Oral means swallowed; a 28-day cycle and a calendar month are different. The table separates labeled schedules from broader high-estrogen guidance. [1], [2], [4], [6]
Where these schedules come from
Rows 1–2: Nalvee SmPC sections 4.1–4.2, updated 17 August 2026. Row 3: Duphaston Irish SmPC section 4.2, September 2025. Row 4: Femoston 1/10 section 4.2, current May 2025 text. Row 5: Femoston-conti 1/5 section 4.1–4.2, current May 2025 text. Current contraindications in section 4.3 accompany each regimen. These are exact products; lower experimental combination arms remain evidence only. [1], [2], [3], [10]
What is it used for in menopause?
When systemic estrogen is used with a uterus present, adequate progestogen exposure is generally needed to limit lining overgrowth. Dydrogesterone supplies that part of the regimen in its labeled products. The estrogen-containing combination can relieve vasomotor symptoms, meaning hot flashes and night sweats. Improvement in those symptoms is evidence for the pair, not proof that dydrogesterone alone treats them. [1], [3], [8], [10]
Nalvee and Duphaston also list nonmenopausal indications linked to progesterone insufficiency, with separate schedules. A bleeding, fertility or gynecologic prescription must not be copied into a menopause protection calendar. None of the HRT rows above promises contraception. In perimenopause, changing periods and continuing pregnancy possibility need a separate contraceptive discussion. [1], [2], [4]
For isolated vaginal dryness, painful sex or urinary/vulvovaginal symptoms, a systemic fixed combination is not automatically the most appropriate treatment. NICE discusses local vaginal estrogen separately. Treatment selection considers the actual symptom goal, uterine status, contraindications and preferences instead of adding a systemic progestogen because another person’s prescription included one. [6]
How do sequential and continuous products differ?
Sequential means the progestogen is taken for selected days, usually with a planned withdrawal bleed afterward. Continuous combined means both hormones every day, generally aiming eventually for no bleeding. These patterns use different products and populations. Femoston 1/10 has estrogen-only tablets first and combined tablets second; Femoston-conti 1/5 has the same hormone pair in every daily tablet. [3], [10]
“Continuous sequential” can sound contradictory: in the Nalvee label, estrogen continues while dydrogesterone is added for the last 14 days of each 28-day cycle. The alternative cyclic-estrogen regimen includes 21 estrogen days followed by seven off-days, with dydrogesterone confined to the last 12–14 estrogen days. Taking it in the estrogen-off week would change that complete source schedule. A calendar month also is not always 28 days. [1]
The label permits adjustments based on the described response, and BMS stresses matching progestogen exposure to estrogen dose. This is a clinician’s assessment, including bleeding and sometimes tissue information. It is not a fixed online escalation ladder or permission to use continuous 5 mg separate tablets because a fixed combination contains that amount. Higher-estrogen regimens retain their off-label/evidence qualifications. [1], [2], [4], [5]
Two fixed packs, different exposure
One oral tablet every day. Start the next pack immediately after day 28; no seven-day break.
Femoston 1/10
E2 1 mg all days; add dydrogesterone 10 mg days 15–28 [3]
Femoston-conti 1/5
E2 1 mg + dydrogesterone 5 mg every day [10]
UK labels. Femoston-conti after natural menopause: at least 12 months since last period; surgical menopause can start immediately. Separate Nalvee/Duphaston calendars are not pictured.
How are the tablets taken?
These reviewed products are swallowed. Their oral evidence should not become a vaginal insertion, compounded cream or patch protocol. Take the prescribed tablet at a consistent time; Nalvee says doses should be spread through the day when more than one tablet is used. A twice-daily adjustment therefore is not automatically two tablets together at bedtime. [1], [2]
The Nalvee and Duphaston score line is only to facilitate breaking for easier swallowing, not to divide the tablet into equal doses. A public account of using half a 10 mg tablet does not establish an authorized 5 mg preparation or reliable endometrial protection. The fixed 5 mg Femoston-conti tablet also contains estrogen, so it is not a replacement for a separate half-tablet plan. [1], [2], [10]
If a dose is missed, follow the specific product leaflet and pharmacist’s instructions rather than inventing a doubled dose or extending the course. Keep the prescribed estrogen and progestogen days visible. With a fixed pack, taking the wrong tablet order changes which hormone exposure is supplied. [1], [3], [10]
How should the product be stored?
Nalvee’s current SmPC says there are no special storage conditions. That does not remove the expiry or justify storing any medicine in heat, damp or an unmarked container. Duphaston and the fixed combinations retain their own pack/storage instructions; do not transfer the standalone instruction to every brand. Keep the product identified and away from children. [1], [2], [3], [10]
Before a refill or shortage substitution, confirm whether estrogen is supplied separately or inside the pack. If only the progestogen runs out while systemic estrogen continues with a uterus present, contact the prescriber or pharmacist about maintaining the protection plan. Matching “10 mg” on another molecule does not create an equivalent replacement. [4]
What does the human research show?
A 2010 randomized trial included 313 postmenopausal participants with at least 50 moderate-to-severe hot flushes per week. For 13 weeks it compared estradiol 0.5 mg/dydrogesterone 2.5 mg, estradiol 1 mg/dydrogesterone 5 mg and placebo. Mean daily hot-flush reductions were 6.4, 6.3 and 4.9 respectively. These are changes in symptoms with combinations, not individual response rates or evidence that dydrogesterone alone was effective. [8]
The placebo group later switched treatment for the subsequent follow-up. Later bleeding outcomes therefore must not be described as a full-year placebo comparison. The early vasomotor result is useful, while the trial size and duration cannot settle rare adverse events, breast-cancer comparisons or whether a separate tablet/patch pair provides equal protection. [8]
A 2024 post hoc report pooled two phase III trials, with 579 participants: 288 assigned the 0.5/2.5 combination and 291 placebo. It supports symptom benefit in those 12- or 13-week comparisons. Pooling previously studied participants is not an independent new randomized trial, and statistical symptom benefit does not establish long-term safety. [9]
In the observational French E3N cohort, breast-cancer associations differed across estrogen/progestogen combinations. NICE’s current conclusion remains that evidence is insufficient to establish whether progesterone or dydrogesterone differs from other progestogens in the increase in breast risk. Observational findings can inform counseling without proving this molecule is breast-safe or superior for every patient. [6], [11]
Fewer hot flushes per day
Mean reductions at 13 weeks. Overall n=313 postmenopausal participants with at least 50 moderate/severe flushes per week; randomized combination trial, 2010. [8]
Larger reduction means greater average symptom improvement. The placebo group later changed treatment. These are not response rates, dydrogesterone-alone results or long-term safety estimates.
How does it differ from ovarian progesterone?
Dydrogesterone is structurally related to progesterone but is a distinct synthetic compound. Its progestogen activity changes the estrogen-stimulated lining toward secretory development. The body processes it into active metabolites, including dihydrodydrogesterone. Chemistry helps explain why oral amounts differ; it does not turn the molecule into micronized progesterone. [1], [2], [16]
Progesterone sleep findings involving neuroactive metabolites must not simply be copied to dydrogesterone. A person reporting less grogginess may still have nausea, headache or mood difficulty; someone whose night sweats improve may sleep better for that reason. The product’s symptom goals and unwanted effects are evaluated separately. [1], [8], [12]
Which warnings need a product-specific discussion?
Headache/migraine, nausea, breast symptoms and changes in bleeding are listed tolerability concerns; mood effects and dizziness also warrant review. A predictable withdrawal bleed is different from unexplained, persistent or heavy bleeding. Do not use a reassuring forum account to exclude an underlying cause or to override the current leaflet. [1], [2], [7]
Current Nalvee and the reviewed Femoston labels contraindicate use in people with meningioma or a history of it. Meningioma is a tumor of membranes around the brain and spinal cord. The Nalvee label reports these tumors with dydrogesterone and says to stop dydrogesterone-containing treatment if diagnosed. New progressive headache, vision/hearing changes, loss of smell, seizures or weakness need medical assessment. These restrictions should be checked on the exact current regional product. [1], [3], [10], [14]
A 2024 French case-control study did not find excess meningioma association with dydrogesterone. That finding is not a zero-risk guarantee and does not cancel a subsequently updated contraindication. It also does not provide a personal incidence estimate. The molecule-specific label and regulator assessment remain relevant rather than assuming every synthetic progestogen has the same restriction. [1], [14], [15]
Contraindications also include unexplained bleeding, relevant hormone-dependent tumors and certain liver or clotting conditions, depending on the product. When estrogen is combined, its restrictions also apply. Sudden chest pain, breathlessness, one-sided weakness, serious visual changes, jaundice or suspected severe allergy require prompt assessment. Bring the complete medicine and supplement list: metabolism-inducing medicines and some herbal products can reduce effectiveness. [1], [2], [3], [10]
No general claim of negligible clot or breast risk follows from an oral molecule’s selectivity or a favorable observational comparison. The fixed combination’s estrogen dose/route, age, personal history and treatment duration remain part of the discussion. Review troublesome mood or daily-function effects early; a mandatory “three-month adjustment” is not a rule for enduring severe symptoms. [6]
What do the brand and country change?
Nalvee, Duphaston and Femoston do not describe one interchangeable pack. The UK and Irish labels reviewed here provide specific examples; they do not certify US, Canadian or Australian approval, reimbursement or stock. An updated online SmPC date is also not a new approval date or proof of current pharmacy supply. [1], [2], [3], [10]
At a cross-border refill, confirm the full ingredients and whether the pack is sequential or continuous. “Femoston” without its strength and suffix loses essential information. If substituting a separate estrogen and progestogen, the prescriber needs a complete source-supported calendar and estrogen amount, not simply the familiar trade name. Do not import medicines from an unverified source to resolve a dose question.
What do public experiences help explain?
A public perimenopause discussion includes little noticeable benefit early in a dydrogesterone course, better cycle regularity in another account, and differences in grogginess or mood compared with progesterone. These are varied experiences, not a trial of the same estrogen/progestogen pair. They help identify questions about timing, mood and the intended purpose rather than establish superiority. [12]
A public Femoston-conti discussion reports initial improvement followed by returning low mood or anxiety, with life events and product changes complicating the explanation. That matters clinically: a later change is not automatically a progestogen effect, and an early favorable response does not guarantee continued benefit. The thread is from 2017, rechecked for this guide; it is not presented as current prescribing policy. [13]
Only public material was reviewed. Selected accounts cannot supply a response rate, a safe tablet fraction or a predictable adaptation deadline. Keep both favorable and unwanted outcomes visible, without usernames or identifiable histories. A useful follow-up records the exact combination, dose days, bleeding, mood and what else changed. [12], [13]
What should be monitored?
Keep the whole prescription visible: the estrogen product and amount, this progestogen’s product and route, the actual exposure days, and any missed doses or refill gaps. A record that says only “one hormone pill” loses the distinction between estrogen-only days and combined days. Bleeding dates, amount, sleep, mood and effects on daily activity help the review. They do not prove that the lining is protected. [4], [6], [7]
NICE recommends a review three months after starting treatment, then annually, with earlier review when treatment is ineffective, unwanted effects are troublesome or an adverse event occurs. An adverse event is an unwanted event during treatment; it is not automatically caused by the medicine. Review may change the product, estrogen exposure, progestogen amount, route or calendar. It also considers whether the treatment remains useful for the person’s current goals. [6]
Unscheduled bleeding should be reported rather than interpreted from a hormone blood test. NICE’s April 2026 update says bleeding is common during the first six months of systemic HRT or within three months of a change, and recommends prompt medical help beyond those periods. That is not an instruction to wait with heavy, prolonged, persistent or concerning bleeding. The British pathway assesses risk factors, adherence and both hormone components, and can arrange earlier ultrasound or tissue assessment. [6], [7]
A planned withdrawal bleed after a sequential course differs from bleeding between expected courses, or new bleeding after a stable interval without it. Ultrasound assesses the lining’s thickness; a biopsy takes a tissue sample. Neither a comfortable mood nor bleeding stopping after a dose change rules out disease by itself. Keep routine breast and cervical screening appropriate to local guidance and personal risk, and report new breast changes. The purpose of follow-up is clinical assessment, not finding a universally “optimal” progesterone blood level. [4], [6], [7]
What happens when treatment stops?
Stopping the whole HRT regimen and stopping only its progestogen are different decisions. If systemic estrogen continues with a uterus present, a protection plan is still needed. Planned off-days in a sequential prescription are part of that plan; extending them because the capsule or tablet is troublesome is a treatment change. Contact the prescriber to review a suitable alternative instead of quietly removing one component. [4], [6]
Symptoms can return after stopping HRT. NICE allows either gradual reduction or immediate stopping; gradual reduction may limit symptom recurrence in the short term, but makes no long-term difference. There is no universal tablet-cutting schedule in this guidance. A fixed combination changes both hormones when it is reduced or stopped, while separate products can be adjusted independently under clinical supervision. A scored line does not always mean a tablet is authorized to provide equal smaller doses. [6]
New severe mood deterioration, major impairment or suspected serious adverse effects need prompt help, not completion of an online “adjustment period.” A clinician may stop or change treatment urgently while arranging continuing protection where needed. Record the last actual dose and what estrogen was continued; those details make a review more useful than a general report that “the hormones did not suit me.” [4], [6], [7]
How does it compare with other options?
Micronized progesterone, medroxyprogesterone acetate, norethindrone acetate, dydrogesterone and a 52 mg levonorgestrel intrauterine system are different protection options. “Progestogen” names the family; “progestin” commonly describes a synthetic member. Capsule or tablet milligrams do not measure the same potency across these molecules. The amount is interpreted with its product, estrogen exposure and treatment days. The levonorgestrel device’s HRT protection duration is separate from its contraceptive duration. [4], [5]
Tolerability matters alongside protection. Someone who feels groggy on micronized progesterone may do differently on a synthetic progestogen, while another person has the opposite experience. A fixed estrogen/progestogen product can simplify taking the intended pair, but provides less independent adjustment than separate medicines. No comparison justifies transferring one molecule’s dose to another, or assuming a contraceptive pill supplies the intended HRT opposition. [4], [5]
Breast-cancer comparisons also require care. NICE says evidence is insufficient to establish whether the increase in risk with micronized progesterone or dydrogesterone differs from other progestogens. Observational associations can inform a discussion without proving a safer drug for every person. Personal cancer history, duration, estrogen route and the exact combination remain part of the clinical review. [6]
Common questions
Can I take half a 10 mg tablet for continuous HRT?
The Nalvee and Duphaston score line facilitates swallowing, not equal smaller doses. Their sequential labels do not authorize every half-tablet/estrogen pairing. A fixed Femoston-conti 1/5 tablet contains both estradiol and dydrogesterone and has its own evidence. Discuss a complete product-specific plan rather than borrowing a forum fraction. A fixed combination tablet contains estrogen as well; changing its amount changes both hormones rather than only the progestogen. See taking tablets. [1], [2], [10]
Is it safer for the breast than other progestogens?
Observational E3N associations were more favorable for some combinations, including dydrogesterone, but confounding and treatment differences limit interpretation. NICE says evidence is insufficient to establish a different increase in breast risk with dydrogesterone versus other progestogens. That does not mean all regimens are proven identical; it means a safety ranking is not settled. Use the actual combination and personal history in that discussion, while keeping observational uncertainty explicit. See evidence. [6], [11]
Can I compare its milligrams with progesterone?
No. These are different molecules and products, with different potency, metabolism and studied regimens. A smaller milligram number does not mean less protection or fewer adverse effects. Use the exact product-and-estrogen row, not a mass ratio or a forum conversion. The prescriber considers exposure days and estrogen dose as well as the amount. Keep the actual estrogen prescription available when discussing any proposed change. See protocols and comparisons. [4], [5]
Does no bleeding prove the lining is protected?
No. Bleeding patterns help assess a regimen, but are not a tissue-protection test. Missed exposure days, estrogen changes and the route can alter the protection question even when symptoms feel better. New or persistent unscheduled bleeding also needs assessment rather than self-adjustment. Keep the complete calendar and product information available at review. Symptom-free days do not replace the prescribed estrogen and progestogen exposure calendar. See monitoring. [4], [6], [7]
Can I stop just the progestogen?
If systemic estrogen continues with a uterus present, the protection plan still matters. Planned sequential off-days are different from an unplanned prolonged gap. Trouble tolerating treatment is a reason to review the product, route or entire regimen; it is not proof that protection can be dropped. Stopping all HRT may be gradual or immediate under NICE guidance. See stopping. [4], [6]
How long should I wait with unwanted effects?
There is no mandatory forum adjustment deadline. NICE recommends earlier review for troublesome effects or ineffective treatment, rather than waiting for the annual visit. Severe impairment, major mood deterioration or concerning bleeding needs prompt assessment. Some effects change with time, but improvement cannot be promised from selected posts. Record what changed and when, including the paired estrogen and actual dose days. See risks and monitoring. [6], [7]
Glossary
Terms used to read the product and evidence.
- Adverse event
- An unwanted event during treatment; it is not automatically caused by the medicine.
- Amenorrhea
- Absence of menstrual periods. Secondary amenorrhea occurs after periods have previously occurred.
- Bioavailability
- The amount of an administered medicine reaching the circulation; formulation and route can change it.
- Bioidentical
- Chemically identical to a hormone the body makes; the word does not establish safety or product quality.
- Biopsy
- A tissue sample examined for abnormalities, unlike an ultrasound measurement of thickness.
- Boxed warning
- A prominent warning format used in a medicine label; removing the box does not remove every risk.
- Compounding
- Preparing a medicine to a prescription rather than supplying a standard approved finished product.
- Continuous combined HRT
- Estrogen and progestogen used continuously according to their prescriptions, without scheduled progestogen-free days.
- Contraindication
- A condition in which a particular product must not be used under its label.
- Cycle
- A repeating treatment calendar. A 28-day cycle and a calendar month have different lengths.
- Daily total
- All doses taken on one day added together, not the average across days without treatment.
- Endometrium
- The lining inside the uterus that can grow in response to estrogen.
- Estrogen
- A family of hormones including estradiol; systemic treatment and low-dose local treatment have different purposes.
- Excipient
- An ingredient other than the active medicine, such as a capsule oil or lecithin.
- First-pass metabolism
- Processing in the intestine and liver before an oral medicine reaches the wider circulation.
- Hormone replacement therapy (HRT)
- In this guide, hormone treatment for menopause-related needs; also called menopausal hormone therapy.
- Hyperplasia
- Excessive tissue growth. Endometrial hyperplasia is not the same diagnosis as endometrial cancer.
- Hysterectomy
- Surgery removing the uterus; removal of ovaries is a different procedure.
- Intrauterine device (IUD)
- A device placed inside the uterus. Protection duration in HRT can differ from contraception duration.
- Metabolite
- A substance produced as the body processes another substance. Some progesterone metabolites affect brain signaling.
- Micronization
- Making particles smaller to change their dissolution and absorption, without changing the hormone molecule.
- Milligram (mg)
- A unit of mass; a 100 mg capsule contains 100 milligrams of active progesterone.
- Observational study
- A study following treatment choices rather than randomly assigning them; confounding can affect comparisons.
- Off-label
- Use outside a product’s authorized indication, route or schedule; it can be guideline-supported without becoming labeled use.
- Oral
- Swallowed, passing through the digestive system.
- Perimenopause
- The transition toward menopause, when periods and hormone patterns can change.
- Placebo
- A comparison treatment without the tested active medicine.
- Postmenopause
- The stage after menopause; context and other hormonal treatments matter when identifying it.
- Progestogen
- The broader family of progesterone-like medicines, including progesterone and synthetic progestins.
- Randomized controlled trial
- A study assigning participants to groups by chance to make a treatment comparison.
- Sequential HRT
- A regimen giving progestogen on selected days of a repeating cycle.
- Systemic
- Reaching the wider body through the circulation, rather than being intended mainly for a local site.
- Transdermal
- Absorbed through the skin, as with an estrogen patch; evidence for progesterone cream is different.
- Vaginal
- Administered in the vagina; the route alone does not establish systemic exposure or uterine protection.
- Vasomotor symptoms
- Hot flashes and night sweats.
- Withdrawal bleeding
- Bleeding following removal of hormonal exposure, such as after a sequential progesterone course.
- Meningioma
- A tumor arising from membranes around the brain and spinal cord; often benign, but its location can have serious effects.
How this guide was researched
We compared current product information with May/August 2026 BMS guidance and NICE, then checked original human research and relevant public discussions. Each amount retains its product, route, indication and country. A listing or page update is not necessarily a prescribing-information revision.
The directory distinguishes full text, abstracts and public search excerpts. Combination results do not prove the progestogen’s independent effect. Discussions show selected experiences, not surveys, response rates or prescribing authority. Anatomy images are conceptual; data figures use the exact values from named sources.
This educational content does not replace a prescription or clinical assessment. Sources that can change require an updated check when making a new treatment decision.
Explore the sources
Checked October 2, 2026. Access level describes the material actually reviewed.
Showing 16 sources
- 01
Nalvee 10 mg film-coated tablets: Summary of Product Characteristics ↗
Labels and regulators
Full SmPC retrieved. Sections 4.1–4.4 give estrogen opposition, complete sequential regimens, score-line limits and meningioma contraindication; section 6.4 gives storage.
- 02
Duphaston 10 mg film-coated tablets: Summary of Product Characteristics ↗
Labels and regulators
Full SmPC retrieved, not the separate patient leaflet. HRT 10 mg last 14 days of each 28-day estrogen cycle; source-described increase to 10 mg twice daily; meningioma and score-line restrictions.
- 03
Femoston 1/10 mg film-coated tablets: Summary of Product Characteristics ↗
Labels and regulators
Full SmPC retrieved. One tablet daily, first 14 estrogen-only then 14 combined, no break between packs; indication and contraindications.
- 04
Progestogens and endometrial protection ↗
Clinical guidance
Full guidance retrieved. Oral opposition, higher estrogen exposure, vaginal uncertainty, IUDs and compounded creams.
- 05
HRT – Practical prescribing ↗
Clinical guidance
Full four-page document retrieved; dose-table headings checked in PDF text. Average-age population; POI excluded.
- 06
Menopause: identification and management (NG23): Recommendations ↗
Clinical guidance
Full recommendations retrieved. Diagnosis, breast-risk uncertainty, stopping and 3-month/annual review; 2026 bleeding amendments.
- 07
Management of unscheduled bleeding on hormone replacement therapy (HRT) ↗
Clinical guidance
Current recommendations page reviewed. Risk assessment, adherence and investigation pathways; not a self-triage tool.
- 08
Ultra-low-dose estradiol and dydrogesterone for the treatment of menopausal symptoms ↗
Human research
PubMed abstract reviewed. 313 participants; combination arms and placebo for 13 weeks; daily hot-flush reduction and later follow-up have different comparator periods.
- 09
Efficacy and safety of low-dose estradiol/dydrogesterone in menopausal women: pooled post hoc analysis ↗
Human research
PubMed abstract reviewed. Two phase III trials, 579 pooled participants; 12/13-week vasomotor outcomes, not an independent new trial or long-term cancer comparison.
- 10
Femoston-conti 1 mg/5 mg film-coated tablets: Summary of Product Characteristics ↗
Labels and regulators
Full SmPC retrieved. Estradiol 1 mg/dydrogesterone 5 mg daily without break; natural-menopause timing and meningioma contraindication.
- 11
Unequal risks for breast cancer associated with different hormone replacement therapies: results from the E3N cohort study ↗
Human research
PubMed abstract reviewed. Observational combination associations; NICE does not establish a comparative breast-risk advantage from this evidence.
- 12
Dydrogesterone vs Progesterone in perimenopause ↗
Public experiences
Public search text rechecked 2 October 2026. Mixed mood, grogginess, bleeding regularity and early nonresponse; doses in posts are not clinical guidance.
- 13
Femoston conti 1/5 ↗
Public experiences
Full public guest-accessible thread retrieved. Initial improvement followed by mood/anxiety questions, with life events and product changes complicating attribution.
- 14
Flash VIG news: Progestin-associated meningioma risk, current situation and recommendations ↗
Labels and regulators
Full regulator text retrieved. Differentiates progestogens and states risk measures for dydrogesterone/estradiol; actual product SmPC takes precedence for exact restrictions.
- 15
Use of progestogens and the risk of intracranial meningioma: national case-control study ↗
Human research
Full open-access article retrieved. French case-control study did not find excess risk for dydrogesterone; absence of association does not override current contraindications.
- 16
Dydrogesterone: PubChem compound 9051, 2D structure record ↗
Labels and regulators
Full small SDF downloaded for deterministic chemical drawing. Chemical identity is not evidence of equal clinical potency with progesterone.
No matching sources
Try a different term or show the full list.
Updates and corrections
Draft researched October 2, 2026. Report a correction through Doserly support, identifying the claim and source. Legacy production drafts remain available.