
In this guide
What is TRT, and how is it controlled in the United States?
In the United States, testosterone replacement therapy (TRT) is available only with a prescription, because testosterone is a Schedule III controlled substance. To get it you need a clinician who can prescribe controlled drugs in your state, a diagnosis confirmed by repeated morning blood tests, and a pharmacy to fill the prescription. If you use insurance, your plan usually adds its own approval step. [1], [2], [3]
Schedule III is the federal category for drugs with an accepted medical use and a lower potential for misuse than Schedules I and II. Testosterone and its esters sit there as anabolic steroids, and because the law itself names testosterone, taking it out of control would involve Congress, not only a DEA rule. No proposal to deschedule it had been published when we checked in September 2026. [16], [17], [1]
The Food and Drug Administration (FDA) approves testosterone for men whose low testosterone has an associated medical condition, such as a testicular or pituitary disorder (hypogonadism). Labels still say benefit in "age-related" low testosterone is not established; the FDA's June 2026 request to remove that limitation is pending. Some coverage rules follow the label: Oklahoma's Medicaid program, for example, asks for a diagnosed cause or abnormal pituitary hormone results. [18], [19], [20], [21], [22]
How do you get TRT in the US?
Most men follow the same seven steps, whoever prescribes. Checked September 2026.
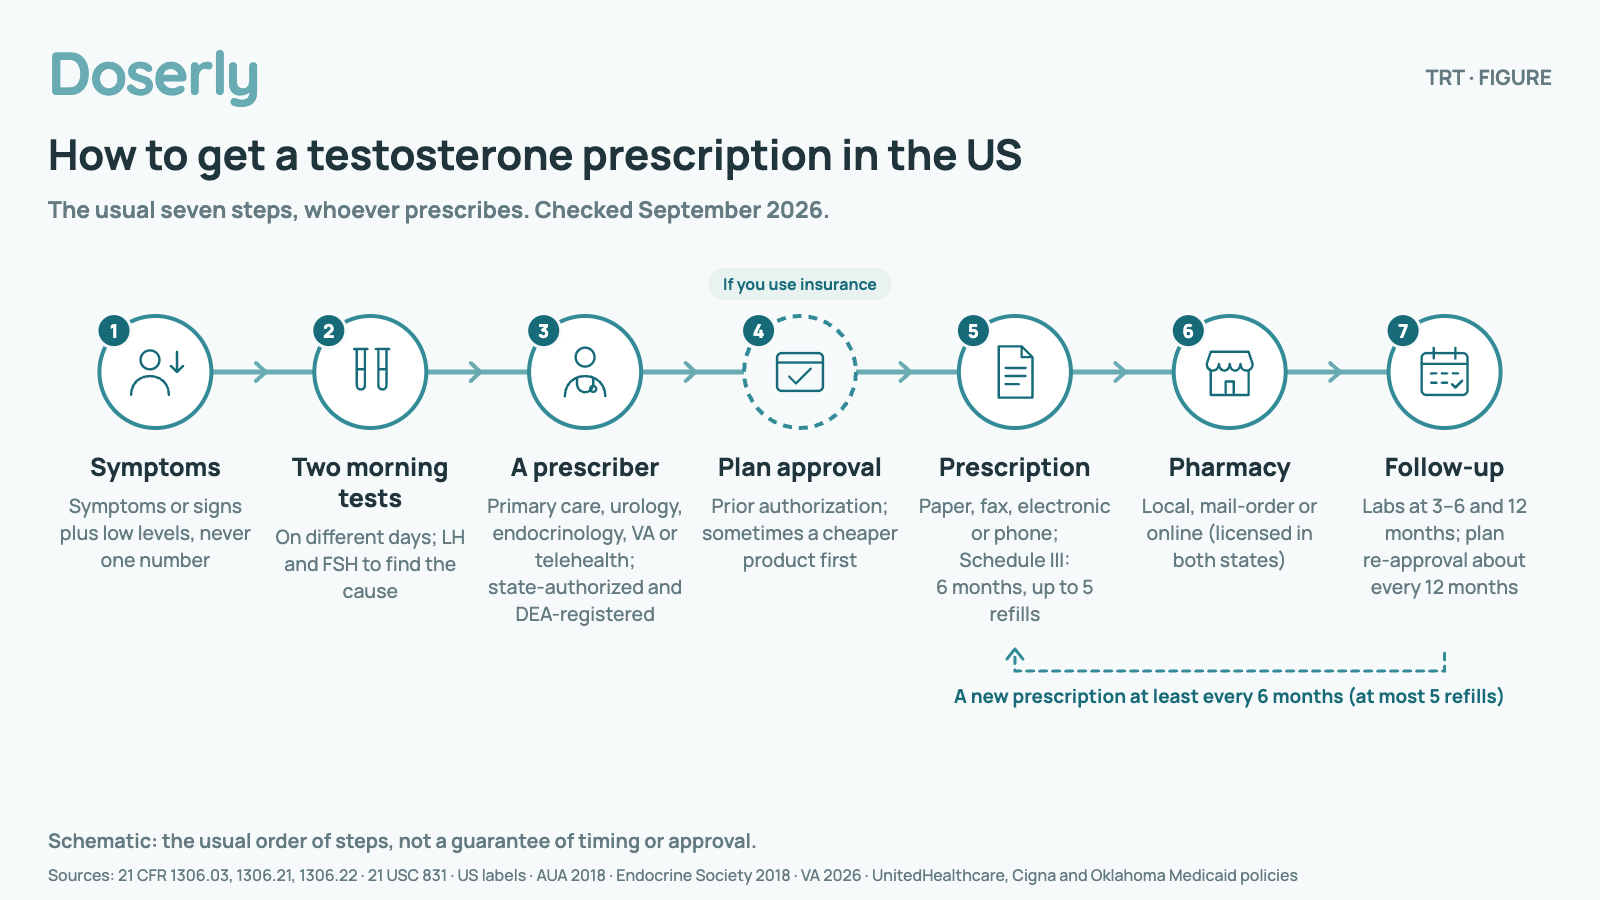
How to get a testosterone prescription in the US
The usual seven steps, whoever prescribes. Checked September 2026.
- 1.Symptoms
- Symptoms or signs plus low levels, never one number
- 2.Two morning tests
- On different days; LH and FSH to find the cause
- 3.A prescriber
- Primary care, urology, endocrinology, VA or telehealth; state-authorized and DEA-registered
- 4.Plan approval
- If you use insurance
Prior authorization; sometimes a cheaper product first
- 5.Prescription
- Paper, fax, electronic or phone; Schedule III: 6 months, up to 5 refills
- 6.Pharmacy
- Local, mail-order or online (licensed in both states)
- 7.Follow-up
- Labs at 3–6 and 12 months; plan re-approval about every 12 months
After step 7: back to step 5. A new prescription at least every 6 months (at most 5 refills).
Schematic: the usual order of steps, not a guarantee of timing or approval.
- Symptoms plus low blood levels. Guidelines diagnose low testosterone only when symptoms or signs and low levels occur together. [4]
- Two morning blood tests on different days, plus the pituitary hormones LH and FSH (and prolactin in some men) to look for a cause. See the TRT blood work and low testosterone guides. [3], [4], [23]
- A prescriber: primary care, a urologist, an endocrinologist, the Department of Veterans Affairs (VA) or telehealth. [2]
- Insurance approval, if you use insurance: often prior authorization, depending on the plan and the form, sometimes after trying a cheaper product first. [5], [22]
- The prescription, on paper, by fax, electronically or by phone, for "a legitimate medical purpose". Prescribers who treat Medicare Part D patients must send most controlled-drug prescriptions electronically. [24], [25], [26]
- A pharmacy: local, mail-order or online. [27], [28]
- Follow-up and renewal. Guidelines recheck testosterone and hematocrit at 3–6 and 12 months (the Endocrine Society and the VA) or every 6–12 months (the American Urological Association, AUA), and plans that publish a renewal period re-approve every 12 months. [23], [29], [4], [5], [6]
Who can prescribe testosterone?
Any clinician your state authorizes to prescribe controlled substances who also holds a DEA registration; federal rules name no specialty. Nurse practitioners and physician assistants can prescribe it where their state gives them that authority, which varies by state, and a clinician normally needs a separate DEA registration for each state where they prescribe. [2], [30]
Guidelines point some men to a specialist: the AUA suggests a pituitary scan, and the VA an endocrinology referral, when testosterone is below 150 ng/dL (5.2 nmol/L) with low or normal pituitary hormones. Men who want children need fertility advice before any testosterone (see who should be cautious). [4], [29], [31]
What if your doctor says no?
No rule makes a clinician prescribe testosterone: each must judge that it serves "a legitimate medical purpose", and the pharmacist shares that responsibility. Results near a cut-off, an afternoon test or a reversible cause often lead to retesting or treating the cause first; for low testosterone linked to excess weight, the Endocrine Society's 2026 statement calls weight loss typically first-line. [25], [32]
You can ask which guideline your clinician follows, ask for repeat morning tests, or get a second opinion. The pillar guide lists questions to ask any prescriber.
What do you need to qualify for TRT in the US?
At least two low testosterone results, usually from morning blood tests, and for guidelines and several insurers, symptoms too. The table shows the rules in US guidelines, labels, the VA and published insurer policies, checked September 2026; plans change often, so check your own plan's current document.
| Who sets the rule (document, date) | Cut-off | Tests asked for | Approval and renewal |
|---|---|---|---|
| AUA guideline (2018, validity confirmed 2024) | Below 300 ng/dL (10.4 nmol/L) | Two early-morning tests, plus symptoms or signs | Not applicable |
| Endocrine Society guideline (2018) | Below 264 ng/dL (9.2 nmol/L) on standardized assays | Two fasting morning tests with an accurate assay | Not applicable |
| Endocrine Society statement (July 2026) | "Near 300 ng/dL" | At least two early-morning fasting tests | Not applicable; same at any age |
| US product labels (all) | Below the lab's normal range | Morning tests on at least two separate days | Not applicable |
| VA criteria (March 2025) and recommendations (January 2026) | "Unequivocally low"; 264 ng/dL (9.2 nmol/L) on certified assays | Two fasting morning tests at least a week apart, plus LH, FSH, prolactin and hematocrit | Not started with hematocrit above 48% or when future fertility is wanted |
| UnitedHealthcare pharmacy policy for gels, solutions, patches, oral and nasal products and Xyosted (effective February 1, 2026) | Below 300 ng/dL or below the lab's range | Two, at separate times | 12 months; renewal needs a recent level within or below range. Xyosted only after generic injections and gels (step therapy) |
| Anthem medical-benefit policy for injections CC-0026 (October 2025) | Below 300 ng/dL at 70 or younger; below 200 ng/dL (6.9 nmol/L) over 70 | Two morning tests at least 24 hours apart | Not approved with hematocrit above 48% or untreated sleep apnea; renewal needs a level within 180 days and symptom benefit |
| Cigna pharmacy policy for injections, including generic cypionate and enanthate, CNF620 (September 2025) | Low by the lab's own range | Two morning tests on separate days | 1 year |
| Aetna medical policy for cypionate CPB 1014 (reviewed July 2026) | Low by the lab's range or practice guidelines | At least two confirmed low morning tests | Not stated |
| Medicaid example: Oklahoma (criteria page, updated November 2025) | Below 300 ng/dL, plus a diagnosed cause or abnormal LH or FSH | Two morning tests | 1 year; some products only after 12-week trials of an injection and a topical |
[4], [23], [32], [3], [33], [29], [5], [34], [6], [35], [22]
Every guideline, label and insurer policy in the table asks for at least two low results before treatment, most of them from morning tests; the guidelines, Anthem and Cigna also require symptoms. They differ on the cut-off (from the lab's own range to 300 ng/dL, or 200 ng/dL over 70 for one insurer), on which products need approval and on how often it must be renewed. UnitedHealthcare's published prior-authorization policy applies to gels, oral and nasal products and Xyosted, not to generic injections, while Cigna's also applies to generic injections. Your plan's own policy, not a national number, decides coverage. Guidelines differ because "normal" depends on the lab method and reference group: 264 ng/dL is the lower limit in healthy young men on standardized assays, while the AUA chose 300 ng/dL as a practical cut-off. [23], [4], [5], [6], [34]
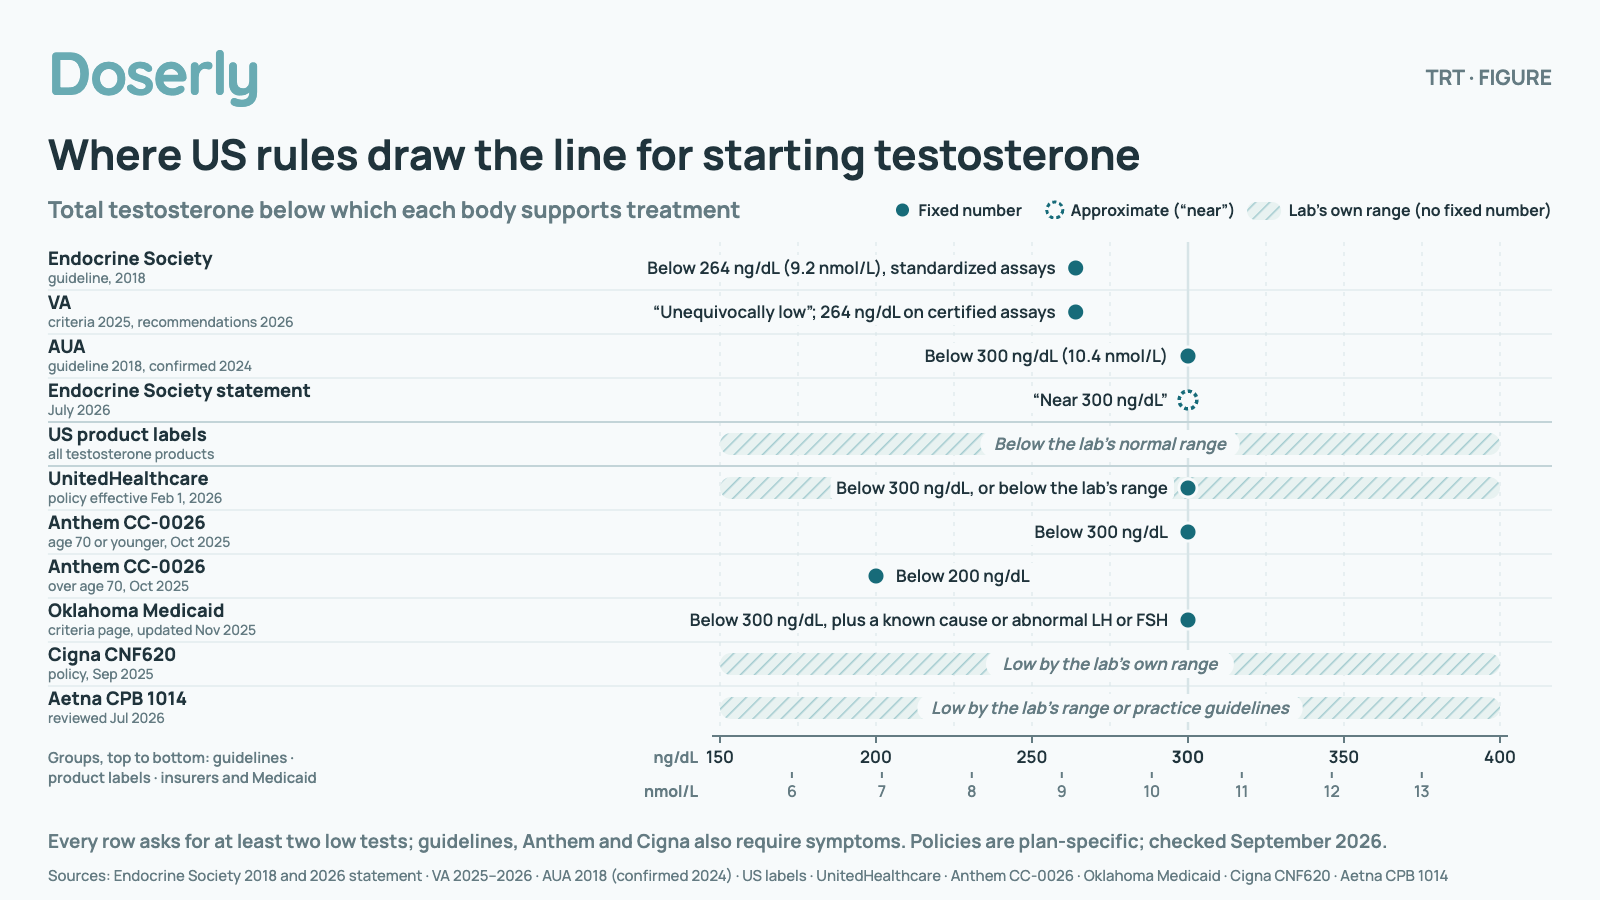
Where US rules draw the line for starting testosterone
Total testosterone below which each body supports treatment.
Each line runs from 150 ng/dL (about 5 nmol/L, left) to 400 ng/dL (about 14 nmol/L, right); the thin mark is 300 ng/dL. A dashed circle is approximate; a striped bar means the lab’s own range, with no fixed number.
Guidelines
- Endocrine Society (guideline, 2018)
- Below 264 ng/dL (9.2 nmol/L), standardized assays
- VA (criteria 2025, recommendations 2026)
- “Unequivocally low”; 264 ng/dL on certified assays
- AUA (guideline 2018, confirmed 2024)
- Below 300 ng/dL (10.4 nmol/L)
- Endocrine Society statement (July 2026)
- “Near 300 ng/dL”
Labels
- US product labels (all testosterone products)
- Below the lab’s normal range
Insurers and Medicaid
- UnitedHealthcare (policy effective Feb 1, 2026)
- Below 300 ng/dL, or below the lab’s range
- Anthem CC-0026 (age 70 or younger, Oct 2025)
- Below 300 ng/dL
- Anthem CC-0026 (over age 70, Oct 2025)
- Below 200 ng/dL
- Oklahoma Medicaid (criteria page, updated Nov 2025)
- Below 300 ng/dL, plus a known cause or abnormal LH or FSH
- Cigna CNF620 (policy, Sep 2025)
- Low by the lab’s own range
- Aetna CPB 1014 (reviewed Jul 2026)
- Low by the lab’s range or practice guidelines
Every row asks for at least two low tests; guidelines, Anthem and Cigna also require symptoms. Policies are plan-specific; checked September 2026.
US labs report testosterone in ng/dL; most other countries use nmol/L. 300 ng/dL is about 10.4 nmol/L (1 nmol/L is 28.84 ng/dL), and the testosterone unit converter switches between them. [5]
Do you have to stop TRT to qualify with a new doctor or insurer?
Sometimes. Insurers want results from before treatment, and UnitedHealthcare's policy notes this "may require treatment to be temporarily held". The VA recommends holding testosterone for 3–6 months, then rechecking, for veterans who recently started it elsewhere without records, but can waive baseline results case by case after more than a year of treatment. Bring your original pre-treatment results if you have them. [5], [33]
Does age change who gets approved?
It can. The labels' age-related limitation stands while the FDA's request to remove it is pending, and Anthem uses 200 ng/dL for men over 70. Guidelines have moved: in 2018 the Endocrine Society suggested against routinely treating all men 65 and older, while its 2026 statement applies the same approach at any age. [19], [20], [34], [23], [32]
How do Medicare, Medicaid, marketplace plans and the VA handle it?
- Medicare. Testosterone is covered under Part D when used for a medically accepted indication, and each plan sets its own drug list (formulary) and approval rules. [7]
- Medicaid. Each state sets its own rules; federal law lets a state require prior authorization for any drug and exclude "agents when used to promote fertility", such as hCG (human chorionic gonadotropin). [8]
- Marketplace plans must cover at least one drug in every US Pharmacopeia category and class, and decide a request to cover an unlisted drug within 72 hours (24 when urgent). [36]
- The VA uses its own criteria (see the table), does not generally recommend aromatase inhibitors, and reserves hCG for men who want fertility. [33], [29]
Which testosterone products are available in the US?
Checked September 2026. A current label shows that a product is approved, not that a pharmacy has it in stock on a given day.
| Form | Products | How it is given (label) | Generic? | Guide |
|---|---|---|---|---|
| Cypionate injection | Depo-Testosterone, generics (a new generic was approved September 3, 2026), Azmiro | Intramuscular (into a muscle), 50–400 mg every 2 to 4 weeks | Yes | Cypionate |
| Enanthate injection | Generic vials | Intramuscular, 50–400 mg every 2 to 4 weeks | Yes | Enanthate |
| Enanthate autoinjector | Xyosted | Subcutaneous (into the fatty layer under the skin), weekly, starting at 75 mg | No | Xyosted |
| Undecanoate injection | Aveed | Intramuscular, 750 mg at the start, at 4 weeks, then every 10 weeks, in a clinic with 30 minutes of observation | No | Undecanoate injection |
| Gels and solution | AndroGel 1% and 1.62%, Testim, Vogelxo, generic gels, generic 2% solution | Transdermal (absorbed through the skin), daily | Yes, for most | Testosterone gel |
| Oral undecanoate | Jatenzo, Kyzatrex (a 50 mg capsule was added August 25, 2026), Tlando | Swallowed, usually twice daily with food | No | Oral testosterone |
| Nasal gel | Natesto | Into each nostril three times daily | No | Natesto |
| Pellets | Testopel | Implanted subcutaneously every 3 to 6 months | No | Pellets |
| Oral methyltestosterone | Methyltestosterone capsules, Methitest | Swallowed; still listed, but the AUA advises against it because of liver harm | Yes | n/a |
[37], [38], [39], [40], [3], [41], [42], [43], [44], [45], [46], [47], [19], [48], [49], [50], [51], [4], [9]
Generic cypionate is by far the most used: in Medicare Part D in 2024 it had 1,118,253 claims for 281,637 people, against 556,670 claims for generic gels and solutions. Xyosted, Jatenzo, Tlando, Natesto and Testim appeared only as brands in the September 2026 pharmacy price data, and no testosterone propionate product is approved in the US. [10], [9], [37]
Can a pharmacy swap cypionate for enanthate? Not on its own: the FDA treats different esters as "not therapeutically equivalent", so switching needs a new prescription. [52]
No longer sold
- Striant (a buccal tablet held against the gum): approval withdrawn June 15, 2020.
- Androderm (skin patch): discontinued.
- Axiron (armpit solution): the brand's approval was withdrawn in 2018; generic 2% solutions remain.
- Fortesta (gel): the brand was discontinued on December 1, 2023.
- Delatestryl (enanthate brand): no longer marketed; generic enanthate remains.
What about compounded testosterone, hCG and enclomiphene?
Compounded testosterone creams and pellets are not FDA-approved, and the FDA does not check their safety, effectiveness or quality before sale; the AUA advises commercially made testosterone when possible. Approved Testopel pellets are different: one Medicare contractor covers up to six per insertion. [54], [55], [4], [56] See compounded testosterone cream.
Since March 23, 2020, hCG cannot be compounded, so only approved products such as Pregnyl and Novarel can be lawfully dispensed. Enclomiphene is not FDA-approved; an FDA advisory committee voted 4 to 8 against letting pharmacies compound it, and it remains under evaluation. [57], [58], [59] See hCG and enclomiphene.
Is there a testosterone shortage?
Not on the FDA's list: its shortage database showed no testosterone product in September 2026. Individual brands or pharmacies can still run short (see what people report). [60]
How much does TRT cost in the US?
It depends mostly on the form and your plan. The only official figures are what pharmacies pay and what Medicare spends; neither is the price you will be charged. Checked September 2026.
| Product | Official figure | Source and meaning |
|---|---|---|
| Generic cypionate 200 mg/mL, 10 mL vial | About $35.82 ($3.58 per mL) | NADAC, September 23, 2026: average price pharmacies pay |
| Generic cypionate 100 mg/mL, 10 mL vial | About $45.28 ($4.53 per mL) | NADAC |
| Generic cypionate 200 mg/mL, 1 mL vial | $11.39 per vial | NADAC |
| Generic enanthate 200 mg/mL | $14.48 per mL | NADAC |
| Generic 1.62% gel, pump | $0.47 per gram (about $35 for 30 days at the 40.5 mg starting dose) | NADAC |
| Xyosted | About $158 per weekly autoinjector ($316.50 per mL) | NADAC |
| Jatenzo | $8.95 to $17.93 per capsule | NADAC |
| Tlando | $7.17 per capsule | NADAC |
| Natesto | $41.28 per gram | NADAC |
| Average Medicare Part D spending per claim, 2024 | Generic cypionate $37.01; generic topical testosterone $167.85; Xyosted $788.20; Jatenzo $1,055.04; AndroGel $1,148.50 | Centers for Medicare & Medicaid Services (CMS), before rebates |
Generic injections cost the least by a wide margin, and brand-only products the most. Your share also depends on your plan's tiers, deductible and whether it covers the form prescribed. [9], [10]
What will you actually pay?
- With Medicare Part D in 2026, the standard plan's deductible is $615 and your out-of-pocket spending on covered drugs is capped at $2,100 a year. The Medicare Prescription Payment Plan can spread those costs over the year, but it "doesn't save you money". [61], [62], [63]
- Drug-maker copay coupons generally cannot be used by people on Medicare Part D or other federal programs. [64]
- Injections given in a clinic, such as Aveed, are paid under Medicare Part B. For Aveed, Medicare's payment limit from October 1, 2026 is $2.203 per mg, about $1,652 for one 750 mg injection; that is what Medicare pays, not your share. [65]
- Health savings accounts (HSAs). Prescribed medicines count as medical expenses, and HSA withdrawals for qualified medical expenses are not taxed. A drug brought in or shipped from another country generally does not count. [66], [67]
- If your plan says no, your prescriber can send more information, ask for a formulary exception or appeal; marketplace plans must decide an exception within 72 hours (24 when urgent). [36]
- Cash prices and clinic or telehealth fees are set by each business and not officially tracked; see what people report.
What are the prescription and telehealth rules?
Checked September 2026. State laws can add to the federal rules below.
| Rule | What it says |
|---|---|
| Schedule | Schedule III controlled substance; no proposal to change that has been published |
| Prescription life | Cannot be filled more than 6 months after it was written or refilled more than 5 times |
| Moving a prescription | Refills can be transferred to another pharmacy once (freely within a chain that shares a real-time database); an unfilled electronic prescription can move once at your request |
| Telehealth without an in-person visit | Allowed through December 31, 2026; a permanent rule is pending |
| VA telehealth | Allowed if any VA clinician has ever seen the veteran in person |
| Possession without a prescription | Up to 1 year in prison and a minimum $1,000 fine (first federal offense; state penalties also apply) |
| Selling or supplying | Up to 10 years and a fine up to $500,000 for an individual (first federal offense) |
[1], [68], [13], [69], [70], [11], [12], [71], [72], [73]
How long does a testosterone prescription last?
Six months at most: a Schedule III prescription cannot be filled or refilled more than six months after it was written, or refilled more than five times, and then your prescriber must write a new one. Partial fills are allowed within those 6 months. [68], [13], [74]
Every state runs a prescription drug monitoring program (PDMP), a database of controlled-substance prescriptions that prescribers and pharmacists can check; each state sets which drugs it tracks. [75]
Can you move a prescription to another pharmacy?
Yes, with limits. Refills can be transferred between pharmacies once, or freely between pharmacies sharing a real-time database, such as one chain. Since August 28, 2023, an unfilled electronic prescription can also be moved once at your request. If you move states, you may need a new prescription from a prescriber authorized there. [69], [70], [76], [2]
Can you get TRT through telehealth after 2026?
Through December 31, 2026, yes: temporary rules let clinicians prescribe controlled medicines such as testosterone by telehealth without seeing you in person. After that is not settled. [11]
- The permanent fix is pending. In January 2025 the DEA proposed a special registration letting qualified clinicians prescribe Schedule III–V drugs by telehealth, with a registration for every state where a patient is treated and a nationwide PDMP check starting 3 years later. The final rule reached White House review on August 25, 2026 and was unpublished when we checked on September 28, 2026. [77], [12]
- Without a new rule or another extension, the Ryan Haight Act's requirement returns: an online prescription needs a prescriber who has done "at least 1 in-person medical evaluation" of you, or a covering clinician acting for them. After that visit, the clinician can keep prescribing by telehealth. [68]
- Veterans: since December 31, 2025, a VA clinician may prescribe by telemedicine to any veteran ever seen in person by a VA clinician. [71], [78], [79]
If you get testosterone only through telehealth, ask your provider how they will handle January 2027. We will update this section when the rule is published.
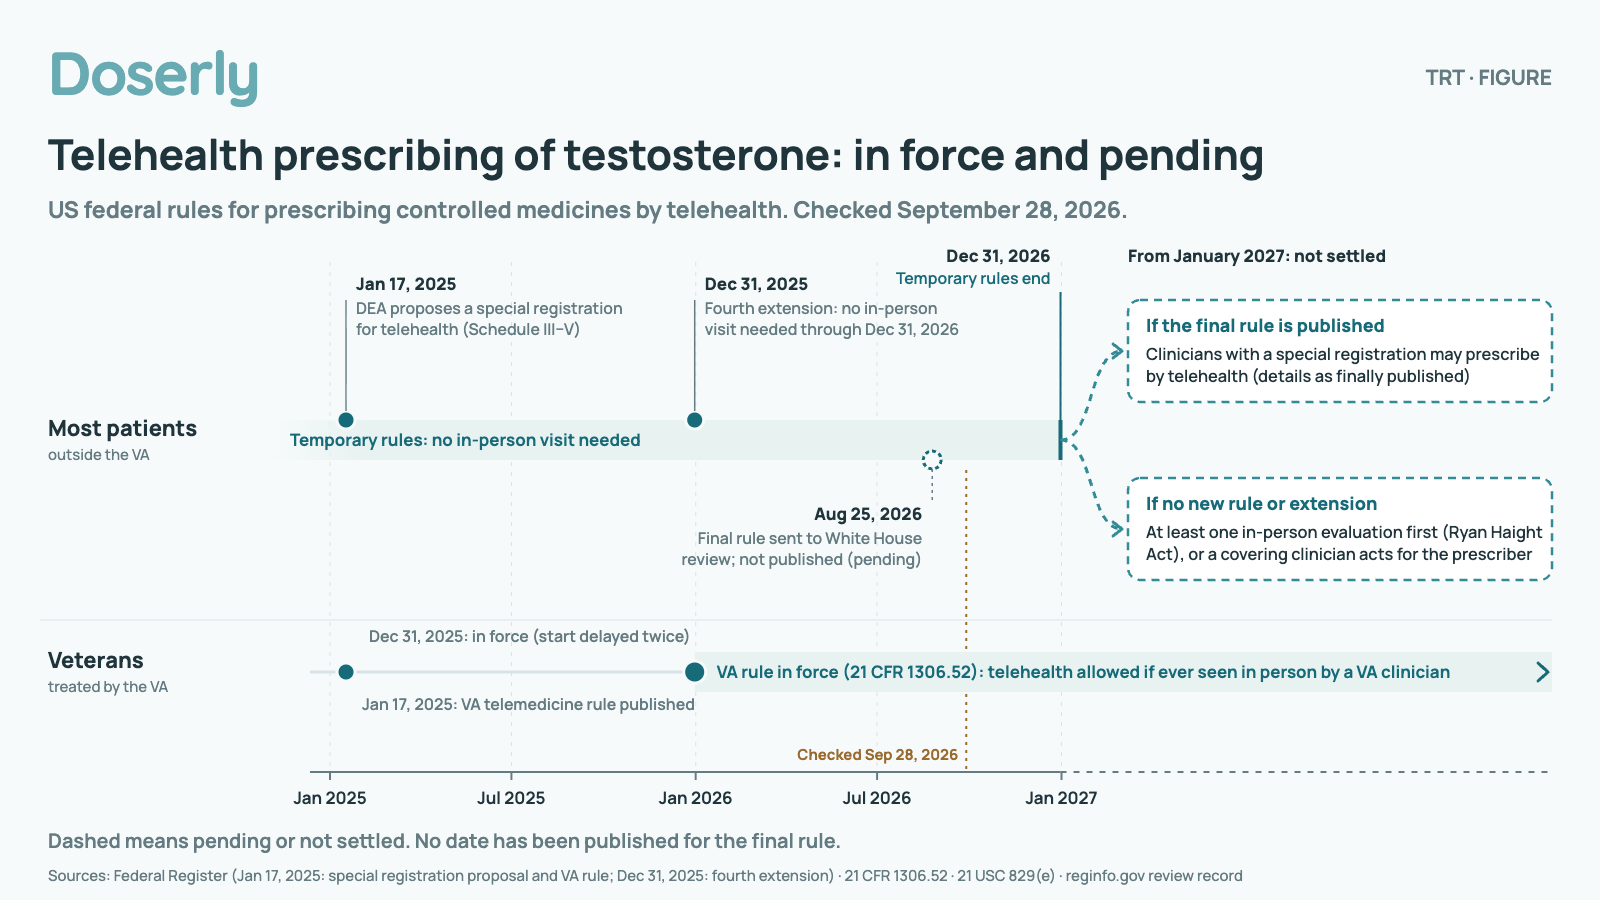
Telehealth prescribing of testosterone: in force and pending
US federal rules for prescribing controlled medicines by telehealth. Checked September 28, 2026.
- Jan 17, 2025Proposed
DEA proposes a special registration letting qualified clinicians prescribe Schedule III–V medicines by telehealth. The VA telemedicine rule is published the same day.
- Dec 31, 2025In force
Fourth extension published: no in-person visit needed through December 31, 2026. The VA rule takes effect: a VA clinician may prescribe by telehealth to a veteran ever seen in person by a VA clinician.
- Aug 25, 2026Pending
The final special-registration rule reaches White House review. It was not published when we checked on September 28, 2026.
- Dec 31, 2026Scheduled
The temporary rules end.
- From January 2027Not settled
If the final rule is published, clinicians with a special registration may prescribe by telehealth (details as finally published). If there is no new rule or extension, a prescriber needs at least one in-person evaluation first (Ryan Haight Act), or a covering clinician acts for them.
Dashed tags are pending or not settled. No date has been published for the final rule.
Are online TRT clinics and pharmacies legal?
Yes, when they follow the same rules as anyone else: a valid prescription from a clinician authorized in your state, and a pharmacy licensed in both the shipping and receiving states with a DEA registration for internet dispensing. The FDA's BeSafeRx program says a safe online pharmacy "always requires a doctor's prescription", has a US address and a licensed pharmacist, and "is licensed with a state board of pharmacy". A site selling testosterone without a prescription breaks federal law, and a "research use only" label does not make a vial legal or the same as a licensed medicine. [27], [28], [80], [81]
Legal is not the same as good care: the pillar guide summarizes studies of what online TRT services get wrong.
Why does the pharmacy say to discard a vial after 28 days?
Because of a rule written for clinics and hospitals. The Centers for Disease Control and Prevention (CDC) says an opened multi-dose vial should be discarded within 28 days "unless the manufacturer states another date", and the US Pharmacopeia's standard says the same. Both are written for health-care settings, not a patient's own vial at home, and the US cypionate labels we checked give no in-use period. Ask your pharmacist or prescriber whether smaller vials suit your dose. [82], [83], [37]
Can you travel with, mail or import testosterone?
Checked September 2026. You can fly with your own prescribed testosterone, but you cannot mail it, and bringing home testosterone bought abroad is tightly limited. [84], [14], [85]
- Flying. The Transportation Security Administration (TSA) allows declared medical liquids and gels, such as vials or gel, above the usual carry-on limit, and unused syringes with the injectable medicine. [84], [86]
- Crossing the border. Keep it in the original dispensed container and declare it; no DEA permit is needed for your own supply. A US resident may bring back no more than 50 dosage units of controlled medicine obtained abroad, and visitors may generally bring up to a 90-day supply. [85], [87]
- Mailing. Only DEA registrants such as pharmacies may mail anabolic steroids, so you cannot post testosterone to yourself or anyone else. [14]
- Importing. The FDA says importing drugs for personal use is illegal "in most circumstances", and the DEA decides for controlled substances; imported drugs also do not count for HSA purposes. [88], [66]
The traveling with testosterone guide covers other countries' limits, storage, time zones and paperwork.
Is TRT safe, and what is the FDA changing?
Generally yes for men with confirmed low testosterone who are monitored, but it has known risks. The largest trial ruled out a large rise in heart attacks and strokes over an average of 33 months of follow-up, but testosterone raises red blood cells and blood pressure, can lower or stop sperm production, and in that trial increased atrial fibrillation, lung clots, kidney injury and fractures. [89], [19], [90], [3], [91]
TRAVERSE, the trial behind the 2025 label changes, randomly assigned 5,204 men aged 45 to 80 with low testosterone and heart disease or high heart risk to daily testosterone gel or placebo gel. Among the 2,596 men who used testosterone gel and the 2,602 who used placebo gel, heart attack, stroke or cardiovascular death occurred in 182 (7.0%) vs 190 (7.3%), a hazard ratio of 0.96 (95% confidence interval 0.78 to 1.17), which met the trial's safety margin. Atrial fibrillation (3.5% vs 2.4%), acute kidney injury (2.3% vs 1.5%) and pulmonary embolism (0.9% vs 0.5%) were more common on testosterone, and so were fractures: 91 of 2,601 men (3.50%) vs 64 of 2,603 (2.46%), counting every randomized man. It tested only a gel, men used it for an average of 21.7 months, and about 61% stopped their study gel early. [89], [19], [91] The TRT and heart health guide covers it in full, and the side effects guide covers the rest.
What has the FDA changed, and what is still pending?
- March 2015. The FDA required labeling changes urging caution in using testosterone for age-related low testosterone. [90]
- February 28, 2025. The FDA required every testosterone label to add the TRAVERSE results and blood-pressure warnings and to drop the boxed-warning language about heart risk. Labels such as AndroGel, Testim, Natesto, Xyosted, Aveed, Azmiro and the oral capsules now carry the TRAVERSE results. The Depo-Testosterone and generic cypionate and enanthate vial labels, Testopel and some generic gels and solutions still carry the older statement that long-term heart-safety trials have not been done (checked September 2026). [90], [42], [3], [39], [19], [37], [21], [40], [50], [45], [46]
- July 2025. Blood-pressure boxed warnings were removed from Xyosted, Jatenzo, Tlando and Kyzatrex. Boxed warnings now remain only on Aveed (oil reaching the lungs and allergic reactions, with a restricted program called a REMS) and on gels and solutions (transfer to others). [19], [48], [41]
- December 10, 2025 and April 16, 2026. An FDA expert panel on TRT for men, then an invitation to makers to apply for a new use in low sex drive; no such use is approved. [92], [93]
- June 18, 2026. The Department of Health and Human Services (HHS) announced FDA requests to remove the age-related limitation, to rule out testosterone only for prostate cancer that has spread beyond the prostate (metastatic), where labels now rule it out for known or suspected prostate cancer, and to revise the prostate-enlargement warning. These are requests, not yet in any label. [20], [18], [21]
Who should be especially cautious?
- Men who want children now or later. Testosterone lowers sperm production, reduced fertility may not reverse, and the AUA says not to prescribe it to men trying to conceive; Medicaid and Part D may not cover fertility drugs. See TRT and fertility. [3], [4], [31], [8]
- Men with a high hematocrit, untreated severe sleep apnea, prostate or breast cancer, or a recent heart attack or stroke. Guidelines advise against starting, and some insurers refuse approval for the first two. See hematocrit on TRT. [23], [29], [34]
- Drug-tested athletes. A therapeutic use exemption is granted only for low testosterone with a physical cause, not for age or weight. [15], [94]
- Under-18s. Testosterone for teenagers belongs only in specialist care.
- Women. This guide covers men; see testosterone therapy for women.
Which medicines interact with testosterone?
Labels name insulin and other diabetes medicines (testosterone can lower blood sugar), blood thinners taken by mouth, corticosteroids (more fluid retention) and medicines that raise blood pressure; the pillar guide covers the rest. Bring a complete list of what you take to your pharmacist or prescriber. [19], [37]
Is testosterone legal elsewhere, and in sport?
Checked September 2026. Testosterone is not internationally controlled, so each country sets its own rules: it is a Class C drug in the UK, a Schedule IV controlled substance in Canada and a Schedule 4 prescription-only medicine in Australia. The World Anti-Doping Agency (WADA) prohibits it at all times, and its 2027 list keeps the ban. See the guides for the UK, Canada, Australia and Europe. [95], [96], [97], [98], [15], [99]
What do people report about getting TRT in the US?
Public forums are full of men trying to get a first prescription, keep coverage or move their care. The threads below are public Reddit discussions from 2025 and 2026, read with their replies; they show experiences, not how often they happen, and we left out threads about testosterone used without a prescription.
What gets in the way of a first prescription?
Waits and refusals come up most. One man in his 40s, at 195 and then 162, was referred to endocrinology by a primary care doctor who would not prescribe; at least five offices turned him down once they learned it was for testosterone, and one offered a date about 11 months away. Most replies told him to ask for a urologist. [100] A wife described a 5 to 6 month wait for an endocrinologist before she found a private appointment within weeks. [101]
Borderline or changing results cause confusion. One veteran reported VA results of 162 and then 390 a week later; another said the VA considered his repeated results around 260 to 270 acceptable. [102], [103] Going the other way, a man who felt mostly well said a clinic called 484 low and offered 100 mg a week; many replies advised retesting first. [104]
What do people report about insurance and price?
Coverage often turns on the tests. After a urologist prescribed Xyosted, one man's insurer asked for another blood test 4 weeks later; several replies described covered cypionate at $10 to $15 a month. [105] Another, at about 415 ng/dL (14.4 nmol/L), tried clomiphene with a urologist for 6 months before starting testosterone, and his plan charged $25 for 90 days; a reply noted most plans want results below 300. [106]
A man prescribed AndroGel was quoted about $700 at the pharmacy, even for the generic with a discount card, because his plan did not cover it. [107] A man on prescribed TRT for 20 years pays $30 for a 10 mL vial at a retail pharmacy, but the most-upvoted replies said the hard part is finding a prescriber, and some preferred an all-inclusive monthly membership. [108] Another was quoted $500 for a clinic refill that had to include anastrozole and tamoxifen he said he did not need. [109]
What goes wrong with refills and pharmacies?
Gaps happen when a visit is cancelled: one urologist cancelled two follow-ups and would not refill until a visit a month later. [110] When a small clinic's only prescriber went on an extended absence, one man's local doctor wrote a bridging prescription. [111] Moving states meant a new prescriber, a new authorization and then a backorder for one man; another could no longer get enanthate locally, though replies found a mail-order pharmacy that stocked it. [112], [113] Others report pharmacies newly applying the 28-day vial rule. [114]
Moving care from a clinic to a regular doctor can mean retesting: one urologist said a man would need to stop for about a month so new tests could support a prescription and insurance. [115] Another man's new urologist said hCG would be expensive because insurance would not cover it. [116]
How can you judge an access story?
Ask: Were the tests drawn in the morning, twice, before any treatment? What did the plan's written policy say? Was the price for the medicine alone or a package of visits, labs and extra medicines? Selected forum threads are not a survey of US patients or a substitute for your plan's own documents.
Common questions about getting TRT in the US
Does insurance cover TRT?
Usually, when your tests meet your plan's rules. Large insurers' published policies want two low results, below 300 ng/dL or below the lab's range; many need prior authorization for some or all forms, renewed yearly, and some require a cheaper product first. Medicare Part D and Medicaid also cover it. Checked September 2026. [5], [6], [7], [8] See who qualifies.
How much does TRT cost without insurance?
It depends on the form. Generic cypionate is cheapest: pharmacies paid about $35.82 for a 10 mL vial of 200 mg/mL in September 2026, while brand-only products such as Xyosted cost many times more. Pharmacy cash prices and clinic fees vary and are not officially tracked. [9] See cost.
Can a primary care doctor prescribe testosterone?
Yes. Any clinician your state authorizes to prescribe controlled substances, with a DEA registration, can prescribe it; no federal rule requires a specialist. Guidelines suggest a specialist for very low levels with low pituitary hormones, or when fertility matters. [2], [4] See who can prescribe.
Will telehealth TRT end after 2026?
Not necessarily, but the rules will change unless new action is taken. Prescribing without an in-person visit is allowed through December 31, 2026; the DEA's permanent special-registration rule was still under White House review on September 28, 2026. Without it, a prescriber must have seen you in person at least once. [11], [12], [68] See telehealth.
Is it legal to buy testosterone online?
Only with a valid prescription from a licensed pharmacy. An online pharmacy must be licensed in the state it ships from and the state it ships to, and hold a DEA registration for internet dispensing. Buying without a prescription, or importing it for yourself, is illegal. [28], [80], [88] See online pharmacies.
Does Medicare cover testosterone?
Yes, under Part D, when used for a medically accepted indication; each plan sets its own drug list and approval rules. In 2026 the standard deductible is $615 and out-of-pocket drug costs are capped at $2,100 a year. Aveed, given in a clinic, falls under Part B. [7], [61], [65] See cost.
Glossary
Plain explanations of the medical, legal and insurance terms used in this guide. Underlined terms in the text link here.
- Anabolic steroid
- Testosterone and drugs related to it that build muscle. US drug law groups testosterone under this term, which is why it is a controlled substance.
- Aromatase inhibitor
- A medicine, such as anastrozole, that blocks the enzyme turning testosterone into estradiol. The VA does not generally recommend it for men on TRT.
- Boxed warning
- The FDA's strongest label warning, printed in a box at the top of the prescribing information. For testosterone it now appears only on Aveed and on gels and solutions.
- Buccal
- Absorbed through the lining of the cheek or gum. Striant, a buccal testosterone tablet, is no longer sold in the US.
- Controlled substance
- A medicine whose prescribing, possession, import or export is restricted by drug law because it can be misused. Testosterone is controlled in the US, UK, Canada and Australia.
- DEA registration
- A registration with the US Drug Enforcement Administration that a clinician or pharmacy needs to prescribe or dispense controlled substances. Clinicians normally need one for each state where they prescribe.
- Endocrinologist
- A doctor who specializes in hormones and the glands that make them, including the pituitary and testicles.
- Formulary (drug list)
- The list of medicines a health plan covers, often sorted into cost tiers. A plan can cover a drug that is not on its list through an exception request.
- Hazard ratio
- A measure comparing how often an event happens over time in two groups. A hazard ratio of 1 means no difference. TRAVERSE's heart result of 0.96 was within the range expected by chance, so it showed no meaningful difference.
- hCG (human chorionic gonadotropin)
- A hormone medicine that acts like LH, prompting the testicles to make testosterone and helping keep sperm production going. In the US only approved products can be dispensed; it cannot be compounded.
- Hematocrit
- The share of the blood made up of red blood cells. Testosterone therapy can raise it, which is why it is checked.
- Health savings account (HSA)
- A US tax-advantaged savings account linked to a high-deductible health plan. Withdrawals used for qualified medical expenses, including prescribed medicines, are not taxed.
- Hypogonadism
- Low testosterone caused by a problem in the testicles or in the brain and pituitary signals that control them, confirmed with symptoms and repeated morning blood tests.
- Intramuscular (IM)
- Injected into a muscle. Most testosterone cypionate and enanthate is given this way.
- Product label (prescribing information)
- The official document approved by a medicines regulator for a product, describing its uses, doses, warnings and storage.
- LH and FSH
- Luteinizing hormone and follicle-stimulating hormone, the pituitary signals that tell the testicles to make testosterone and sperm. Testing them shows whether low testosterone starts in the testicles or in the brain.
- Medicaid
- The US public health program for people with low incomes, run by each state within federal rules. Each state sets its own drug list and approval rules.
- Medicare Part B
- The part of Medicare that pays for doctor visits and for drugs given in a clinic, such as Aveed injections.
- Medicare Part D
- Medicare's prescription drug benefit, provided through private plans that each set their own drug list. In 2026 the standard deductible is $615 and out-of-pocket drug costs are capped at $2,100.
- NADAC
- National Average Drug Acquisition Cost: a weekly federal survey of what US pharmacies pay for medicines. It is not the price a patient is charged.
- Prescription drug monitoring program (PDMP)
- A state database of controlled-substance prescriptions that prescribers and pharmacists can check. Every US state has one.
- Prior authorization
- A health plan's approval step before it will pay for a medicine. For testosterone it usually means sending two low blood test results and a diagnosis.
- REMS
- Risk Evaluation and Mitigation Strategy: an FDA safety program that restricts how a medicine is given. Aveed can be given only in certified settings, with 30 minutes of observation after each injection.
- Schedule III (US)
- A US drug-control category for medicines with accepted medical use and a moderate risk of misuse. Testosterone and its esters are listed here as anabolic steroids.
- Special registration for telemedicine
- A DEA registration proposed in January 2025 that would let qualified clinicians prescribe Schedule III–V drugs by telehealth without an in-person visit. It is not yet in force.
- Step therapy
- A plan rule that you must try a cheaper medicine first, such as a generic injection, before it covers a more expensive one.
- Subcutaneous (SC)
- Injected into the fatty layer just under the skin. Xyosted is given this way.
- Telehealth (telemedicine)
- Care given by video, phone or other remote contact instead of in person. US rules for prescribing controlled drugs this way change after December 31, 2026 unless new action is taken.
- Transdermal
- Absorbed through the skin, as with testosterone gels and solutions.
- TRT (testosterone replacement therapy)
- Prescribed testosterone, by injection, gel or other forms, for men with low testosterone.
- Urologist
- A doctor who specializes in the urinary tract and male reproductive organs, and a common prescriber of testosterone in the US.
- WADA
- The World Anti-Doping Agency, which publishes the list of substances banned in sport. Testosterone is prohibited at all times.
How this guide was researched
This guide is built from a thorough review of the sources cited throughout it: US laws and federal regulations, regulators' pages and data, product labels, clinical guidelines, published insurer and Medicaid policies, and clinical trials. We also reviewed public online forums where men describe getting and keeping TRT in the US.
The guide cites 116 sources, including 86 laws, regulations, regulators' pages and data, and product labels, 5 published insurer and Medicaid policies, 6 clinical guidelines and criteria, 2 original clinical trials, and 17 public community discussions. Each type of source answers a different question. Laws, regulations and plan policies show the rules. Guidelines and labels show what clinicians are told to do. Trials show what was measured. Personal accounts show what individual people experienced. Every numbered citation links to its entry below, labeled by source type.
How this guide was made
Research and drafting were AI-assisted. Every cited source was checked against the original, and the guide was reviewed and edited by Doserly before publication. It has not had an independent clinical review, and Doserly does not currently have medical reviewers. Doserly makes a medication and health-tracking app and runs Doserly Academy, both of which are promoted in this guide. Read our editorial policy for how guides are researched, updated and corrected.
This guide is for educational purposes. It summarizes what the reviewed sources report so the research is easier to understand; it is not medical advice, legal advice or advice about any insurance plan. For a deeper dive, or to check any point for yourself, go straight to the cited sources.
Explore the sources
These are the documents cited in this guide. Laws, regulations, regulators' data, product labels, insurer policies, guidelines, trials and personal accounts answer different questions. A source being listed does not mean every statement on its page is endorsed. Insurer policies change often; check your own plan's current document.
Showing 116 sources
- 01
21 CFR 1308.13(f) Schedule III: anabolic steroids ↗
Regulation (US)
Official legal text reviewed.
Detail: Testosterone and its esters are Schedule III anabolic steroids; no proposal to change this published (checked September 2026).
- 02
21 CFR 1306.03 Persons entitled to issue prescriptions ↗
Regulation (US)
Official legal text reviewed.
Detail: A prescriber must be authorized to prescribe controlled substances by the jurisdiction where licensed and be registered with the DEA.
- 03
Xyosted (testosterone enanthate) subcutaneous autoinjector 50, 75, 100 mg/0.5 mL prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Confirm low testosterone with morning tests on at least two separate days before starting; 75 mg subcutaneously once weekly to start; high doses suppress sperm production and reduced fertility may not reverse.
- 04
Evaluation and Management of Testosterone Deficiency: AUA Guideline ↗
Clinical guideline (US)
Full guideline reviewed.
Detail: Diagnose with symptoms or signs plus two early-morning total testosterone results below 300 ng/dL; LH in all men and a pituitary scan below 150 ng/dL with low or low-normal LH; check every 6–12 months; prefer commercial over compounded products; do not prescribe alkylated oral testosterone; do not prescribe testosterone to men trying to conceive.
- 05
UnitedHealthcare Prior Authorization/Medical Necessity - Testosterone (Program 2025 P 2018-19) ↗
Insurer policy (US)
Full policy reviewed.
Detail: Two pre-treatment total testosterone results below 300 ng/dL or below the lab range, taken at separate times (may require treatment to be temporarily held); 12-month approvals; renewal needs a recent level within or below range or a dose change; Xyosted only after failure of both generic injections and two gels.
- 06
Cigna National Formulary Prior Authorization Policy CNF620: Testosterone (Injectable) Products ↗
Insurer policy (US)
Full policy reviewed.
Detail: Two morning tests on separate days, both low by the lab's reference range; approve for 1 year.
- 07
42 U.S.C. 1395w-102(e) (Social Security Act 1860D-2): covered Part D drug ↗
Law (US)
Official legal text reviewed.
Detail: A covered Part D drug includes any use for a medically accepted indication, with the Medicaid exclusion list applying.
- 08
42 U.S.C. 1396r-8 (Social Security Act 1927)(d): limitations on Medicaid coverage of drugs ↗
Law (US)
Official legal text reviewed.
Detail: A state Medicaid program may require prior authorization for any covered outpatient drug and may exclude agents used to promote fertility.
- 09
NADAC (National Average Drug Acquisition Cost) 2026 dataset, testosterone rows (as of 23 Sep 2026) ↗
Federal price dataset (US)
Official dataset queried.
Detail: What pharmacies pay on average: generic cypionate 200 mg/mL 10 mL $3.58 per mL, 100 mg/mL $4.53 per mL, 1 mL vial $11.39; generic enanthate $14.48 per mL; generic 1.62% gel $0.47 per gram; Xyosted $316.50 per mL; Jatenzo $8.95–17.93 and Tlando $7.17 per capsule; Natesto $41.28 per gram. Not a patient price.
- 10
Medicare Part D Spending by Drug, data year 2024 (testosterone rows, Mftr_Name=Overall) ↗
Federal spending dataset (US)
Official dataset queried.
Detail: Generic cypionate: 1,118,253 claims for 281,637 people, $37.01 per claim; generic topical testosterone 556,670 claims, $167.85; Xyosted $788.20; Jatenzo $1,055.04; AndroGel $1,148.50. Gross spending before rebates.
- 11
Fourth Temporary Extension of COVID-19 Telemedicine Flexibilities for Prescription of Controlled Medications (FR 2025-24123) ↗
Regulation (US)
Official legal text reviewed.
Detail: Telemedicine prescribing of Schedule II–V medicines without an in-person visit is extended through 31 December 2026.
- 12
OIRA EO 12866 review record: RIN 1117-AB40 (Special Registrations for Telemedicine), final rule stage ↗
Regulatory record (US)
Official page reviewed.
Detail: The DEA special-registration final rule is under White House review and not yet published (checked 28 September 2026).
- 13
21 CFR 1306.22 Refilling of prescriptions ↗
Regulation (US)
Official legal text reviewed.
Detail: No Schedule III or IV prescription may be filled or refilled more than six months after issue or refilled more than five times.
- 14
Publication 52, 453 Controlled Substances and Drugs ↗
Postal regulation (US)
Official legal text reviewed.
Detail: Controlled substances, including any anabolic steroid, may be mailed only when both sender and recipient are DEA-registered.
- 15
World Anti-Doping Code International Standard: Prohibited List 2026 ↗
Anti-doping rule
Official list reviewed.
Detail: Testosterone is prohibited at all times (S1.1).
- 16
21 U.S.C. 812(b)(3): Schedule III findings ↗
Law (US)
Official legal text reviewed.
Detail: Schedule III: potential for abuse less than Schedules I and II; abuse may lead to moderate or low physical dependence or high psychological dependence.
- 17
21 U.S.C. 802(41): definition of anabolic steroid ↗
Law (US)
Official legal text reviewed.
Detail: Testosterone is named in the statutory definition of anabolic steroid.
- 18
Testosterone Information (Postmarket Drug Safety Information for Patients and Providers) ↗
Regulator page (US)
Official page reviewed.
Detail: Approved testosterone products are for men with low testosterone plus an associated medical condition; confirms the June 2026 label requests.
- 19
Kyzatrex (testosterone undecanoate) oral capsules 50, 100, 150, 200 mg prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Oral testosterone undecanoate with food; still states that safety and efficacy in age-related hypogonadism are not established; interactions with insulin, oral anticoagulants, corticosteroids and drugs that raise blood pressure. Sections 5 and 6.1 carry the class TRAVERSE text: atrial fibrillation 3.5% vs 2.4%, acute kidney injury 2.3% vs 1.5%, pulmonary embolism 0.9% vs 0.5%, about 61% stopped study gel; blood-pressure boxed warning removed 07/2025.
- 20
HHS Announces Requested Updates to Testosterone Therapy Product Labels ↗
Government announcement (US)
Official page reviewed.
Detail: FDA is requesting label changes: remove the age-related limitation, contraindicate only in metastatic prostate cancer, revise the prostate-enlargement warning. Requests, not yet in labels (checked September 2026).
- 21
DailyMed SPL: Testosterone cypionate injection (BPI Labs, ANDA 219478) ↗
Product label (US)
Relevant label sections reviewed.
Detail: A September 2026 generic label that still carries the age-related limitation, the known-or-suspected prostate cancer contraindication and the older statement that long-term heart safety trials have not been done.
- 22
Oklahoma Health Care Authority (SoonerCare) Endocrine PDL: Testosterone Replacement Medications prior authorization criteria ↗
State Medicaid policy (US)
Official page reviewed.
Detail: An FDA-approved diagnosis; two morning results below 300 ng/dL plus abnormal gonadotropins or documented disease; tier-2 products after 12-week trials of an injection and a topical; 1-year approvals.
- 23
Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline ↗
Clinical guideline
Full guideline reviewed.
Detail: Two fasting morning tests with an accurate assay; 264 ng/dL lower limit on standardized assays; LH and FSH to find the cause; check at 3–6 and 12 months, then yearly; suggests against routine treatment of all men 65 and older; lists reasons not to start.
- 24
21 CFR 1306.21 Requirement of prescription (Schedules III-V) ↗
Regulation (US)
Official legal text reviewed.
Detail: Schedule III–V drugs may be dispensed on a signed paper, faxed, electronic or oral prescription.
- 25
21 CFR 1306.04 Purpose of issue of prescription ↗
Regulation (US)
Official legal text reviewed.
Detail: A prescription must be for a legitimate medical purpose in the usual course of professional practice; the pharmacist has a corresponding responsibility.
- 26
CMS Electronic Prescribing for Controlled Substances (EPCS) Program ↗
Regulator page (US)
Official page reviewed.
Detail: The SUPPORT Act requires electronic prescribing of Schedule II–V drugs under Medicare Part D; prescribers are compliant at a 70% rate or higher.
- 27
21 U.S.C. 831: Additional requirements relating to online pharmacies and telemedicine ↗
Law (US)
Official legal text reviewed.
Detail: An online pharmacy must meet state pharmacy licensing law in each state it delivers from and to.
- 28
21 CFR 1301.19 Special requirements for online pharmacies ↗
Regulation (US)
Official legal text reviewed.
Detail: Online pharmacies must be state-licensed where they deliver from and to and hold a DEA registration modified for internet dispensing.
- 29
Evaluation for and Management of Males with Low Testosterone: Recommendations for Use (January 2026) ↗
Clinical recommendations (US)
Full document reviewed.
Detail: Fasting early-morning tests on two occasions; refer to endocrinology below 150 ng/dL with low or normal LH and FSH; check at 3–6 and 12 months; hematocrit above 48% is a contraindication, as is a desire for future fertility; aromatase inhibitors not generally recommended; hCG reserved for men wanting fertility.
- 30
DEA letter to registrants on state reciprocity (DEA-DC-018, COVID-19 public health emergency exception) ↗
Regulator letter (US)
Official letter reviewed.
Detail: DEA regulations require a practitioner to obtain a separate DEA registration in each state where they dispense a controlled substance (letter describing a COVID-19 emergency exception).
- 31
Diagnosis and Treatment of Infertility in Men: AUA/ASRM Guideline (2020; Amended 2024) ↗
Clinical guideline (US)
Full guideline reviewed.
Detail: Clinicians should not prescribe testosterone to men interested in current or future fertility.
- 32
Statement on Testosterone Replacement Therapy (Endocrine Society press statement, 16 July 2026) ↗
Clinical society statement
Full statement reviewed.
Detail: Diagnosis on at least two early-morning fasting tests with a common threshold near 300 ng/dL, the same approach at any age; weight loss typically first-line for low testosterone linked to obesity.
- 33
VA PBM Testosterone Replacement Therapy (TRT) in Males Criteria for Use (updated March 2025) ↗
Clinical criteria (US)
Full document reviewed.
Detail: Two unequivocally low fasting total testosterone results at least a week apart, 8–10 am; excludes hematocrit above 48% and a desire for future fertility; for recently started outside treatment without records, hold for 3–6 months and reassess; documentation can be waived case by case after more than a year.
- 34
Anthem Medical Drug Clinical Criteria CC-0026: Testosterone, Injectable ↗
Insurer policy (US)
Full policy reviewed.
Detail: Below 300 ng/dL at 70 or younger or below 200 ng/dL over 70 on two morning tests at least 24 hours apart; not approved with hematocrit above 48% (50% at altitude) or untreated sleep apnea; continuation needs a level within 180 days and symptom benefit.
- 35
Aetna Clinical Policy Bulletin 1014: Testosterone Cypionate Injections ↗
Insurer policy (US)
Full policy reviewed.
Detail: At least two confirmed low morning testosterone levels based on the lab range or current practice guidelines.
- 36
45 CFR 156.122 Prescription drug benefits (essential health benefits) ↗
Regulation (US)
Official legal text reviewed.
Detail: Plans covering essential health benefits must cover at least one drug in every USP category and class and decide non-formulary exception requests within 72 hours (24 hours if urgent).
- 37
Depo-Testosterone (testosterone cypionate) 100 and 200 mg/mL prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: 50–400 mg intramuscularly every 2 to 4 weeks; may lower blood glucose and insulin needs in diabetes; contraindicated in known or suspected prostate or breast cancer; still states that long-term heart safety trials have not been done; gives no in-use period for an opened vial.
- 38
Orange Book: August 2026 cumulative supplement changes (new approvals) ↗
Regulator list (US)
Official list reviewed.
Detail: New approvals include a generic testosterone cypionate 200 mg/mL (3 September 2026) and Kyzatrex 50 mg (25 August 2026).
- 39
Azmiro (testosterone cypionate) 200 mg/mL single-dose vial and prefilled syringe prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Testosterone cypionate 200 mg/mL, 50–400 mg every 2–4 weeks by deep gluteal intramuscular injection.
- 40
Testosterone enanthate injection USP 200 mg/mL (generic, Hikma) prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Generic enanthate 200 mg/mL: 50–400 mg every 2 to 4 weeks for male hypogonadism; still states that long-term heart safety trials have not been done (no TRAVERSE text, checked September 2026).
- 41
Aveed (testosterone undecanoate) 750 mg/3 mL intramuscular injection prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: 750 mg intramuscularly at the start, at 4 weeks, then every 10 weeks; boxed warning for oil microembolism and anaphylaxis; 30-minute observation; restricted program (REMS).
- 42
AndroGel 1.62% (testosterone gel) pump and packets prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Starting dose 40.5 mg (2.5 g of gel) each morning; boxed warning for secondary exposure.
- 43
AndroGel 1% (testosterone gel) pump and packets prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Daily testosterone gel; boxed warning for secondary exposure.
- 44
Testim (testosterone gel) 1%, 50 mg tube prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Daily testosterone gel 50 mg; boxed warning for secondary exposure.
- 45
Vogelxo (testosterone gel) 1% tube, packet and pump prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Daily testosterone gel 50 mg; boxed warning for secondary exposure; still states that long-term heart safety trials have not been done (checked September 2026).
- 46
Testosterone topical solution USP 30 mg/1.5 mL actuation (generic of Axiron, Lupin) prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Generic of the discontinued Axiron brand, applied to the armpits daily; still states that long-term heart safety trials have not been done (checked September 2026).
- 47
Jatenzo (testosterone undecanoate) oral capsules 158, 198, 237 mg prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Oral testosterone undecanoate twice daily with food.
- 48
Tlando (testosterone undecanoate) oral capsules 112.5 mg prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: Oral testosterone undecanoate 225 mg twice daily with food.
- 49
Natesto (testosterone) nasal gel 5.5 mg per actuation prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: 11 mg (one spray in each nostril) three times daily.
- 50
Testopel (testosterone pellets) 75 mg prescribing information ↗
Product label (US)
Relevant label sections reviewed.
Detail: 150–450 mg (two to six 75 mg pellets) implanted subcutaneously every 3 to 6 months; still states that long-term heart safety trials have not been done (checked September 2026).
- 51
DailyMed SPL listing: Methyltestosterone capsules (ANI, Jul 2025; Amneal, Jun 2025) and Methitest tablets (Amneal, Jun 2025) ↗
Label listing (US)
Official listing reviewed.
Detail: Oral methyltestosterone remains listed in the US.
- 52
Orange Book Preface (Approved Drug Products with Therapeutic Equivalence Evaluations), sections 1.2 and AO code ↗
Regulator reference (US)
Official page reviewed.
Detail: Different esters of the same drug are pharmaceutical alternatives and not therapeutically equivalent; injectable oils are rated equivalent only when active ingredient, concentration and oil are identical.
- 53
Federal Register 2020-10367: Withdrawal of approval of 16 NDAs (includes Striant NDA 021543) ↗
Regulatory notice (US)
Official notice reviewed.
Detail: Withdrawal of approval of 16 applications, including Striant buccal testosterone, effective 15 June 2020. Discontinuations of Androderm, Axiron, Fortesta and Delatestryl are from FDA and sponsor records in the Doserly fact base.
- 54
Compounding and the FDA: Questions and Answers ↗
Regulator page (US)
Official page reviewed.
Detail: Compounded drugs are not FDA-approved, and FDA does not verify their safety, effectiveness or quality before they are marketed.
- 55
FDA Questions and Answers on Outsourcing Facility Registration ↗
Regulator page (US)
Official page reviewed.
Detail: Drugs made by compounders, including outsourcing facilities, are not FDA-approved.
- 56
Billing and Coding: Testopel Coverage (A55056), Noridian (Medicare MAC, Jurisdictions E/F) ↗
Medicare coverage article (US)
Official page reviewed.
Detail: Testopel may be covered for the FDA-approved indication, up to six pellets actually implanted. A regional contractor policy.
- 57
Notice to Compounders: Changes that affect compounding as of March 23, 2020 ↗
Regulator notice (US)
Official page reviewed.
Detail: From 23 March 2020 hCG is regulated as a biologic and cannot be compounded under sections 503A or 503B.
- 58
Pharmacy Compounding Advisory Committee meeting transcript, 8 June 2022 ↗
Regulator meeting record (US)
Official transcript reviewed.
Detail: The committee voted 4 to 8 against adding enclomiphene citrate to the 503A bulks list.
- 59
Bulk Drug Substances Nominated for Use in Compounding Under Section 503A (categories list) ↗
Regulator list (US)
Official list reviewed.
Detail: Enclomiphene citrate is in Category 1 (under evaluation); this is not FDA approval.
- 60
openFDA Drug Shortages dataset (FDA Drug Shortages Database) ↗
Regulator dataset (US)
Official dataset queried.
Detail: No testosterone product listed as in shortage.
- 61
Final CY 2026 Part D Redesign Program Instructions (fact sheet) ↗
Regulator fact sheet (US)
Official page reviewed.
Detail: 2026 standard Part D benefit: $615 deductible and $2,100 annual out-of-pocket threshold.
- 62
Announcement of CY 2026 Medicare Advantage Capitation Rates and Part C and Part D Payment Policies (Table V-2) ↗
Regulator document (US)
Relevant table reviewed.
Detail: 2026 Part D deductible $615 and out-of-pocket threshold $2,100.
- 63
What's the Medicare Prescription Payment Plan? ↗
Government page (US)
Official page reviewed.
Detail: The Medicare Prescription Payment Plan spreads out-of-pocket drug costs over the year but does not save money or lower drug costs.
- 64
Special Advisory Bulletin: Pharmaceutical Manufacturer Copayment Coupons ↗
Government bulletin (US)
Full bulletin reviewed.
Detail: Manufacturer copay coupons generally may not be used by people in federal health programs, including Medicare Part D.
- 65
Medicare Part B Payment Allowance Limits, July 2026 (updated Aug 2026) and October 2026 files: HCPCS J3145 testosterone undecanoate 1 mg ↗
Federal payment file (US)
Official dataset queried.
Detail: Aveed (HCPCS J3145): $2.203 per mg from 1 October 2026. What Medicare pays, not the patient's share.
- 66
IRS Publication 502 (2025), Medical and Dental Expenses ↗
Tax guidance (US)
Official page reviewed.
Detail: Prescribed medicines count as medical expenses; a prescribed drug brought in or shipped from another country generally does not.
- 67
IRS Publication 969 (2025), Health Savings Accounts and Other Tax-Favored Health Plans ↗
Tax guidance (US)
Official page reviewed.
Detail: HSA distributions used for qualified medical expenses are not taxed.
- 68
21 U.S.C. 829: Prescriptions (subsections (b) Schedule III and IV; (e) dispensing by means of the Internet) ↗
Law (US)
Official legal text reviewed.
Detail: A Schedule III prescription may not be filled or refilled more than six months after its date or refilled more than five times; internet prescriptions need a prescriber who has done at least one in-person evaluation, or a covering practitioner.
- 69
21 CFR 1306.25 Transfer between pharmacies for refill purposes ↗
Regulation (US)
Official legal text reviewed.
Detail: Refill information may be transferred between pharmacies once; pharmacies sharing a real-time online database may transfer up to the maximum refills.
- 70
21 CFR 1306.08 Electronic prescriptions (paragraph (e) transfer for initial dispensing) ↗
Regulation (US)
Official legal text reviewed.
Detail: An unfilled electronic prescription for a Schedule II–V drug can be transferred between retail pharmacies once, at the patient's request.
- 71
21 CFR 1306.52 Other circumstances where VA practitioners may prescribe controlled substances via telemedicine ↗
Regulation (US)
Official legal text reviewed.
Detail: A VA clinician may prescribe by telemedicine to a VA patient who has at any time had an in-person evaluation by any VA practitioner.
- 72
21 U.S.C. 844(a): Penalties for simple possession ↗
Law (US)
Official legal text reviewed.
Detail: Possession without a valid prescription, first offense: up to 1 year and a minimum $1,000 fine.
- 73
21 U.S.C. 841(b)(1)(E): penalties, Schedule III ↗
Law (US)
Official legal text reviewed.
Detail: Schedule III distribution, first offense: up to 10 years and a fine up to $500,000 for an individual.
- 74
21 CFR 1306.23 Partial filling of prescriptions ↗
Regulation (US)
Official legal text reviewed.
Detail: Partial fills are allowed within the total prescribed, with no dispensing after 6 months.
- 75
PDMP Administrators' Orientation Guide (revision 5 Nov 2024) ↗
Government-funded guide (US)
Relevant section reviewed.
Detail: All 50 states, the District of Columbia and three territories have operational prescription drug monitoring programs.
- 76
Transfer of Electronic Prescriptions for Schedules II-V Controlled Substances Between Pharmacies for Initial Filling (final rule) ↗
Final rule (US)
Official legal text reviewed.
Detail: Allows a one-time transfer of an unfilled electronic controlled-substance prescription at the patient's request, effective 28 August 2023.
- 77
Special Registrations for Telemedicine and Limited State Telemedicine Registrations (proposed rule, RIN 1117-AB40) ↗
Proposed rule (US)
Official legal text reviewed.
Detail: Proposes a Telemedicine Prescribing Registration for Schedule III–V drugs, a State Telemedicine Registration for each patient state, and a nationwide PDMP check after 3 years. A proposal, not law.
- 78
Continuity of Care via Telemedicine for Veterans Affairs Patients (final rule) ↗
Final rule (US)
Official legal text reviewed.
Detail: Lets VA practitioners prescribe controlled substances by telemedicine to VA patients previously seen in person by a VA practitioner.
- 79
Expansion of Buprenorphine Treatment via Telemedicine Encounter and Continuity of Care via Telemedicine for VA Patients (delay of effective date) ↗
Final rule (US)
Official legal text reviewed.
Detail: Delays the VA telemedicine rule's effective date to 31 December 2025.
- 80
21 CFR 1306.09 Prescription requirements for online pharmacies ↗
Regulation (US)
Official legal text reviewed.
Detail: No prescription controlled substance may be dispensed by means of the Internet without a valid prescription.
- 81
BeSafeRx: Considering an Online Pharmacy? (and Locate a State-Licensed Online Pharmacy) ↗
Regulator page (US)
Official page reviewed.
Detail: A safe online pharmacy always requires a doctor's prescription and is licensed with a state board of pharmacy, with a US address, phone number and a licensed pharmacist.
- 82
Preventing Unsafe Injection Practices (CDC injection safety, clinical safety) ↗
Public health guidance (US)
Official page reviewed.
Detail: Once opened, a multi-dose vial should be dated and discarded within 28 days unless the manufacturer states another date. Written for health-care settings.
- 83
USP General Chapter <797> FAQs (December 2023) ↗
Standards body guidance (US)
Full document reviewed.
Detail: A multiple-dose vial must be discarded no later than 28 days after first puncture. A standard for sterile preparations in health-care settings.
- 84
TSA What Can I Bring: Medications (Liquid) ↗
Regulator page (US)
Official page reviewed.
Detail: Medically necessary liquids and gels are allowed in reasonable quantities above the usual limit if declared at the checkpoint.
- 85
21 CFR 1301.26 Exemptions from import or export requirements for personal medical use ↗
Regulation (US)
Official legal text reviewed.
Detail: A traveler may enter or leave with their own controlled medicine in its original dispensed container and declared; a US resident may bring back no more than 50 dosage units obtained abroad.
- 86
TSA What Can I Bring: Unused Syringes / Used Syringes ↗
Regulator page (US)
Official page reviewed.
Detail: Unused syringes are allowed when accompanied by injectable medicine; used syringes must be in a sharps or hard-surface container.
- 87
CBP: Prohibited and Restricted Items (Medication section) ↗
Regulator page (US)
Official page reviewed.
Detail: Visitors: original container and, as a rule of thumb, no more than a 90-day supply; controlled substances must also meet DEA rules.
- 88
Personal Importation (FDA Import Basics) ↗
Regulator page (US)
Official page reviewed.
Detail: In most circumstances it is illegal for individuals to import drugs for personal use; the DEA decides for controlled substances; foreign nationals may bring a 90-day supply.
- 89
Cardiovascular Safety of Testosterone-Replacement Therapy ↗
Human trial
Original abstract reviewed.
Detail: TRAVERSE: 5,204 men aged 45–80 at high heart risk; heart attack, stroke or cardiovascular death in 182 men (7.0%) on testosterone gel vs 190 (7.3%) on placebo (hazard ratio 0.96, 95% CI 0.78 to 1.17), meeting the noninferiority margin; mean treatment 21.7 months and mean follow-up 33.0 months.
- 90
FDA issues class-wide labeling changes for testosterone products ↗
Regulator statement (US)
Official page reviewed.
Detail: Class-wide changes: TRAVERSE results and blood-pressure warnings added, boxed-warning language about heart risk removed, age-related limitation kept; recounts the 2015 labeling changes on age-related low testosterone.
- 91
Testosterone Treatment and Fractures in Men with Hypogonadism ↗
Human trial
Original abstract reviewed.
Detail: TRAVERSE fracture substudy: clinical fractures in 91 of 2,601 men on testosterone gel (3.50%) vs 64 of 2,603 on placebo (2.46%); hazard ratio 1.43 (95% CI 1.04 to 1.97).
- 92
FDA Expert Panel on Testosterone Replacement Therapy for Men (meeting page) ↗
Regulator meeting page (US)
Official page reviewed.
Detail: FDA Expert Panel on Testosterone Replacement Therapy for Men.
- 93
FDA Takes Step Forward on Testosterone Therapy for Men (press release) ↗
Regulator announcement (US)
Official page reviewed.
Detail: Invites makers of approved TRT products to seek a new use in low libido; an invitation, not an approval.
- 94
TUE Physician Guidelines – Male Hypogonadism, Version 9 (January 2026) ↗
Anti-doping guidance
Official guidance reviewed.
Detail: Exemptions for testosterone are granted only for low testosterone with an organic cause, not for age or obesity.
- 95
INCB Green List: List of Psychotropic Substances under International Control, 36th edition (2025) ↗
International control list
Official list reviewed.
Detail: Testosterone is not on the list of internationally controlled psychotropic substances.
- 96
Misuse of Drugs Act 1971, Schedule 2 Part III (Class C drugs) ↗
Law (UK)
Official legal text reviewed.
Detail: Testosterone is a Class C drug.
- 97
Controlled Drugs and Substances Act (S.C. 1996, c. 19): ss. 4, 6 and Schedule IV ↗
Law (Canada)
Official legal text reviewed.
Detail: Testosterone is in Schedule IV.
- 98
Therapeutic Goods (Poisons Standard—June 2026) Instrument 2026 (F2026L00633) ↗
Regulation (Australia)
Official legal text reviewed.
Detail: Testosterone is a Schedule 4 prescription-only medicine.
- 99
World Anti-Doping Code International Standard: Prohibited List 2027 (and explanatory note) ↗
Anti-doping rule
Official list reviewed.
Detail: Testosterone remains prohibited from 1 January 2027.
- 100
Endocrinologists not accepting patients for Low T? ↗
Community account
Public thread reviewed: opening post and 30 comments.
Detail: After results of 195 and then 162 ng/dL, a primary care doctor referred the poster to endocrinology; at least five offices declined once they learned the referral was for testosterone, and the one that accepted offered a date about 11 months away. The most common reply was to ask for a urologist instead.
- 101
Low T, endo or clinic? ↗
Community account
Public thread reviewed: opening post and 14 comments.
Detail: A wife describes her husband's result of 184 and a primary care doctor who would not prescribe without an endocrinologist, whose earliest appointments were 5 to 6 months away. In a later comment she reported finding a private endocrinology appointment within weeks.
- 102
35. VA won’t help. Weighing all my options. Any input helps. ↗
Community account
Public thread reviewed: opening post and 21 comments.
Detail: A veteran in his 30s reported VA results of 162 and then 390 a week later, and 247 at a local clinic; replies suggested retesting because the results varied so much.
- 103
Looking for Legit TRT clinic ↗
Community account
Public thread reviewed: opening post and 13 comments.
Detail: A veteran diagnosed with low testosterone during military service reported repeated results around 260 to 270 ng/dL that the VA considered acceptable. One reply described using private insurance instead: two results below 300 plus prior authorization, then a $10 copay for 84 days.
- 104
36M, Natural test came back at 484. Clinic said I was low and prescribed me, should I even consider starting ? ↗
Community account
Public thread reviewed: opening post and 38 comments.
Detail: A man in his 30s who felt mostly well said a clinic called his result of 484 low and offered 100 mg a week; many replies advised retesting and working on training, sleep and diet before starting.
- 105
Is TRT difficult to get covered by insurance? ↗
Community account
Public thread reviewed: opening post and 74 comments.
Detail: With a total testosterone of 182, the poster was quoted about $200 a month by a clinic; a urologist prescribed Xyosted at the first visit, but the insurer asked for another blood test 4 weeks later before covering it. Several replies reported paying $10 to $15 a month for covered cypionate.
- 106
Wow, I got Insurance coverage, and here’s what I did. ↗
Community account
Public thread reviewed: opening post and 13 comments.
Detail: After losing weight, a man in his 30s still had symptoms at about 415 ng/dL; his primary care doctor expected insurance to refuse, a urologist tried clomiphene for 6 months and then prescribed testosterone, and his plan charged $25 for a 90-day supply. A reply noted that most plans want results below 300.
- 107
Im confused at the price of my testosterone!?!? ↗
Community account
Public thread reviewed: opening post and 59 comments.
Detail: A primary care doctor prescribed AndroGel after a result of 27 ng/dL, expecting a cost near $40; the pharmacy quoted about $700 even for the generic with a discount card, and his insurance did not cover the gel. Replies suggested asking about prior authorization and noted that injections usually cost far less.
- 108
If you are paying a clinic to get your shots monthly. You’re getting ripped off. ↗
Community account
Public thread reviewed: opening post and 210 comments.
Detail: A man prescribed TRT for more than 20 years said a 10 mL vial of 200 mg/mL costs him $30 at a retail pharmacy. The most-upvoted replies answered that the hard part is finding a prescriber, and others valued an all-inclusive monthly membership.
- 109
Paying for meds I don’t use with my TRT refill is this standard practice? ↗
Community account
Public thread reviewed: opening post and 39 comments.
Detail: When he asked for a refill, a man on clinic TRT was quoted $500 for a package that had to include anastrozole and tamoxifen he said he did not need. One reply worked out that, if the package lasted 4 months, it came to about $125 a month; others described cheaper routes, including a regular prescription filled at a pharmacy.
- 110
Doctor couldn’t keep scheduled appointment and wont refill prescription until I see him a month from now. ↗
Community account
Public thread reviewed: opening post and 35 comments.
Detail: A urologist cancelled two follow-up visits and would not refill the prescription until a visit a month later; the most-upvoted reply said the doctor should bridge the gap.
- 111
Help! I'm injecting 0.5ml twice a week. I have about three doses left. I texted my clinic for s routine refill and here's what I got back. What do I do? ↗
Community account
Public thread reviewed: opening post and 87 comments.
Detail: The nurse who ran a small clinic began an extended absence without telling patients when the poster had about three doses left; he later reported that his own local physician prescribed enough to bridge the gap until he joined a new clinic.
- 112
Trouble getting test from pharmacy ↗
Community account
Public thread reviewed: opening post and 10 comments.
Detail: After moving states, the poster needed a new prescription from a new doctor; the first pharmacy held it for insurance authorization, then reported the medicine was backordered.
- 113
Enanthate shortage / discontinuation? ↗
Community account
Public thread reviewed: opening post and 6 comments.
Detail: A man who could not use cypionate said his prescriber and local pharmacies in Florida could no longer get enanthate; replies said a mail-order pharmacy stocked it and that another Florida pharmacy still filled it.
- 114
Pharmacy now advising I throw testosterone away 28 days past using. Advice on switching to 1ml bottles ↗
Community account
Public thread reviewed: opening post and 65 comments.
Detail: A pharmacy newly told a long-term patient to discard each 10 mL vial 28 days after first use; in a later comment he said the pharmacist told him they have to give that advice. Replies were split on whether the rule applies to testosterone.
- 115
Worth coming off for 6 weeks to get Urologist TRT? ↗
Community account
Public thread reviewed: opening post and 68 comments.
Detail: A man who had started TRT through an online clinic asked a urologist to take over; the urologist said he would need to stop for about a month so qualifying tests could support a prescription and insurance. Replies ranged from finding another urologist to asking the insurer what levels it approves.
- 116
Talking to Urologist about HCG ↗
Community account
Public thread reviewed: opening post and 5 comments.
Detail: After moving states, a man on TRT for 2 years discussed hCG with a new urologist, who said it would be expensive because insurance would not cover it.
No matching sources
Try a different term or show the full list.
Updates and corrections
Updated September 28, 2026. This version replaces the earlier guide to getting TRT in the United States with a rewrite based on current US law and federal regulations, product labels, clinical guidelines and published insurer and Medicaid policies. It adds the step-by-step route to a prescription, a table of the qualifying rules in guidelines, labels, the VA and named insurer policies, a dated product list, official cost figures, the prescription, transfer and telehealth rules, travel and import limits, and the full TRAVERSE results. It corrects the earlier page on several points: the DEA's January 2025 special-registration rules for telehealth were a proposal, not rules in force; the VA telemedicine rule took effect on December 31, 2025, not in January 2025; TRAVERSE enrolled 5,204 men, and its atrial fibrillation, kidney and clot results are given as the label's percentages; the Androderm patch and Striant buccal tablet are no longer sold; and the February 2025 changes removed boxed-warning language about heart risk rather than every boxed warning. Named telehealth clinic brands and clinic-blog price ranges were removed; costs now come from federal price and spending data, and cash prices appear only as dated individual accounts. The date describes this revision, not a fresh check of every source.
Found an error or a relevant source we missed? Report a correction with the guide title, the specific passage and a supporting source if available. Please leave out personal health records. See our editorial policy for how we handle attribution, evidence limits and corrections.